

Paper Menu >>
Journal Menu >>
 Surgical Science, 2011, 2, 463-467 doi:10.4236/ss.2011.210102 Published Online December 2011 (http://www.SciRP.org/journal/ss) Copyright © 2011 SciRes. SS Predictors for Adverse Outcome in Patients Aged 80 Years and Older Undergoing Emergent Hip Surgery Eli Peled1, Michal Barak2, Yaniv Keren3, Michael Soudry3, Doron Norman1 1Departments of Orthopedic Surgery B, Rambam Health Care Campus and the Bruce Rappaport Faculty of Medicine, Technion-Israel Institute of Technology, Haifa, Israel 2Departments of Anesthesia, Rambam Health Care Campus and the Bruce Rappaport Faculty of Medicine, Technion-Israel Institute of Technology, Haifa, Israel 3Departments of Orthopedic Surgery A, Rambam Health Care Campus and the Bruce Rappaport Faculty of Medicine, Technion-Israel Institute of Technology, Haifa, Israel E-mail: [email protected] Received June 10, 2011; revised September 14, 2011; accepted October 14, 2011 Abstract Background: Increased life expectancy results in aging of the population. One of the leading medical pro- blems of elderly patients is hip fracture. We studied demographic, surgical and anesthetic parameters of eld- erly patients who underwent surgery due to osteoporotic hip fracture, to find predictors for peri-operative morbidity and mortality. Methods: This is a retrospective review of prospectively collected data of patients aged 80 years and older who underwent emergent surgery due to osteoporotic femoral neck, subcapital or pertrochanteric fractures. Data was collected on age, gender, co-morbidities, American Society of Anesthesi- ologists Class, number of regular medications, whether the patient was bedridden or not before the surgery, hemoglobin on admission and on discharge, type of surgery and anesthesia, duration of surgery, duration of hospitalization, post-operative morbidity and mortality. The demographic and peri-operative parameters were analyzed and matched to the post-operative complications and mortality to find predictors for adverse out- come. Results: One hundred and nine patients were included in the study, of whom 22 (20%) had post-ope- rative complications and 10 (9.1%) died. We found an increased complication rate in patients who had chr- onic obstructive pulmonary disease and in patients who underwent general anesthesia. Patients who were bedridden before the surgery had increased mortality rates. No significant correlation was found between outcome and any other factors. Conclusion: Our results suggest favoring regional anesthesia in elderly pa- tients undergoing emergent femoral neck surgery and acknowledging a higher risk in chronic pulmonary disease or bedridden patients. Keywords: Femoral Fracture, Surgery, Orthopedics, Anesthesia, Spinal, Complications, Postoperative 1. Introduction Osteoporotic hip fracture is a major health problem world- wide [1]. Its incidence has been rising steadily, mainly due to increased life expectancy [1,2], and this trend is expected to continue in the future. There were 1.6 mil- lion osteoporotic hip fractures throughout the world in 2000 [1] and it has been estimated that the number of hip fractures in 2025 will be 2.6 million and in 2050 will be 4.5 million [3]. The age of the patients has been increas- ing as well. Although age is recognized as a significant risk factor for complications and mortality [4,5], there is no recommendation to avoid surgery at any age [6,7]. In this study we focused on the elderly population, patients aged 80 years or more, in order to isolate age from other risk factors. We believe that patients in this age group constitute a distinct entity, with typical physiology and unique medical characteristics and needs. We prospec- tively followed their management during surgery and hospital stay to find predictors for adverse outcome, in the hope that this could lead to better management of these patients in the future, although it is still uncertain whether or not their outcome is modifiable [8]. 2. Patients and Methods With the approval of the local Ethics Committee, we conducted this study, a retrospective review of prospec-  E. PELED ET AL. 464 tively collected data of patients 80 years old or older who underwent emergent orthopedic surgery for osteoporotic femoral neck fracture in our institution. The surgery took place within less than 48 hours from admission to the emergency room. All the patients were assessed pre- operatively by an anesthesiologist who determined their American Society of Anesthesiologists (ASA) class and planned the type of anesthesia and the level of operative and post-operative monitoring. The anesthesia of choice was regional, specifically spinal. Only patients who had a contraindication for regional anesthesia, such as abnor- mal coagulation blood tests, had general anesthesia. In the operating room, the patients were monitored and treated according to their general condition and the se- quence of the surgery. The senior orthopedic surgeon de- cided, according to the fracture type, whether to do a par- tial hip replacement (PHR) or reduction and internal fix- ation. Displaced sub-capital fractures, Garden III & IV, were replaced, while nondisplaced sub-capital fractures, Garden I & II, were stabilized by three 7.3 mm cannu- lated screws (CS). Femoral and intertrochanteric frac- tures were reduced by closed or open means and were stabilized by dynamic hip screw (DHS) or proximal fe- moral nail (PFN). All the patients were admitted to the post-anesthesia care unit following surgery, where they stayed for two hours or more, depending on their general condition. In cases of hemodynamic instability, respire- tory problem, or intra-operative complication, the patient was transferred to the intensive care unit. Patients who underwent uneventful surgery were transferred 7 - 9 days later to another institution for rehabilitation. Follow-up continued during their hospitalization time. Collected data included age, gender, co-morbidities: hypertension, ischemic heart disease, diabetes mellitus, chronic obstructive pulmonary disease (COPD), other co-morbidity, number of medications that the patient used regularly before admission to hospital, whether or not the patient was bedridden before the surgery, ASA class, hemoglobin on admission and on discharge and the disparity between them, type of surgery (PHR, DHS, CS PFN), duration of surgery, type of anesthesia, duration of hospitalization, 30 day post-operative morbidity, and mortality within six months of surgery. Morbidity was defined as a new disease or illness (new diagnosis) that occurred in the peri-operative peiod, meaning within a month from surgery. We analyzed the data and studied correlations between each and every pre- and intra-ope- rative parameter to post-operative morbidity and morta- lity, in order to find predictors for adverse outcome. 3. Statistical Analysis Data was analyzed with a commercial statistical software (Statistica 6.0, StatSoft, Tulsa OK). Frequencies were compared using Pearson’s chi square test. Continuous variables were compared using analysis of variance. Whenever the homogeneity of variance was violated (significant Levene’s test), the Mann-Whitney test was applied instead. Pre-post comparisons used the t-test for dependent variables. Significance level was set at p < 0.05. 4. Results One hundred and nine patients were included in the study, 32 (29%) male and 77 (71%) female. Age ranged be- tween 80 to 98 years (median 85); there was no signifi- cant age difference between genders. Patients’ co-morbi- dities are summarized in Table 1. The type of surgery was PHR in 29 (26.6%) patients and CS or DHS or PFN in 80 (73.3%) patients. In Table 2 we compared patients who underwent PHR to those who had CS or DHS or PFN. Spinal anesthesia was used in 95 (87.2%) patients and general anesthesia in 14 (12.8%) patients. The contraindication for regional anesthesia in all the patients who underwent general anesthesia was the use of anticoagulants or anti-platelet aggregation drugs, other than acetylsalicylic acid. Mean length of hospital stay was 7.6 days (SD 3.5 days). Twenty-two (20%) patients had post-operative com- plications and 10 (9.1%) patients died. Post-operative complications are summarized in Table 3. Predictors for adverse outcome: patients with COPD had significantly higher rates of post-operative complica- tions than other patients (p = 0.001). The complication rate was significantly higher in patients who had general anesthesia (35%) compared to those who had spinal an- Table 1. Patient co-morbidities and pre-operative data. Number of Patients (%) Hypertension 87 (81%) Ischemic heart disease 44 (41%) Diabetes mellitus 26 (24%) Chronic obstructive pulmonary disease 7 (6.5%) Other co-morbidities 83 (77.5%) Patient bedridden 14 (13%) American Society of Anesthesiology (ASA) class, Mean (±SD) 2.8 (± 0.7) Number of regular medications used, Mean (±SD) 5.3 (± 3.2) Pre-operative hemoglobin (g%)* Mean (range) 12.4 (7.1-15.5) *Normal range is 12.0 - 16.0 g%. Copyright © 2011 SciRes. SS 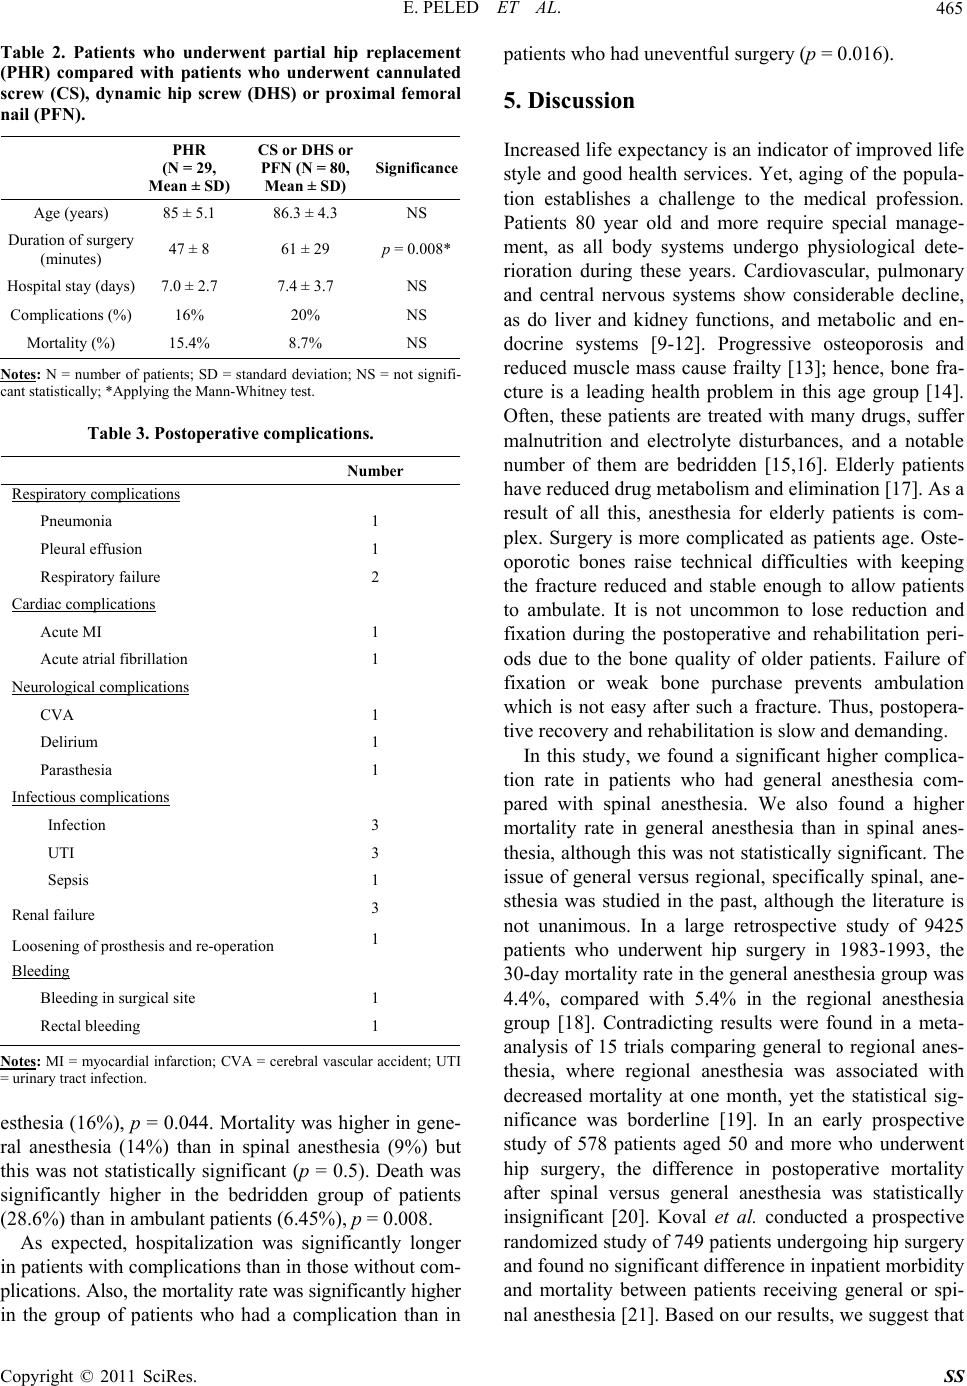 E. PELED ET AL.465 Table 2. Patients who underwent partial hip replacement (PHR) compared with patients who underwent cannulated screw (CS), dynamic hip screw (DHS) or proximal femoral nail (PFN). PHR (N = 29, Mean ± SD) CS or DHS or PFN (N = 80, Mean ± SD) Significance Age (years) 85 ± 5.1 86.3 ± 4.3 NS Duration of surgery (minutes) 47 ± 8 61 ± 29 p = 0.008* Hospital stay (days) 7.0 ± 2.7 7.4 ± 3.7 NS Complications (%) 16% 20% NS Mortality (%) 15.4% 8.7% NS Notes: N = number of patients; SD = standard deviation; NS = not signifi- cant statistically; *Applying the Mann-Whitney test. Table 3. Postoperative complications. Number Respiratory complications Pneumonia Pleural effusion Respiratory failure 1 1 2 Cardiac complications Acute MI Acute atrial fibrillation 1 1 Neurological complications CVA Delirium Parasthesia 1 1 1 Infectious complications Infection UTI Sepsis 3 3 1 Renal failure 3 Loosening of prosthesis and re-operation 1 Bleeding Bleeding in surgical site Rectal bleeding 1 1 Notes: MI = myocardial infarction; CVA = cerebral vascular accident; UTI = urinary tract infection. esthesia (16%), p = 0.044. Mortality was higher in gene- ral anesthesia (14%) than in spinal anesthesia (9%) but this was not statistically significant (p = 0.5). Death was significantly higher in the bedridden group of patients (28.6%) than in ambulant patients (6.45%), p = 0.008. As expected, hospitalization was significantly longer in patients with complications than in those without com- plications. Also, the mortality rate was significantly higher in the group of patients who had a complication than in patients who had uneventful surgery (p = 0.016). 5. Discussion Increased life expectancy is an indicator of improved life style and good health services. Yet, aging of the popula- tion establishes a challenge to the medical profession. Patients 80 year old and more require special manage- ment, as all body systems undergo physiological dete- rioration during these years. Cardiovascular, pulmonary and central nervous systems show considerable decline, as do liver and kidney functions, and metabolic and en- docrine systems [9-12]. Progressive osteoporosis and reduced muscle mass cause frailty [13]; hence, bone fra- cture is a leading health problem in this age group [14]. Often, these patients are treated with many drugs, suffer malnutrition and electrolyte disturbances, and a notable number of them are bedridden [15,16]. Elderly patients have reduced drug metabolism and elimination [17]. As a result of all this, anesthesia for elderly patients is com- plex. Surgery is more complicated as patients age. Oste- oporotic bones raise technical difficulties with keeping the fracture reduced and stable enough to allow patients to ambulate. It is not uncommon to lose reduction and fixation during the postoperative and rehabilitation peri- ods due to the bone quality of older patients. Failure of fixation or weak bone purchase prevents ambulation which is not easy after such a fracture. Thus, postopera- tive recovery and rehabilitation is slow and demanding. In this study, we found a significant higher complica- tion rate in patients who had general anesthesia com- pared with spinal anesthesia. We also found a higher mortality rate in general anesthesia than in spinal anes- thesia, although this was not statistically significant. The issue of general versus regional, specifically spinal, ane- sthesia was studied in the past, although the literature is not unanimous. In a large retrospective study of 9425 patients who underwent hip surgery in 1983-1993, the 30-day mortality rate in the general anesthesia group was 4.4%, compared with 5.4% in the regional anesthesia group [18]. Contradicting results were found in a meta- analysis of 15 trials comparing general to regional anes- thesia, where regional anesthesia was associated with decreased mortality at one month, yet the statistical sig- nificance was borderline [19]. In an early prospective study of 578 patients aged 50 and more who underwent hip surgery, the difference in postoperative mortality after spinal versus general anesthesia was statistically insignificant [20]. Koval et al. conducted a prospective randomized study of 749 patients undergoing hip surgery and found no significant difference in inpatient morbidity and mortality between patients receiving general or spi- nal anesthesia [21]. Based on our results, we suggest that Copyright © 2011 SciRes. SS  E. PELED ET AL. 466 general anesthesia carried an increased complication risk compared with spinal anesthesia in the selected group of patients aged 80 years or more. In addition, we found that COPD significantly in- creased the risk of postoperative complications in this group of elderly patients. The causative association be- tween COPD and hip fracture is well known since COPD patients who are treated with systemic corticosteroids are at a higher risk for osteoporotic fractures [22]. However, their higher risk for poor outcome was only recently ac- knowledged. In 2002, Eisler et al. found that only COPD significantly affected functional recovery at three months after hip surgery [23]. Later, de Luise et al found that patients with COPD had a 60% - 70% higher risk of death following hip fracture than those without COPD [24]. These authors suggested that certain diseases are more strongly associated with mortality than others, since they profoundly affect the maintenance of normal physiology, as does the cardiopulmonary system. In summary, elderly patients are more vulnerable than younger patients, and their recovery ability is damaged. Every single complication may deteriorate the patient gravely. This is supported by our finding that the morta- lity rate was significantly higher in the group of patients who had a complication than in patients who had an un- eventful procedure. Thus, prompt and intensive reaction to a change in patient status is required. The recognition of elderly patients as a distinct group with certain medi- cal and surgical characteristics and needs is essential for future improvement of care. 6. References [1] O. Johnell and J. A. Kanis, “An Estimate of the World- wide Prevalence and Disability Associated with Osteo- porotic Fractures,” Osteoporosis International, Vol. 17, No. 12, 2006, pp. 1726-1733. doi:10.1007/s00198-006-0172-4 [2] C. Holroyd, C. Cooper and E. Dennison, “Epidemiology of Osteoporosis,” Best Practice & Research Clinical En- docrinology & Metabolism, Vol. 22, No. 5, 2008, pp. 671-685. doi:10.1016/j.beem.2008.06.001 [3] B. Gullberg, O. Johnell and J. A. Kanis, “World-Wide Projections for Hip Fracture,” Osteoporosis International, Vol. 7, No. 5, 1997, pp. 407-413. doi:10.1007/PL00004148 [4] M. Bhandari, H. Koo, L. Saunders, S. G. Shaughnessy, R. B. Dunlop and E. H. Schemitsch, “Predictors of In-Hos- pital Mortality Following Operative Management of Hip Fractures,” International Journal of Surgical Investiga- tion, Vol. 1, No. 4, 1999, pp. 319-326. [5] M. Cree, C. L. Soskolne, E. Belseck, J. Hornig, J. E. Mc- Elhaney, R. Brant and M. Suarez-Almazor, “Mortality and Institutionalization Following Hip Fracture,” Journal of the American Geriatrics Society, Vol. 48, No. 3, 2000, pp. 283-288. [6] E. Bergeron, L. Moore, K. Fournier, C. Gravel and A. Lavoie, “Patients with Isolated Hip Fracture must be Considered for Surgery Irrespectively of their Age, Co- morbidity Status and Provenance: A Statement Applica- ble even to Nonagerians,” Archives of Orthopedic and Trauma Surgery, Vol. 129, No. 11, 2009, pp. 1549-1555. doi:10.1007/s00402-009-0888-7 [7] A. D. Pelavski, M. J. Colomina, M. De Miguel M. E. Marquez, C. Dolors and M. Aranda, “Demographics of Nonagenarians and Centenarians with a Hip Frac- ture,” Anesthesia and Analgesia, Vol. 103, No. 6, 2006, pp. 1597-1599. doi:10.1213/01.ane.0000246354.21634.30 [8] G. G. Teng, J. R. Curtis and K. G. Saag, “Mortality and Osteoporotic Fractures: Is the Link Causal, and Is It Modifiable?” Clinical and Experimental Rheumatology, Vol. 26, No. 5, 2008, pp. S125-137. [9] A. F. Kramer, K. I. Erickson and S. J. Colcomb, “Exer- cise, Cognition, and the Aging Brain,” Journal of Applied Physiology, Vol. 101, No. 4, 2006, pp. 1237-1242. doi:10.1152/japplphysiol.00500.2006 [10] P. E. Krumpe, R. J. Knudson, G. Parsons and K. Reiser, “The Aging Respiratory System,” Clinics in Geriatric Medicine, Vol. 1, No. 1, 1985, pp. 143-175. [11] H. J. Priebe, “The Aged Cardiovascular Risk Patient,” British Journal of Anaesthesia, Vol. 85, No. 5, 2000, pp. 763-778. doi:10.1093/bja/85.5.763 [12] D. L. Schmucker, “Age-Related Changes in Liver Struc- ture and Function: Implications for Disease?” Experi- mental Gerontology, Vol. 40, No. 8-9, 2005, pp. 650-659. doi:10.1016/j.exger.2005.06.009 [13] M. Maggio, A. R. Cappola, G. P. Ceda, S. Basaria, C. W. Chia, G. Valenti and L. Ferrucci, “The Hormonal Path- way to Frailty in Older Men,” Journal of Endocrinologi- cal Investigation, Vol. 28, No. 11, 2005, pp. 15-19. [14] L.A. Beaupre, C. A. Jones, L. D. Saunders, D. W. Johns- ton, J. Buckingham and S. R. Majumdar, “Best Practices for Elderly Hip Fracture Patients. A Systematic Overview of the Evidence,” Journal of General Internal Medicine, Vol. 20, No. 11, 2005, pp. 1019-1025. doi:10.1111/j.1525-1497.2005.00219.x [15] L. H. Beck, “The Aging Kidney. Defending a Delicate Balance of Fluid and Electrolytes,” Geriatrics, Vol. 55, No. 4, 2000, pp. 26-28. [16] B. J. Rolls and P. A. Phillips, “Aging and Disturbances of Thirst and Fluid Balance,” Nutrition Reviews, Vol. 48, No. 3, 1990, pp. 137-144. doi:10.1111/j.1753-4887.1990.tb02915.x [17] R. Rivera and J. F. Antognini, “Perioperative Drug Ther- apy in Elderly Patients,” Anesthesiology, Vol. 110, No. 5, 2009, pp. 1176-1181. doi:10.1097/ALN.0b013e3181a10207 [18] D. A. O’Hara, A. Duff, J.A. Berlin, R.M. Poses, V.A. Lawrence, E.C. Huber, H. Noveck, B.L. Strom and J.L. Carson, ” The Effect of Anesthetic Technique on Postop- erative Outcomes in Hip Fracture Repair,” Anesthesiol- Copyright © 2011 SciRes. SS  E. PELED ET AL. Copyright © 2011 SciRes. SS 467 ogy, Vol. 92, No. 4, 2000, pp. 947-957. [19] M. J. Parker, S. C. Urwin, H. H. Handoll and R. Griffith, “General versus Spinal/Epidural Anaesthesia for Surgery for Hip Fractures in Adults,” Cochrane Database of Sys- tematic Reviews, Vol. 2, 2000, p. CD000521. [20] N. Valentin, B. Lomholt, J. S. Jensen, N. Hejgaard and S. Kreiner, “Spinal or General Anaesthesia for Surgery of the Fractured Hip? A Prospective Study of Mortality in 578 Patients,” British Journal of Anaesthesia, Vol. 58, No. 3, 1986, pp. 284-291. doi:10.1093/bja/58.3.284 [21] K. J. Koval, G. B. Aharonoff, A. D. Rosenberg, C. Schmigelski, R. L. Bernstein and J. D. Zuckerman, “Hip Fracture in the Elderly: The Effect of Anesthetic Tech- nique,” Orthopedics, Vol. 22, No. 1, 1999, pp. 31-34. [22] G. T. Ferguson, P. M. Calverley, J. A. Anderson, C. R. Jenkins, P. W. Jones, L. R. Willits, J. C. Yates, J. Vestbo and B. Celli, “Prevalence and Progression of Osteoporo- sis in Patients with COPD: Results From the Towards a Revolution in COPD Health Study,” Chest, Vol. 136, No. 6, 2009, pp. 1456-1465. doi:10.1378/chest.08-3016 [23] J. Eisler, R. Cornwall, E. Strauss, K. Koval, A. Siu and M. Gilbert, “Outcomes of Elderly Patients with Nondis- placed Femoral Neck Fractures,” Clinical Orthopaedics and Related Research, Vol. 399, 2002, pp. 52-58. [24] C. de Luise, M. Brimacombe, L. Pedersen and H. T. Sorensen, “Chronic Obstructive Pulmonary Disease and Mortality Following Hip Fracture: A Population-Based Cohort Study,” European Journal of Epidemiology, Vol. 23, No. 2, 2008, pp. 115-122. doi:10.1007/s10654-007-9211-5 |