

Paper Menu >>
Journal Menu >>
 Open Journal of Stomatology, 2011, 1, 172-178 doi:10.4236/ojst.2011.14026 Published Online December 2011 (http://www.SciRP.org/journal/ojst/ OJST ). Published Online December 2011 in SciRes. http://www.scirp.org/journal/OJST Clinical and radiographic evaluation of surgical treatment of zygomatic fractures using 1.5 mm miniplates system Paulo Norberto Hasse, Walter Cristiano Gealh*, Cassiano Costa Silva Pereira, Luiz Francisco Coradazzi, Osvaldo Magro Filho, Idelmo Rangel Garcia Junior Maxillofacial Surgery Department, Araçatuba Dentistry School, Universidade Estadual Paulista, São Paulo, Brazil. Email: *[email protected] Received 10 July 2011; revised 25 August 2011; accepted 5 September 2011. ABSTRACT Fractures of the zygomaticomaxillary complex are am- ong the most common face traumas. Based upon the complexity and great variety of reported diagnoses and treatments, the proposal of this study wa s to eva- luate, clinically and radiographically, unilateral zy- gomatic fractures treated through internal rigid fixa- tion with miniplates and screws of 1.5 mm. Material and Method: 15 patients with unilateral fractures of the zygomaticoma xillary complex were analyzed, and compared with 15 patients without fractures so that a comparative analysis of the area and the perimeter of the orbital cavities could be made, as well as the dis- tance from the nasal point to the zygomatic promi- nence between both groups. Results: In the radiogra- phic analysis, the both groups presented similarity in the perimeter and in the area of the orbital cavities. Concerning the distance from the nasal point to the zygomatic prominence, only the operated group show- ed a significant difference between the sides, even though clinically the observation of the asymmetry had been absent or discreet. Conclusions: The treat- ment of unilateral fractures of the zygomaticomaxil- lary complex with the use of plates and screws of the 1.5 mm system proved to be effective, showing good esthetic results and low complication rates. Keywords: Zygomatic Fractures; Internal Fracture Fixa- tion; Facial Injuries 1. INTRODUCTION The treatment of the fractures of the zygomaticomaxil- lary complex (ZMC) is amply discussed in the literature, being that three great conflicts still persist in relation to the applied therapy [1]. The first concerns the best way for surgical reduction of the fractures. The second is related to the necessity to fix them or not after the reduc- tion, and the third concerns the number of fixation points necessary so that the fractures of the ZMC are stabilized [2]. Treating with mi nipl at es and screws provi ded faci lity of use, good stability, bio-compatibility, as well as the pos- sibility of being used in areas where the bone is not so thick, with little soft tissue overlap, minimizing the sym- ptoms of local esthetic discomfort [3]. Technological development together with surgical ne- cessity stimulated the deve lopment of extremely delicate systems of plates and screws with guarantees of pro- moting adequate resistance to bending and three-dimen- sional mechanical stability assuring predictability in the treatment of facial fractures [4-6]. Considering the high rate of fractures in the ZMC and the disagreements about treatment we proposed to carry out the present study to evaluating the zygomatic fra- ctures treated with a 1.5 mm fixation system. 2. MATERIAL AND METHODS Thirty patients were analyzed clinically and radiogra- phically. Fifteen had been submitted to surgical treat- ment of a non-comminuted unilateral fracture of the zygo- maticomaxillary complex, and made up the Treated Group (TG) and fifteen peoples without fractures of the ZMC were called the Con trol Group (CG). On the fifteen patients of the TG access to the fronto- zygomatic region was carried out through a supraciliary incision. The second region to be accessed varied ac- cording to the case, using the infra-orbital region and/or zygomaticomaxillary pillar. The surgical reduction was carried out through the use of the Caroll-Girard screw and the internal fix ation was done in all the patients with titanium miniplates and screws of the system of 1.5 mm. Posteroanterior X-rays for the cheeks of the face (Wa- ter’s X-ray) were carried out in the thirty patients, fifteen in the TG and fifteen in the CG. After obtaining all radio- graphs, fifteen being from the operated patients and fif- teen from the salutary patients without fractures, the scan- ning of the same were done on a “ScanJet 4c/T” scanner 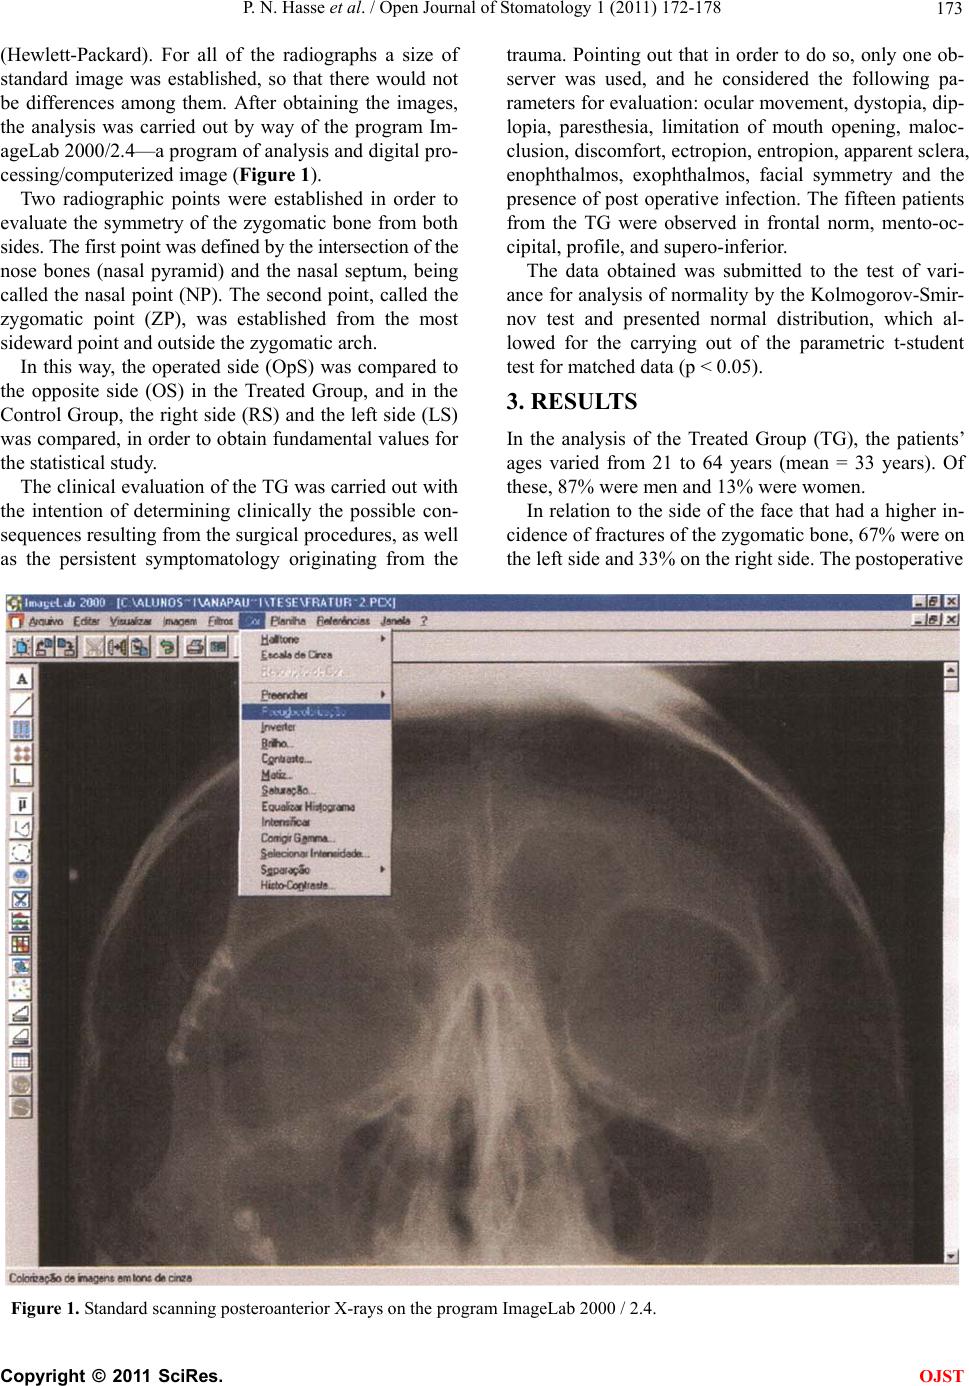 P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 173 (Hewlett-Packard). For all of the radiographs a size of standard image was established, so that there would not be differences among them. After obtaining the images, the analysis was carried out by way of the program Im- ageLab 2000/2.4—a program of analysis and digital pro- cessing/computerized image (Figure 1). Two radiographic points were established in order to evaluate the symmetry of the zygomatic bone from both sides. The first point was defined by the intersection of the nose bones (nasal pyramid) and the nasal septum, being called the nasal point (NP). The second point, called the zygomatic point (ZP), was established from the most sideward point and outside the zygomatic arch. In this way, the operated side (OpS) was compared to the opposite side (OS) in the Treated Group, and in the Control Group, th e right side (RS) and the left side (LS) was compared, in order to obtain fundamental values for the statistical study. The clinical evaluation of the TG was carried out with the intention of determining clinically the possible con- sequences resulting from the surgical procedures, as well as the persistent symptomatology originating from the trauma. Pointing out that in order to do so, only one ob- server was used, and he considered the following pa- rameters for evaluation: ocular movement, dystopia, dip- lopia, paresthesia, limitation of mouth opening, maloc- clusion, discomfort, ectropion, entropion, apparent sclera, enophthalmos, exophthalmos, facial symmetry and the presence of post operative infection. The fifteen patients from the TG were observed in frontal norm, mento-oc- cipital, profile, and supero-inferior. The data obtained was submitted to the test of vari- ance for analysis of normality by the Kolmogorov-Smir- nov test and presented normal distribution, which al- lowed for the carrying out of the parametric t-student test for matched data (p < 0.05). 3. RESULTS In the analysis of the Treated Group (TG), the patients’ ages varied from 21 to 64 years (mean = 33 years). Of these, 87% were men and 13% were women. In relation to the side of the face that had a higher in- cidence of fractures of the zygomatic bone, 67% were on the left side and 33% on the right side. The postoperative Figure 1. Standard scanning posteroanterior X-rays on the program ImageLab 2000 / 2.4. C opyright © 2011 SciRes. OJST 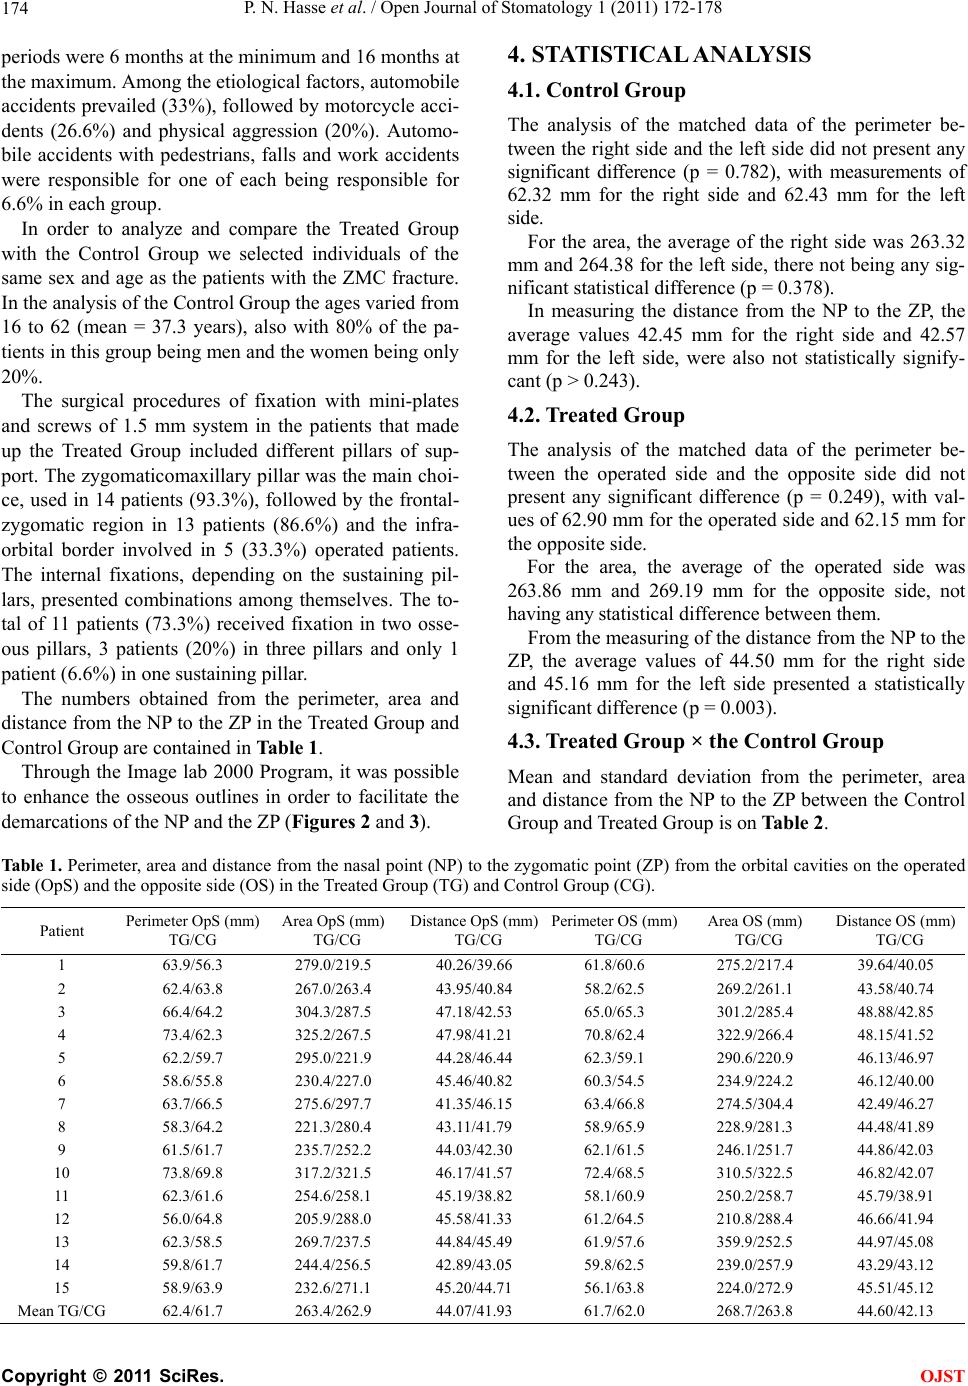 P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 174 periods were 6 months at the minimum and 16 months at the maximum. Among the etiological factors, automobile accidents prevailed (33%), followed by motorcycle acci- dents (26.6%) and physical aggression (20%). Automo- bile accidents with pedestrians, falls and work accidents were responsible for one of each being responsible for 6.6% in each group. In order to analyze and compare the Treated Group with the Control Group we selected individuals of the same sex and age as the patients with the ZMC fracture. In the analysis of the Control Group the ages varied from 16 to 62 (mean = 37.3 years), also with 80% of the pa- tients in this group being men and the women being only 20%. The surgical procedures of fixation with mini-plates and screws of 1.5 mm system in the patients that made up the Treated Group included different pillars of sup- port. The zygomaticomaxillary pillar was the main choi- ce, used in 14 patients (93.3%), followed by the frontal- zygomatic region in 13 patients (86.6%) and the infra- orbital border involved in 5 (33.3%) operated patients. The internal fixations, depending on the sustaining pil- lars, presented combinations among themselves. The to- tal of 11 patients (73.3%) received fixation in two osse- ous pillars, 3 patients (20%) in three pillars and only 1 patient (6.6%) in one sustaining pillar. The numbers obtained from the perimeter, area and distance from the NP to the ZP in the Treated Group and Control Gro up are c ont ai ned in Table 1. Through the Image lab 2000 Program, it was possible to enhance the osseous outlines in order to facilitate the demarcations of the NP and the ZP (Figures 2 and 3). 4. STATISTICAL ANALYSIS 4.1. Control Group The analysis of the matched data of the perimeter be- tween the right side and the left side did not present any significant difference (p = 0.782), with measurements of 62.32 mm for the right side and 62.43 mm for the left side. For the area, the average of the right side was 263.32 mm and 264.38 for the lef t side, there not being any sig- nificant statistical difference (p = 0.378). In measuring the distance from the NP to the ZP, the average values 42.45 mm for the right side and 42.57 mm for the left side, were also not statistically signify- cant (p > 0.243). 4.2. Treated Gr oup The analysis of the matched data of the perimeter be- tween the operated side and the opposite side did not present any significant difference (p = 0.249), with val- ues of 62.90 mm for the operated side and 62.15 mm for the opposite side. For the area, the average of the operated side was 263.86 mm and 269.19 mm for the opposite side, not having any statistical difference between them. From the measuring of the distance from the NP to the ZP, the average values of 44.50 mm for the right side and 45.16 mm for the left side presented a statistically significant difference (p = 0.003). 4.3. Treated Group × the Control Group Mean and standard deviation from the perimeter, area and distance from the NP to the ZP between the Control Group and Treated Group is on Table 2. Table 1. Perimeter, area and distance from the nasal point (NP) to the zygomatic point (ZP) from the orbital cavities on the operated side (OpS) and the opposite side (OS) in the Treated Group (TG) and Control Group (CG). Patient Perimeter OpS (mm) TG/CG Area OpS (mm) TG/CG Distance OpS (mm) TG/CG Perim eter OS (mm) TG/CG Area OS (mm) TG/CG Distance OS (mm) TG/CG 1 63.9/56.3 279.0/219.5 40.26/39.66 61.8/60.6 275.2/217.4 39.64/40.05 2 62.4/63.8 267.0/263.4 43.95/40.84 58.2/62.5 269.2/261.1 43.58/40.74 3 66.4/64.2 304.3/287.5 47.18/42.53 65.0/65.3 301.2/285.4 48.88/42.85 4 73.4/62.3 325.2/267.5 47.98/41.21 70.8/62.4 322.9/266.4 48.15/41.52 5 62.2/59.7 295.0/221.9 44.28/46.44 62.3/59.1 290.6/220.9 46.13/46.97 6 58.6/55.8 230.4/227.0 45.46/40.82 60.3/54.5 234.9/224.2 46.12/40.00 7 63.7/66.5 275.6/297.7 41.35/46.15 63.4/66.8 274.5/304.4 42.49/46.27 8 58.3/64.2 221.3/280.4 43.11/41.79 58.9/65.9 228.9/281.3 44.48/41.89 9 61.5/61.7 235.7/252.2 44.03/42.30 62.1/61.5 246.1/251.7 44.86/42.03 10 73.8/69.8 317.2/321.5 46.17/41.57 72.4/68.5 310.5/322.5 46.82/42.07 11 62.3/61.6 254.6/258.1 45.19/38.82 58.1/60.9 250.2/258.7 45.79/38.91 12 56.0/64.8 205.9/288.0 45.58/41.33 61.2/64.5 210.8/288.4 46.66/41.94 13 62.3/58.5 269.7/237.5 44.84/45.49 61.9/57.6 359.9/252.5 44.97/45.08 14 59.8/61.7 244.4/256.5 42.89/43.05 59.8/62.5 239.0/257.9 43.29/43.12 15 58.9/63.9 232.6/271.1 45.20/44.71 56.1/63.8 224.0/272.9 45.51/45.12 Mean TG/CG 62.4/61.7 263.4/262.9 44.07/41.93 61.7/62.0 268.7/263.8 44.60/42.13 C opyright © 2011 SciRes. OJST 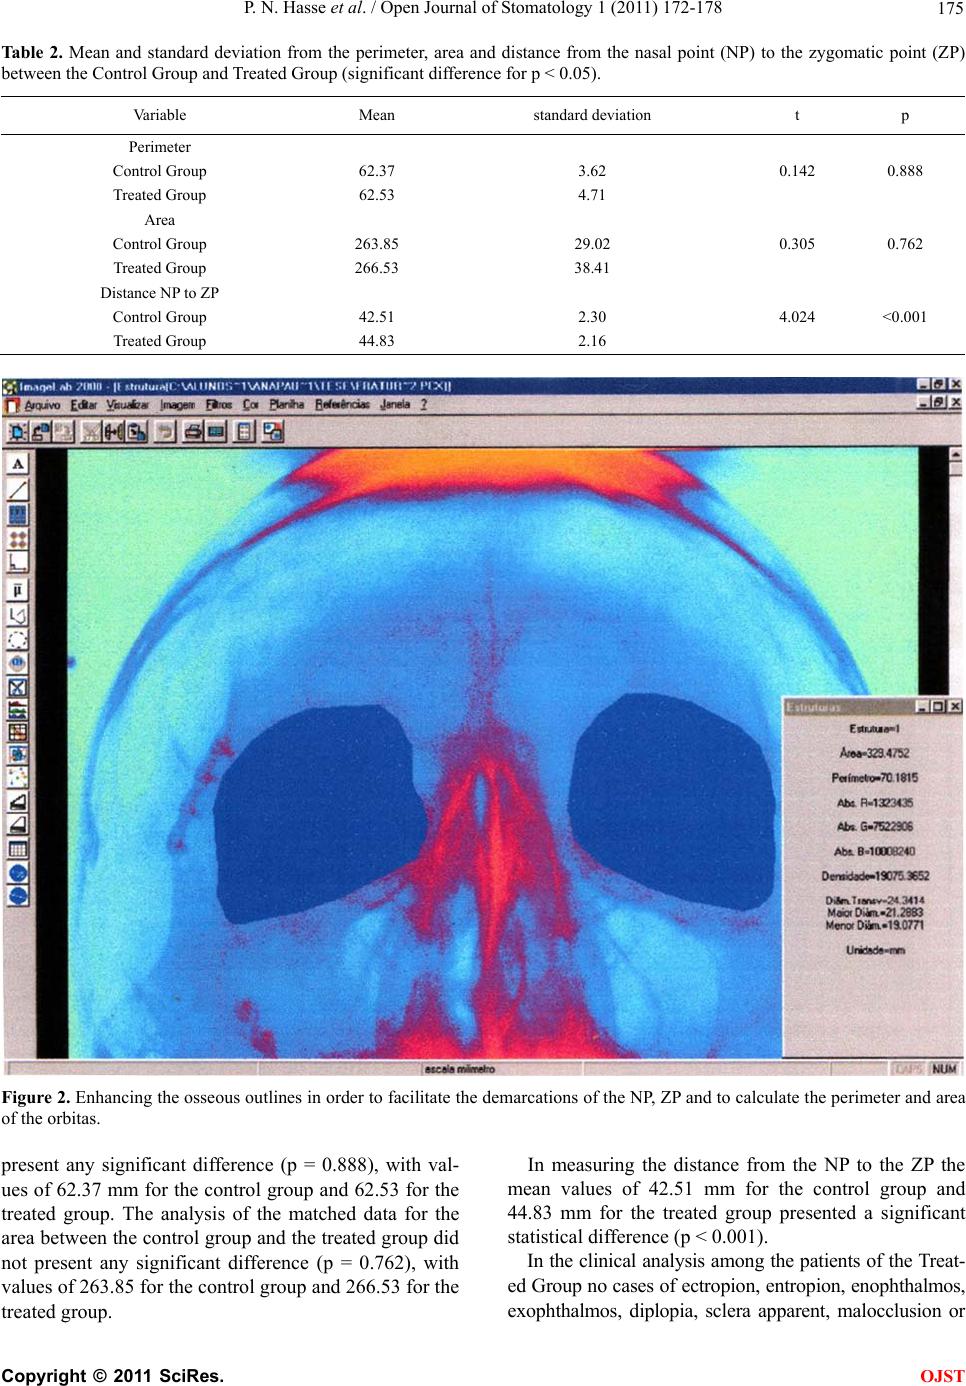 P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 175 Table 2. Mean and standard deviation from the perimeter, area and distance from the nasal point (NP) to the zygomatic point (ZP) between the Control Group and Treated Group (significant difference for p < 0.05). Variable Mean standard deviation t p Perimeter Control Group 62.37 3.62 0.142 0.888 Treated Group 62.53 4.71 Area Control Group 263.85 29.02 0.305 0.762 Treated Group 266.53 38.41 Distance NP t o ZP Control Group 42.51 2.30 4.024 <0.001 Treated Group 44.83 2.16 Figure 2. Enhancing the osseous outlines in order to facilitate the demarcations of the NP, ZP and to calculate the perimeter and area of the orbitas. present any significant difference (p = 0.888), with val- ues of 62.37 mm fo r the control group and 62.5 3 for the treated group. The analysis of the matched data for the area between the control group and the treated group did not present any significant difference (p = 0.762), with values of 263.8 5 for the con trol grou p and 266.53 for the treated group. In measuring the distance from the NP to the ZP the mean values of 42.51 mm for the control group and 44.83 mm for the treated group presented a significant statistical difference (p < 0.001). In the clinical analysis among the patients of the Treat- ed Group no cases of ectropion, entropion, enophthalmos, exophthalmos, diplopia, sclera apparent, malocclusion or C opyright © 2011 SciRes. OJST 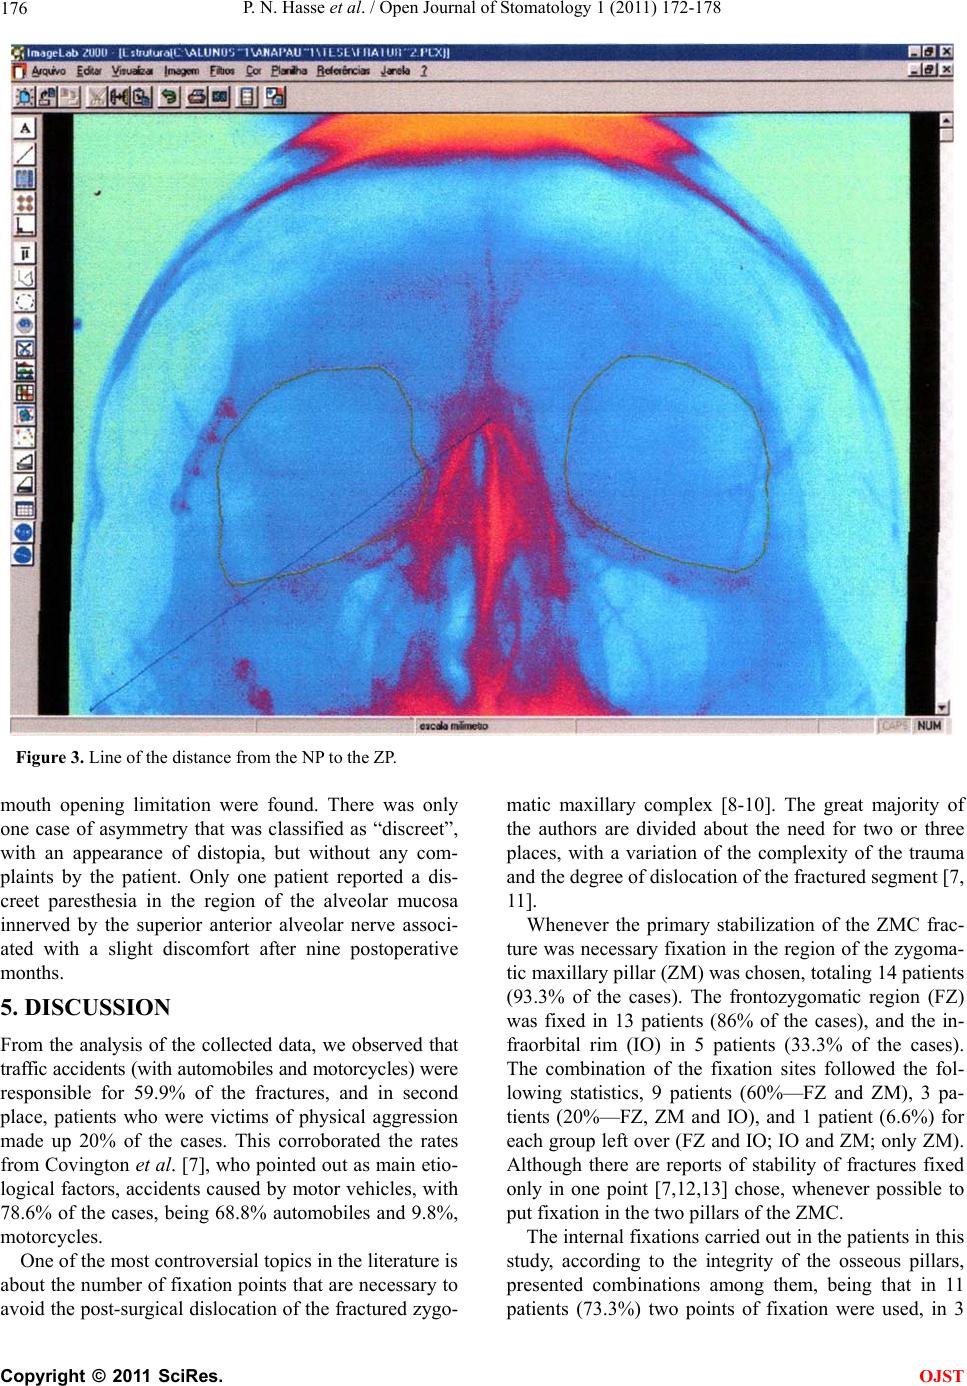 P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 176 Figure 3. Line of the distance from the NP to the ZP. mouth opening limitation were found. There was only one case of asymmetry that was classified as “discreet”, with an appearance of distopia, but without any com- plaints by the patient. Only one patient reported a dis- creet paresthesia in the region of the alveolar mucosa innerved by the superior anterior alveolar nerve associ- ated with a slight discomfort after nine postoperative months. 5. DISCUSSION From the analysis of the collected data, we observed that traffic accidents (with auto mobiles and motorcyc les) were responsible for 59.9% of the fractures, and in second place, patients who were victims of physical aggression made up 20% of the cases. This corroborated the rates from Covington et al. [7], who pointed out as main etio- logical factors, accidents caused by motor vehicles, with 78.6% of the cases, being 68.8% automobiles and 9.8%, motorcycles. One of the most controversial top ics in the literature is about the number of fixation points that are necessary to avoid the post-surgical dislocation of the fractured zygo- matic maxillary complex [8-10]. The great majority of the authors are divided about the need for two or three places, with a variation of the complexity of the trauma and the degree of dislocation of the fractured segment [7, 11]. Whenever the primary stabilization of the ZMC frac- ture was necessary fixation in the region of the zygoma- tic maxillary pillar (ZM) was chosen, totaling 14 patients (93.3% of the cases). The frontozygomatic region (FZ) was fixed in 13 patients (86% of the cases), and the in- fraorbital rim (IO) in 5 patients (33.3% of the cases). The combination of the fixation sites followed the fol- lowing statistics, 9 patients (60%—FZ and ZM), 3 pa- tients (20%—FZ, ZM and IO), and 1 patient (6.6%) for each group left over (FZ and IO; IO and ZM; only ZM). Although there are reports of stability of fractures fixed only in one point [7,12,13] chose, whenever possible to put fixation in the two pillars of the ZMC. The internal fixations carried ou t in the patients in this study, according to the integrity of the osseous pillars, presented combinations among them, being that in 11 patients (73.3%) two points of fixation were used, in 3 C opyright © 2011 SciRes. OJST  P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 177 cases (20%), there was the need for osteossynthesis in three pillars and in only 1 patient (6.6%) one fixation point was used. Davidson et al. [14] analyzed, in an in vitro study, several forms of fixation, combining steel wires, plates and screws, obtaining a total of 25 different combina- tions. By means of traction that simulated the action of the masseter muscles they calculated the rotation and the dislocation after the application of the forces on the dif- ferent planes. The means of fixation that received the best results were: fixation with steel wires in three points and fixation with plates and screws in three points. However, the stability reached by fixation with plates and screws in two points was similar to the previous fixations, highlighting the zygomatic pillar as the strate- gic point for the opposition of the forces of th e masseter muscle. In relation to the combinations and the choice of os- seous pillars, the combination between the frontozygo- matic region and the zygomatic maxillary making up a total of nine (60%) of the fifteen patients treated. The zygomatic maxillary pillar should be the region of choice for unstable fractures of the zygomatic bone, for it acts as a direct antagonist to the action of traction provoked by the masseter muscle [15]. Strong and Sykes [16] propose a combination of sys- tems of mini-plates and micro-plates in the different pil- lars of support of the ZMC. They recommend the use of microplates of 1.0 or 1.2 mm in the infra-orbital border, 1.5 or 1.7 mm in the frontozygomatic region and 2.0 mm in the zygomatic maxillary pillar region. The data obtained from this study are in agreement with the results obtained in other studies [17]. The diffe- rences obtained, for the perimeter as well and for the area of the operated side and the opposite side of the Treated Group were not statistically significant. The good stability obtained from the fixation in two points gains force when compared with the sides obtain- ed from the Control Group, in other words, the patients who did not have fractures of the ZMC. In those we verified that the differences in the values obtained be- tween the right side and the left side, in referring to the perimeter and, as well as the area, were also not statistic- cally significant. The distance from the NP to the ZP was also another variable that was analyzed in this study with the aim to determine a possible zygomatic asymmetry between the opposite side and the treated side (Figure 3). The results showed a significant difference between the sides in the treated group, although the clinical analysis of this data has not been made evident. In the patients from the Treated Group a case of asy- mmetry classified as “discreet” (6.6%) was found, pre- senting dystopia, but with no complaints from the pa- tient. Data that corroborates an incidence from 2% to 9% of facial asymmetry in patients treated by a system of internal rigid fixation [18,19]. However, in these, the system used was of 2.0 mm, that structurally guarantees the smallest rate of deflection, when compared to the system of 1.5 mm. The esthetic-functional items evaluated in this study showed a significant improvement, principally related to the “bother from the use of the plate”, related by the use of the system 2.0 mm. One case was reported with dis- comfort in the region of the zygomatic pillar, however, associated with a symptomatology of disestesia in the re- gion of the mucosa near the region with teeth and not perceptible to palpation. 6. CONCLUSIONS In this study the treatment of the unilateral fractures of the zygomatic maxillary complex with the use of plates and screws of the 1.5 mm system presented good esthe- tic results and low rates of complications. 7. CONFLICT OF INTEREST STATEMENT The authors haven’t any financial and personal relation- ships with other people or organizations that could inap- propriately influence this work. REFERENCES [1] Rohrich, R.J. and Watumull, D. (1995) Comparison of rigid plate versus wire fixation in the management of zygoma fractures: A long-term follow-up clinical study. Plastic and Reconstructive Surgery, 96, 570-575. doi:10.1097/00006534-199509000-00008 [2] Fonseca, R.J., Walker, R.V., Betts, N.J. and Barber, H.D. (1997) Oral and maxillofacial trauma. 2nd Edition, W. B. Sauders, Philadelphia, 652. [3] Zachariades, N., Mezitis, M. and Anagnostopoulos, D. (1998) Changing trends in the treatment of zygomatico- maxillary complex fractures: A 12-year evaluation of methods used. Journal of Oral and Maxillofacial Surgery, 56, 1152-1157. doi:10.1016/S0278-2391(98)90759-5 [4] Luhr, H.G. (1998) A micro-system for cranio-maxillo- facial skeletal fixation. Preliminary report. Journal of Cranio-Maxillofacial Surgery, 16, 312-314. doi:10.1016/S1010-5182(88)80069-6 [5] Reher, P. and Duarte, G.C. (1994) Miniplates in the fron- tozygomatic region. An anatomic study. Journal of Oral and Maxillofacial Surgery, 23, 273-275. doi:10.1016/S0901-5027(05)80107-9 [6] Stevens, M.R. and Menis, M.A. (1993) Microscrew fixa- tion of zygomatic arch fractures. Journal of Oral and Maxillofacial Surgery, 51, 1158-1159. doi:10.1016/S0278-2391(10)80460-4 [7] Covington, D.S., Wainwright, D.J., Teichgraeber, J.F. and Parks, D.H. (1994) Changing pattern in the epidemiology C opyright © 2011 SciRes. OJST  P. N. Hasse et al. / Open Journal of Stomatology 1 (2011) 172-178 Copyright © 2011 SciRes. 178 OJST and treatment of zygoma fractures: 10 year review. Jour- nal of Trauma, 37, 243-248. doi:10.1097/00005373-199408000-00016 [8] Dal, S.F, Ellis, E.III and Throckmorton, G.S. (1992) The effects of zygomatic complex fracture on masseteric muscle force. Journal of Oral and Maxillofacial Surgery, 50, 791-799. doi:10.1016/0278-2391(92)90267-4 [9] Ellis, E.III and Kittidumkerng, W. (1996) Analysis of treatment for isolated zygomatico-maxillary complex fra- ctures. Journal of Oral and Maxillofacial Surgery, 54, 386-400. doi:10.1016/S0278-2391(96)90107-X [10] Rinehart, G.C., Marsh, J.L., Hemmer, K.M. and Bresina, S. (1989) Internal fixation of malar fractures: An experi- mental biophysical study. Plastic and Reconstructive Surgery, 84, 21-28. doi:10.1097/00006534-198907000-00003 [11] Karlan, M.S. and Cassisi, N.J. (1979) Fractures of the zygoma. A geometric, biomechanical, and surgical analy- sis. Archives of Otolaryngology, 105, 320-327. doi:10.1001/archotol.1979.00790180018004 [12] Eisele, D.W. and Duckert, L.G. (1987) Single-point stabi- lization of zygomatic fractures with the minicompression plate. Archives of Otolaryngology—Head & Neck Sur- gery, 113, 267-270. doi:10.1001/archotol.1987.01860030043005 [13] Tarabichi, M. (1994) Transsinus reduction and one-point fixation of malar fractures. Archives of Otolaryngology— Head & Neck Surgery, 120, 620-625. doi:10.1001/archotol.1994.01880300036005 [14] Davidson, J., Nickerson, D. and Nickerson, B. (1991) Zygomatic fractures: Comparison of methods of internal fixation. Plastic and Reconstructive Surgery, 87, 585- 587. [15] Gruss, J.S. and Mackinnon, S.E. (1986) Complex maxil- lary fractures: Role of buttress reconstruction and imme- diate bone grafts. Plastic and Reconstructive Surgery, 78, 9-22. doi:10.1097/00006534-198607000-00002 [16] Strong, E.B. and Sykes, J.M. (1990) Zygoma complex fractures. Facial Plastic Surgery, 14, 105-115. doi:10.1055/s-0028-1085306 [17] Ellis, E.III, El-Attar, A. and Moos, K.F. (1985) An analy- sis of 2067 cases of zygomatico-orbital fracture. Journal of Oral and Maxillofacial Surgery, 43, 417-428. doi:10.1016/S0278-2391(85)80049-5 [18] Sands, T., Symington, O., Katsikeris, N. and Brown, A. (1993) Fractures of the zygomatic complex: A case report and review. Journal of the Canadian Dental Association, 59, 749-757. [19] Schortinghuis, J., Bos, R.R. and Vissink, A. (1999) Com- plications of internal fixation of maxillofacial fractures with microplates. Journal of Oral and Maxillofacial Surgery, 57, 130-135. doi:10.1016/S0278-2391(99)90224-0 |