

Paper Menu >>
Journal Menu >>
 World Journal of AIDS, 2011, 1, 149-154 doi:10.4236/wja.2011.14022 Published Online December 2011 (http://www.SciRP.org/journal/wja) Copyright © 2011 SciRes. WJA 149 Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy Nayana A. Ingole, Seema M. Kukreja, Preeti R. Mehta Microbiology Department, Seth Gordhandas Sunderdas Medical College & King Edward Memorial Hospital, Mumbai, India. E-mail: [email protected] Received August 3rd, 2011; revised September 10th, 2011; accepted September 27th, 2011. ABSTRACT Purpose: For commencement of Antiretroviral Therapy (ART), CD4 count and/or WHO clinical staging is used as the guide in India. In western countries along with clinical and immunological criteria, HIV-1 viral load is also used to start the patient on treatment. Th e present study was conducted to determ ine the role of vira l load in takin g decision on ART commencement in HIV-1 infected treatment naïve individuals. Method: A cross sectional study was carried out at the Integrated Counseling and Testing Centre (ICTC) in the Department of Microbiology at a Tertiary care teaching hospital after Institutional Ethics Committee approval. After obtaining written informed consent, HIV-1 infected pa- tients who were clinically a symptomatic, ART naïve, having CD4 count <250 cells/mm3 and age more th an or equal to 15 yrs were enrolled in this study. Blood sample was collected and viral load was estimated by COBAS® TaqMan® HIV-1 Test. Result: During the study period of one year, 8966 HIV-1 infected patients were referred for CD4 count estimation. Of these 1624 patients had CD4 count <250 cells/mm3 and 405 patients were treatment naïve. Of these 96 (23.70%) patients were clinica lly asymptomatic and were enrolled. Of those enro lled, ten (10.41%) had viral load less than 5000 copies/ml. Co nclusion: Decision to start patient on ART can be made judiciously when viral load is used along with CD4 count estimation. Keywords: Viral Load, CD4 Counts, HIV, Monitoring, ART, Clinically Asymptomatic 1. Introduction In developed countries viral load monitoring along with CD4 count estimation is used to make decision regarding commencement of Antiretroviral Therapy (ART) in an HIV infected individual. Viral load testing is important as a guide for clinical decision making as regards initiation of treatment, swit- ching to second-line treatment and optimizing the dura- tion of the first-line treatment regimen. In addition, the viral load is a particularly useful tool for monitoring ad- herence to treatment, performing sentinel surveillance for new infections/seroconversion, and diagnosing HIV in- fection in children aged <18 months [1]. But for developing countries, World Health Organiza- tion (WHO) recommends starting ART when CD4 count falls below 350 cells/mm3 or when patient is in WHO clinical stage III or IV if CD4 testing is not available [2]. National AIDS Control Organization (NACO) recom- mends initiating therapy when patient is in WHO clinical stage III and IV or when CD4 count < 250 cells/mm3 [3]. Although it is a standard practice in high-income countries, determination of the HIV viral load is not recommended in developing countries because of the costs and technical constraints. But as more and more countries establish capacity to provide second-line ther- apy, and as costs and technological constraints associated with viral load testing decrease, determination of the vi- ral load becomes necessary [1]. Hence, this study was conducted to determine whether performing HIV-1 viral load can lead to better decisions in initiating therapy. 2. Material and Methods A cross sectional study was carried out at the Integrated Counseling and Testing Centre (ICTC) in the department of Microbiology at a Tertiary care teaching hospital. In- stitutional Ethics Committee approval was obtained prior to commencement of the study. HIV-1 infected patients who were clinically asymptomatic, ART naïve, having CD4 count < 250 cells/mm3 and age more than or equal to 15 yrs were enrolled in this study after obtaining writ- ten informed consent. HIV-1 viral load was estimated by  Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy 150 COBAS® TaqMan® HIV-1 test. 2.1. Estimation of HIV Viral Load Principles of the Procedure The COBAS® TaqMan® HIV-1 Test is based on three major processes: 1) manual specimen preparation to ob- tain HIV-1 RNA; 2) automated reverse transcription of the target RNA to generate complementary DNA (cDNA) 3) simultaneous PCR amplification of target cDNA using HIV-1 specific complementary primers, and detection of cleaved dual fluorescent dye-labeled oligonucleotide detection probes that permit quantitation of HIV-1 target amplified product (amplicon) and HIV-1 Quantitation Standard RNA, which is processed, amplified and de- tected simultaneously with the specimen. The test can quantitate HIV-1 RNA over the range of 47 - 10,000,000 copies/mL. 2.2. Specimen Collection and Storage Three ml of venous blood sample was collected in EDTA vacutainer from each subject. Within six hours of collec- tion, the sample was centrifuged at 800 - 1600 × g for 20 minutes at room temperature to separate the plasma. Separated plasma was transferred into sterile polypro- pylene screw cap tube and was stored in frozen form at −70˚C till further use. 2.3. Specimen, Control and Reagent Preparation 1) Frozen plasma specimens were kept at room tempera- ture until completely thawed and were vortexed for 5 - 10 seconds before use. 2) The reagents were allowed to reach ambient tem- perature before proceeding. Heating Block(s) were pre- heated to a temperature of 70˚C (±2˚C) and water bath to a temperature of 50˚C (±2˚C) before starting the purifi- cation reactions. 3) Batches of 21 samples and 3 controls (High positive control, low positive control and negative control) were processed at a time. 2.3.1. Reagent Preparation (For 24 Tests) Reagent preparation was done under a laminar hood 1) The Inhibitor Removal Buffer was prepared by pi- petting 20 ml of 96% - 100% ethanol to Inhibitor Re- moval Buffer (IRB). Mixing was done by inverting 5 - 10 times. 2) The Wash Buffer was prepared by pipetting 80 ml of 96% - 100% ethanol to the Wash Buffer (WASH). Mixing was done by inverting 5 - 10 times. 3) The Elution Buffer (ELB) was preheated at 70˚C (±2˚C) in a 2.0 mL screw-cap microfuge tube. Volume eluted was 4 ml. 4) 0.5 ml of the Elution Buffer (ELB) was pipetted into the Carrier RNA (CAR). Mixing was done by in- verting; then vortexing was done until all of the Carrier RNA was dissolved. 5) 5.0 ml of the Elution Buffer (ELB) was pipeted into the Proteinase K (PK). Mixing was done by inverting; then vortexing was done until all of the Proteinase K was dissolved. 6) The Lysis/Binding Working Solution was prepared by pipetting the volumes listed in the Table 1. The indicated volume of Lysis/Binding Buffer was added to a clean sterile 50 mL tube. The indicated volume of reconstituted Carrier RNA was added to the tube containing the Lysis/Binding Buffer. The HIV-1 QS was vortexed for 3 - 5 seconds and indicated volume of HIV-1 QS was added to the tube containing the Lysis/Binding Buffer and the reconsti- tuted Carrier RNA. Mixing was done by inverting 10 - 15 times. The indicated volume of reconstituted Proteinase K was added to the tube containing the Lysis/Binding Buffer. Mixing was done by inverting 10 - 15 times. 2.3.2. Specimen and Control Preparation Specimen and control preparation was also done under laminar hood. 1) 625 μL of Lysis/Binding Working Solution was pip- peted into each well of the Lysis Rack (I, transparent). 2) 500 μL of specimen or control was pippeted into the appropriate well. 3) After all specimens and controls have been added, mixing was done by vortexing for approximately 10 seconds. 4) The Lysis Rack was incubated in a preheated 50˚C (±2˚C) water bath for 10 minutes. Lysis Rack was dried after removing from water bath. 5) The Lysis Rack was centifuged for 10 - 20 seconds at a setting of 4600 × g in the micro-titer plate centrifuge. 6) 350 μL of isopropanol was pippeted into each well. 7) Specimens were mixed by inverting the rack three times, then vortexing the rack for approximately 10 sec- onds. 8) The Lysis Rack was centrifuged for 10 - 20 seconds Table 1. Preparation of lysis/binding working solution. Reagents 24 Lysis/Binding Buffer (mL) 14.0 Carrier RNA (μL) 280 HIV-1 QS (μL) 168 Proteinase K (mL) 2.8 Copyright © 2011 SciRes. WJA  Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy151 at a setting of 4600 × g in the micro-titer plate centrifuge. 9) Opening one well at a time, 750 μL of specimen or control mixture was transferred to the corresponding wells of the Filter Tube Rack (II, yellow) with affixed Waste Rack (white). 10) After all specimens or controls have been added, the Filter Tube Rack assembly was centrifuged for 2 minutes at 4600 × g in the micro-titer plate centrifuge. 11) Opening one well at a time, the remaining speci- men or control mixture was transferred to the corre- sponding wells of the Filter Tube Rack. 12) The Filter Tube Rack assembly was centrifuged for 2 minutes at 4600 × g in the micro-titer plate centri- fuge. 13) The Filter Tube Rack was replaced with a new Waste Rack. 14) 400 μL of Inhibitor Removal Buffer (IRB) was pippeted down the side of each well. 15) The Filter Tube Rack assembly was centrifuged for 2 minutes at 4600 × g in the micro-titer plate centri- fuge. 16) 700 μL of Wash Buffer (WASH) was pippeted down the side of each well. 17) The Filter Tube Rack assembly was centrifuged for 2 minutes at 4600 × g in the micro-titer plate centri- fuge. 18) The Filter Tube Rack was replaced with a new Waste Rack 19) 700 μL of Wash Buffer (WASH) was pippeted down the side of each well. 20) The Filter Tube Rack assembly was centrifuged for 3 minutes at 4600 × g in the micro-titer plate centrifuge. 21) The Filter Tube Rack was placed onto the Elution Rack (IIIA, blue). 22) 75 μL of the prewarmed Elution Buffer (ELB) was pipette onto the center of each filter without touching the filter. The Elution Rack was incubated at room tempera- ture for a minimum of 3 minutes after adding Elution Buffer to the last well. 23) The Filter Tube Rack assembly was centrifuged for 3 minutes at 4600 × g in the micro-titer plate centrifuge. 24) The Filter Tube Rack was removed from the Elu- tion Rack. 25) The Cover Rack (IIIB, blue) was placed onto the Elution Rack (IIIA, blue). 26) The processed specimens and controls are then used directly for PCR. 2.3.3. Reagent Preparation Reagent preparation was done inside a PCR work station. 1) One vial of HIV-1 MMX and one vial CTM Mn2+ was equilibrated at ambient temperature for 30 minutes. 2) K-carrier was placed in a K-carrier holder. 3) New K-tubes were placed in the K-carrier without touching the sides of the K-tubes. 4) The K-tubes were uncapped using the K-tube Cap- per. 5) The Working MMX was prepared as follows: For 24 tests, 170 μL of CTM Mn2+ was added to one vial of HIV-1 MMX. Mixing was done inverting 10 times. 6) 50 μL of Working MMX was pippeted into each K-tube. 7) 50 μL of each processed specimen and control were added to the appropriate K-tube containing Working MMX using a micropipettor with an aerosol barrier or positive displacement tip. Extracted RNA Reverse transcription, amplification and detection were automatically performed by the CO- BAS® TaqMan® 48 Analyzer. The COBAS® TaqMan® 48 Analyzer: 1) Determined the Cycle Threshold value (Ct) for the HIV-1 RNA and the HIV-1 Quantitation Standard RNA. 2) Determined the HIV-1 RNA titer based upon the Ct values for the HIV-1 RNA and HIV 1 Quantitation Stan- dard RNA and the lot-specific calibration coefficients. 3) Determined that the calculated copies/mL titer for HIV-1 L (+) C and HIV-1 H (+) C fall within the as- signed ranges. 2.4. Interpretation of Results Result was checked for flags and comments to ensure that the run is valid. For a valid run, result for each indi- vidual specimen was interpreted as mentioned in Table 2. 3. Results During the study period of one year from April 2009 to March 2010, 8966 HIV-1 infected patients were referred for CD4 count estimation to our ICTC. Of these, 1624 patients had CD4 count <250 cells/mm3 and 405 patients were treatment naïve. Of these 96 (23.70%) patients were clinically asymptomatic and were enrolled (Figure 1). Of the 96 patients enrolled, 58 were males and 38 were fe- males. Ten patients had viral load <5000 copies/ml. Of these, eight were females and two were males (Table 3). 4. Discussion CD4 count has been reported to be one of the best surro- gate markers for monitoring the progression of HIV in- fection and low CD4 counts are associated with in- creased risk of developing AIDS or death [4]. Contrary to this, in our study 23.70% of patients having CD4 count < 250 cells/mm3 were asymptomatic. Similar findings have been reported by R. Kannangia et al. (2008) where ten (15.2 %) of the 66 patients in CDC category C with CD4 count <200 cells/mm3 were asymptomatic [5]. Thus Copyright © 2011 SciRes. WJA 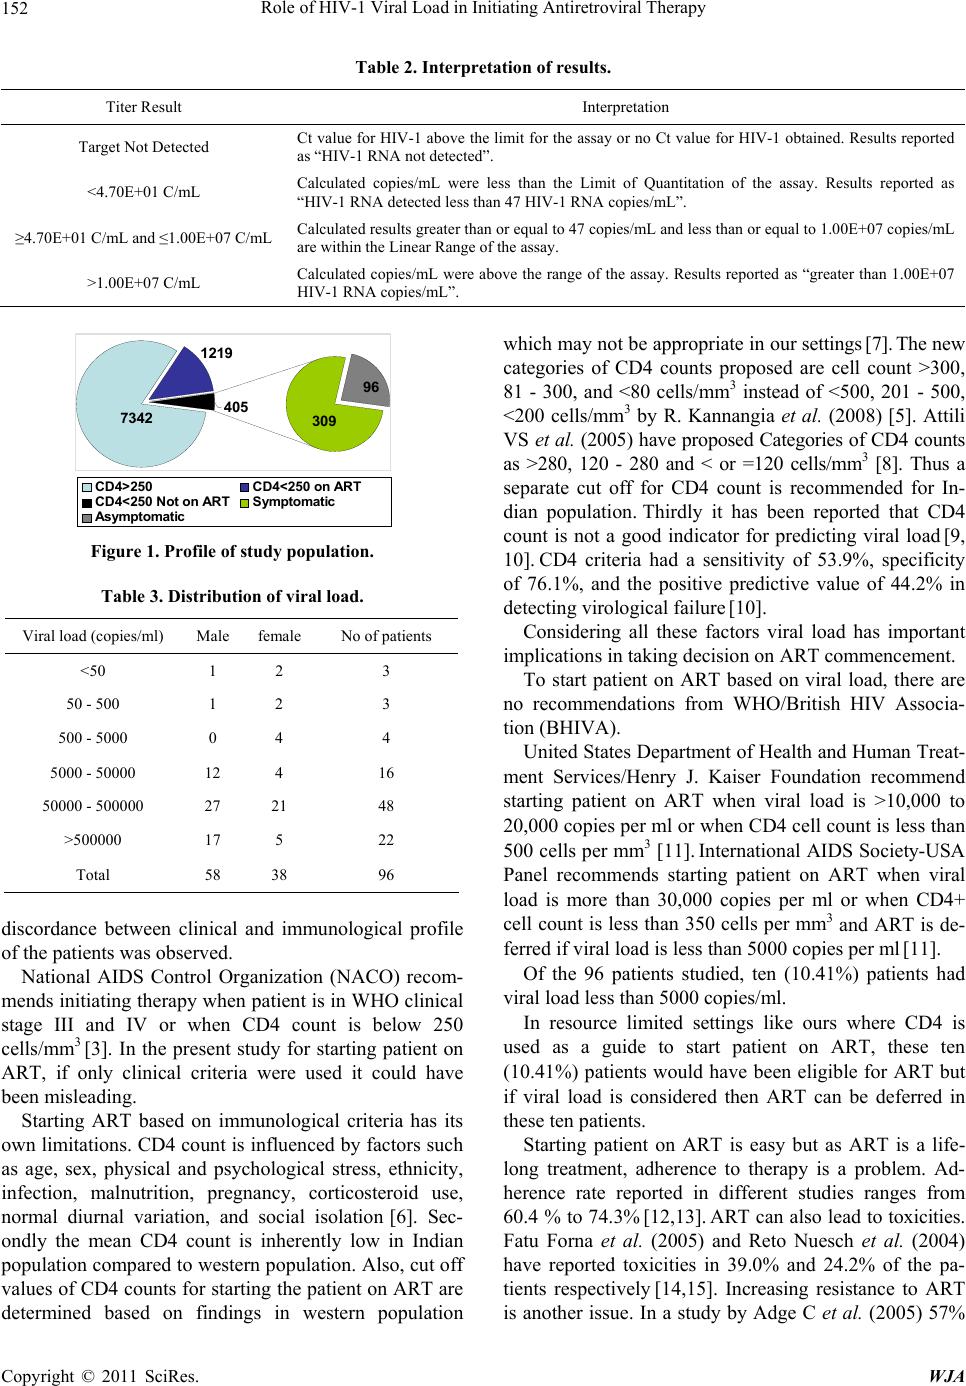 Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy Copyright © 2011 SciRes. WJA 152 Table 2. Interpretation of results. Titer Result Interpretation Target Not Detected Ct value for HIV-1 above the limit for the assay or no Ct value for HIV-1 obtained. Results reported as “HIV-1 RNA not detected”. <4.70E+01 C/mL Calculated copies/mL were less than the Limit of Quantitation of the assay. Results reported as “HIV-1 RNA detected less than 47 HIV-1 RNA copies/mL”. ≥4.70E+01 C/mL and ≤1.00E+07 C/mL Calculated results greater than or equal to 47 copies/mL and less than or equal to 1.00E+07 copies/mL are within the Linear Range of the assay. >1.00E+07 C/mL Calculated copies/mL were above the range of the assay. Results reported as “greater than 1.00E+07 HIV-1 RNA copies/mL”. 7342 1219 309 96 405 CD4>250 CD4<250 on ART CD4<250 Not on ARTSymptomatic Asymptomatic Figure 1. Profile of study population. Table 3. Distribution of viral load. Viral load (copies/ml) Male female No of patients <50 1 2 3 50 - 500 1 2 3 500 - 5000 0 4 4 5000 - 50000 12 4 16 50000 - 500000 27 21 48 >500000 17 5 22 Total 58 38 96 discordance between clinical and immunological profile of the patients was observed. National AIDS Control Organization (NACO) recom- mends initiating therapy when patient is in WHO clinical stage III and IV or when CD4 count is below 250 cells/mm3 [3]. In the present study for starting patient on ART, if only clinical criteria were used it could have been misleading. Starting ART based on immunological criteria has its own limitations. CD4 count is influenced by factors such as age, sex, physical and psychological stress, ethnicity, infection, malnutrition, pregnancy, corticosteroid use, normal diurnal variation, and social isolation [6]. Sec- ondly the mean CD4 count is inherently low in Indian population compared to western population. Also, cut off values of CD4 counts for starting the patient on ART are determined based on findings in western population which may not be appropriate in our settings [7]. The new categories of CD4 counts proposed are cell count >300, 81 - 300, and <80 cells/mm3 instead of <500, 201 - 500, <200 cells/mm3 by R. Kannangia et al. (2008) [5]. Attili VS et al. (2005) have proposed Categories of CD4 counts as >280, 120 - 280 and < or =120 cells/mm3 [8]. Thus a separate cut off for CD4 count is recommended for In- dian population. Thirdly it has been reported that CD4 count is not a good indicator for predicting viral load [9, 10]. CD4 criteria had a sensitivity of 53.9%, specificity of 76.1%, and the positive predictive value of 44.2% in detecting virological failure [10]. Considering all these factors viral load has important implications in taking decision on ART commencement. To start patient on ART based on viral load, there are no recommendations from WHO/British HIV Associa- tion (BHIVA). United States Department of Health and Human Treat- ment Services/Henry J. Kaiser Foundation recommend starting patient on ART when viral load is >10,000 to 20,000 copies per ml or when CD4 cell count is less than 500 cells per mm3 [11]. International AIDS Society-USA Panel recommends starting patient on ART when viral load is more than 30,000 copies per ml or when CD4+ cell count is less than 350 cells per mm3 and ART is de- ferred if viral load is less than 5000 copies per ml [11]. Of the 96 patients studied, ten (10.41%) patients had viral load less than 5000 copies/ml. In resource limited settings like ours where CD4 is used as a guide to start patient on ART, these ten (10.41%) patients would have been eligible for ART but if viral load is considered then ART can be deferred in these ten patients. Starting patient on ART is easy but as ART is a life- long treatment, adherence to therapy is a problem. Ad- herence rate reported in different studies ranges from 60.4 % to 74.3% [12,13]. ART can also lead to toxicities. Fatu Forna et al. (2005) and Reto Nuesch et al. (2004) have reported toxicities in 39.0% and 24.2% of the pa- tients respectively [14,15]. Increasing resistance to ART is another issue. In a study by Adge C et al. (2005) 57%  Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy153 of the patient had genotypic resistance to at least one reverse transcriptase inhibitor (RTI) or protease inhibitor (PI) [16]. In Surveillance on HIV antiretroviral drug re- sistance in treated individuals in England HIV drug re- sistance reported was 55% [17]. Hence, for rationale use of ART, viral load can be a better guide compared to CD4 alone. When viral load and CD4 count both are used for predicting progression to AIDS better estimate of risk of progression is provided compared to when either marker is used alone [18]. Also if baseline viral load is available one can monitor the response to treatment by documenting the fall or rise in viral load [11]. Viral load monitoring is significantly superior to CD4 monitoring in assessing viral suppression and treatment failure in patients on ART [9,10] and as clinical failure is an even later development, defining treatment failure on clinical grounds alone is equally suboptimal [1]. Hence, under the National AIDS Control Programme (NACP), the State Reference Laboratories (SRL) can be given the responsibility of performing baseline viral load estimation and monitoring response to therapy especially in case of suspected drug resistance. In the present study, eight out of 38 females and two out of 58 males had viral load <5000 copies/ml. In a meta-analysis for gender difference in viral load, Sonia Napravnik et al. (2010) observed that a given population of women have, on average, lower plasma HIV RNA levels compared with a population of men with similar CD4 lymphocyte counts and stage of HIV disease [19]. Shade SB et al. (2000) also observed similar gender differences in viral load. Women with advanced HIV disease have slightly lower levels of viral load than men at corresponding levels of CD4+ cell counts [20]. These gender differences in viral load could necessi- tate gender specific recommendations for initiation of ART. Hence when HIV-1 RNA thresholds are used to form treatment recommendations for initiating ART, a lower threshold is likely indicated for women compared with men. To conclude, decision to start patient on ART can be made judiciously when viral load is used along with CD4 count estimation. Also, if baseline viral load value is available it will help in assessing subsequent response to therapy once initiated. Gender differences in viral load necessitate gender specific recommendations for initia- tion of ART. Virological monitoring should be combined with clinical and immunological monitoring for better patient management. REFERENCES [1] A. Calmy, N. Ford, B. Hirschel, S. J. Reynolds, L. Lynen, E. Goemaere, F. G. de la Vega, L. Perrin and W. Rodri- guez, “HIV Viral Load Monitoring in Resource-Limited Regions: Optional or Necessary?” Clinical Infectious Dis- eases, Vol. 44, No. 1, 2007, pp. 128-134. doi:10.1086/510073 [2] WHO, “Antiretroviral Therapy for HIV Infection in Adults and Adolescents, Recommendations for a Public Health Approach 2010 Revision,” 2010. http://whqlibdoc.who.int/publications/2010/97892415997 64_eng.pdf [3] NACO, “Antiretroviral Therapy Guidelines for HIV In- fected Adults and Adolescents Including Post Exposure Prophylaxis,” Ministry of Health and Family Welfare, 2007. http://www.nacoonline.org/upload/Policies%20&%20Gu idelnes/1.%20Antiretroviral%20Therapy%20Guidelines% 20for%20HIVInfected%20Adults%20and%20Adolescent s%20Including%20Post-exposure.pdf [4] Y. Pirzada, S. Khuder and H. Donabedian, “Predicting AIDS-Related Events Using CD4 Percentage or CD4 Absolute Counts,” AIDS Research and Therapy, Vol. 3, 2006, p. 20. doi:10.1186/1742-6405-3-20 [5] R. Kannangai, A. J. Kandathil, D. L. Ebenezer, G. Nithy- anandam, P. Samuel, O. C. Abraham, T. D. Sudarsanam, S. A. Pulimood and G. Sridharan, “Evidence for Lower CD4+ T Cell and Higher Viral Load in Asymptomatic HIV-1 Infected Individuals of India: Implications for Therapy Initiation,” Indian Journal of Medical Microbi- ology, Vol. 26, No. 3, 2008, pp. 217-221. doi:10.4103/0255-0857.42031 [6] M. Irwin, “Low CD4+ T Lymphocyte Counts: A Variety of Causes and Their Implications to a Multifactorial Model of AIDS,” Virusmyth Homepage, 2001. “http://www.virusmyth.com/aids/hiv/milowcd4.htm [7] K. Ray, S. M. Gupta, M. Bala, S. Muralidhar and J. Kumar, “CD4/CD8 Lymphocyte Counts in Healthy, HIV- Positive Individuals & AIDS Patients,” Indian Journal of Medical Research, Vol. 124, 2006, pp. 319-330. [8] V. S. Attili, S. Sundar, V. P. Singh and M. Rai, “Validity of Existing CD4+ Classification in North Indians, in Pre- dicting Immune Status,” Journal of Infection, Vol. 51, No. 1, 2005, pp. 41-46. doi:10.1016/j.jinf.2004.08.022 [9] A. D. Kimmel, M. C. Weinstein, X. Anglaret, S. J. Goldie, E. Losina, Y. Yazdanpanah, E. Messou, K. L. Cotich, R. P. Walensky and K. A. Freedberg, “Monitoring of Anti- retroviral Therapy in Resource-limited Settings: Discus- sion,” Journal of Acquired Immunodeficiency Syndrome, Vol. 54, No. 3, 2010, pp. 258-268. doi:10.1097/QAI.0b013e3181d0db97 [10] B. Boughton, “WHO-Mandated CD4 Monitoring for HIV Shows Poor Sensitivity, Specificity,” 17th Conference on Retroviruses and Opportunistic Infections (CROI), Ab- stract 111, San Francisco, 18 February 2010. http://www.medscape.com/viewarticle/717302 [11] E. Mylonakis, M. Paliou and J. D. Rich, “Plasma Viral Load Testing in the Management of HIV Infection,” American Family Physician, Vol. 63, No. 3, 2001, pp. 483-490. Copyright © 2011 SciRes. WJA  Role of HIV-1 Viral Load in Initiating Antiretroviral Therapy Copyright © 2011 SciRes. WJA 154 [12] M. B. Cauldbeck, C. O’Connor, M. B O’Connor, J. A. Saunders, B. Rao, V. G. Mallesh, N. Kotehalappa, P. Kumar, G. Mamtha, C. McGoldrick, R. B. S. Laing and K. S. Satish, “Adherence to Anti-Retroviral Therapy among HIV Patients in Bangalore, India,” AIDS Research and Therapy, Vol. 6, 2009, p. 7. doi:10.1186/1742-6405-6-7 [13] R. Murri, A. Ammassari, A. De Luca, A. Cingolani, P. Marconi, A. W. Wu and A. Antinori, “Self-Reported Non- adherence with Antiretroviral Drugs Predicts Persistent Condition,” HIV Clinical Trials, Vol. 2, No. 4, 2001, pp. 323-329. doi:10.1310/KDM0-RU5W-NVTW-N9MC [14] F. Forna, C. A. Liechty, P. Solberg, F. Asiimwe, W. Were, J. Mermin, P. Behumbiize, T. Tong, J. T. Brooks and P. J. Weidle, “Clinical Toxicity of Highly Active Antiretrovi- ral Therapy in a Home-Based AIDS Care Program in Ru- ral Uganda,” Journal of Acquired Immunodeficiency Syn- drome, Vol. 44, No. 4, 2007, pp. 456-462. doi:10.1097/QAI.0b013e318033ffa1 [15] R. Nuesch, P. Srasuebkul, J. Ananworanich, K. Ruxrung- tham, P. Phanuphak and C. Duncombe, “Monitoring the Toxicity of Antiretroviral Therapy in Resource Limited Settings: A Prospective Clinical Trial Cohort in Thailand,” Journal of Antimicrobial Chemotherapy, Vol. 58, No. 3, 2006, pp. 637-644. doi:10.1093/jac/dkl313 [16] C. Adje, R. Cheingsong-Popov, T. Roels, G. Djomand, et al., “High Prevalence of Genotypic Antiretroviral (ART) Drug-Resistant HIV-1 Strains among HIV-1-Infected Pa- tients Receiving ART in Abidjan, Ivory Coast,” Confer- ence on Retroviruses and Opportunistic Infections, San Francisco, 30 January - 2 February 2000. http://gateway.nlm.nih.gov/MeetingAbstracts/ma?f=1022 43620.html [17] P. Scott, E. Arnold, B. Evans, A. Pozniak, G. Moyle, M. Shahmenesh, D. White, J. Shirley, P. Cane and D. Pillay, “Surveillance of HIV Antiretroviral Drug Resistance in Treated Individuals in England:1998-2000,” Journal of Antimicrobial Chemotherapy, Vol. 54, No. 3, 2003, pp. 469-473. [18] J. W. Mellors, A. Munoz, J. V. Giorgi, J. B. Margolick, C. J. Tassoni, P. Gupta, L. A. Kingsley, J. A. Todd, A. J. S. R. Detels, J. P. Phair and C. R. Rinaldo Jr., “Plasma Viral Load and CD4+ Lymphocytes as Prognostic Markers of HIV-1 Infection,” Annals of Internal Medicine, Vol. 126, 1997, pp. 946-954. [19] S. Napravnik, C. Poole, J. C. Thomas and J. J. Eron Jr., “Gender Difference in HIV RNA Levels: A Meta-Analy- sis of Published Studies,” Journal of Acquired Immuno- deficiency Syndrome, Vol. 31, No. 1, 2002, pp. 11-19. doi:10.1097/01.QAI.0000026906.47530.AB [20] S. B. Shade, C. Rappoport, D. LeSueur and M. C. Eberly, “Gender Differences in Viral Load: Results from Six Clinical Trials,” International Conference on AIDS, Dur- ban, 9-14 July 2000. http://gateway.nlm.nih.gov/MeetingAbstracts/ma?f=1022 38735.html |