

Paper Menu >>
Journal Menu >>
 Journal of Behavioral and Brain Science, 2011, 1, 229-233 doi:10.4236/jbbs.2011.14029 Published Online November 2011 (http://www.SciRP.org/journal/jbbs) Copyright © 2011 SciRes. JBBS Neur ocysticercosis Association with Cognitive and Aberra n t Behavioural Symptoms: A Case Report and Review Rohit Verma1, Kuljeet Singh Anand2, Mina Chandra1, Neha Prakash2, Ankur Sachdeva1 1Department of Psych iatry, Post Graduate Institute of Medical Education and Research, Dr Ram Manohar Lohia Hospital, New Delhi, India 2Department of Neurology, Post Graduate Institute of Medical Education and Research, Dr Ram Manohar Lohia Hospital, New Delhi, Indi a E-mail: [email protected] Received June 10, 2011; revised July 7, 2011; accepted August 26, 2011 Abstract Neurocysticercosis (NCC) is a leading cause of seizures and epilepsy worldwide. Its clinical manifestations are varied, non specific and pleomorphic, depending on multiple factors. Since NCC mimic large number of neurological disorders, it is important that clinicians should be familiar with these rare presentations to avoid delay in diagnosis and management. We herein describe an unusual case of multiple NCC’s involving entire cortex with only cognitive and behavioural manifestations and review pertinent literature. Keywords: Neurocysticercosis, Dementia, Neuropsychiatric 1. Introduction Neurocysticercosis (NCC) is the common parasitic infes- tation of the central nervous system worldwide. The cli- nical manifestations of NCC are varied and depend on the topography, number, the size and stage of lesions, as well as the status of the host’s immune response to the parasite [1]. While some cases of NCC may remain as- ymptomatic, most have been reported to present seizures, headache, raised intra cranial tension (ICT) due to blockage of CSF flow, stroke, neuropsychiatric symp- toms, ophthalmologic and endocrinological manifesta- tions [2]. Dementia, being the first and only presenting symptom, has been an unusual association with NCC. We herein describe an unusual case of multiple NCC’s involving entire cortex with only cognitive and behav- ioural manifestations and review pertinent literature. 2. Case Report A 44 year old non-diabetic, normotensive non-vegetarian male of middle socio economic status, educated up to higher secondary, presented acute onset behavioral disturbances and forgetfulness for two and half month. The symptoms started after a mild continuous fever of 4 days followed by B/L fronto-temporal headache which was followed few days later by abrupt onset inappropriate behaviour like walking in circles on bed, patting his body parts, and shouting inappropriately. Patient would not stop despite the efforts of family members. He received some medi- cations from a nearby hospital (records not available) but they showed no improvement but only put pati ent t o sleep. In a few days, patient started g iving inappropriate response to asked questions, irrelevan t and abusive talking . Patient had become irritable and started exhibiting symptoms of forgetfulness like difficulty finding rooms in his own house, unable to find way back home from known places. Patient seemed confused most of the time and disoriented to time and place. His activities o f daily living were affected and he needed constant nagging to carry out work. He was also not able to maintain hygiene. Patient would wander inside and outside the hou se for no reason. His sleep du- ration was decreased with difficulty in initiating sleep. There was no history suggestive of coronary artery dis- ease, cerebro-vascular disease, trauma, blood transfusion, joint pain, rashes, photosensitivity, seizure-like activity, and substance use. The pati e n t did not gi ve a ny history of loss of consciousness, vomiting, dysphagia, dysarthria, gait ataxia or any weakness. There was no history of any perceptual disturbances, delusion, suspiciousness, or de- pressed mood. There was no past or family history of any similar, psychiatric or neurological illness. His premor- bid personality was well adjusted. The general physical examination was normal. Visual acuity, including pupils, intraocular pressure and ocular fundi were normal. Both upper and lower limb bulk, power, 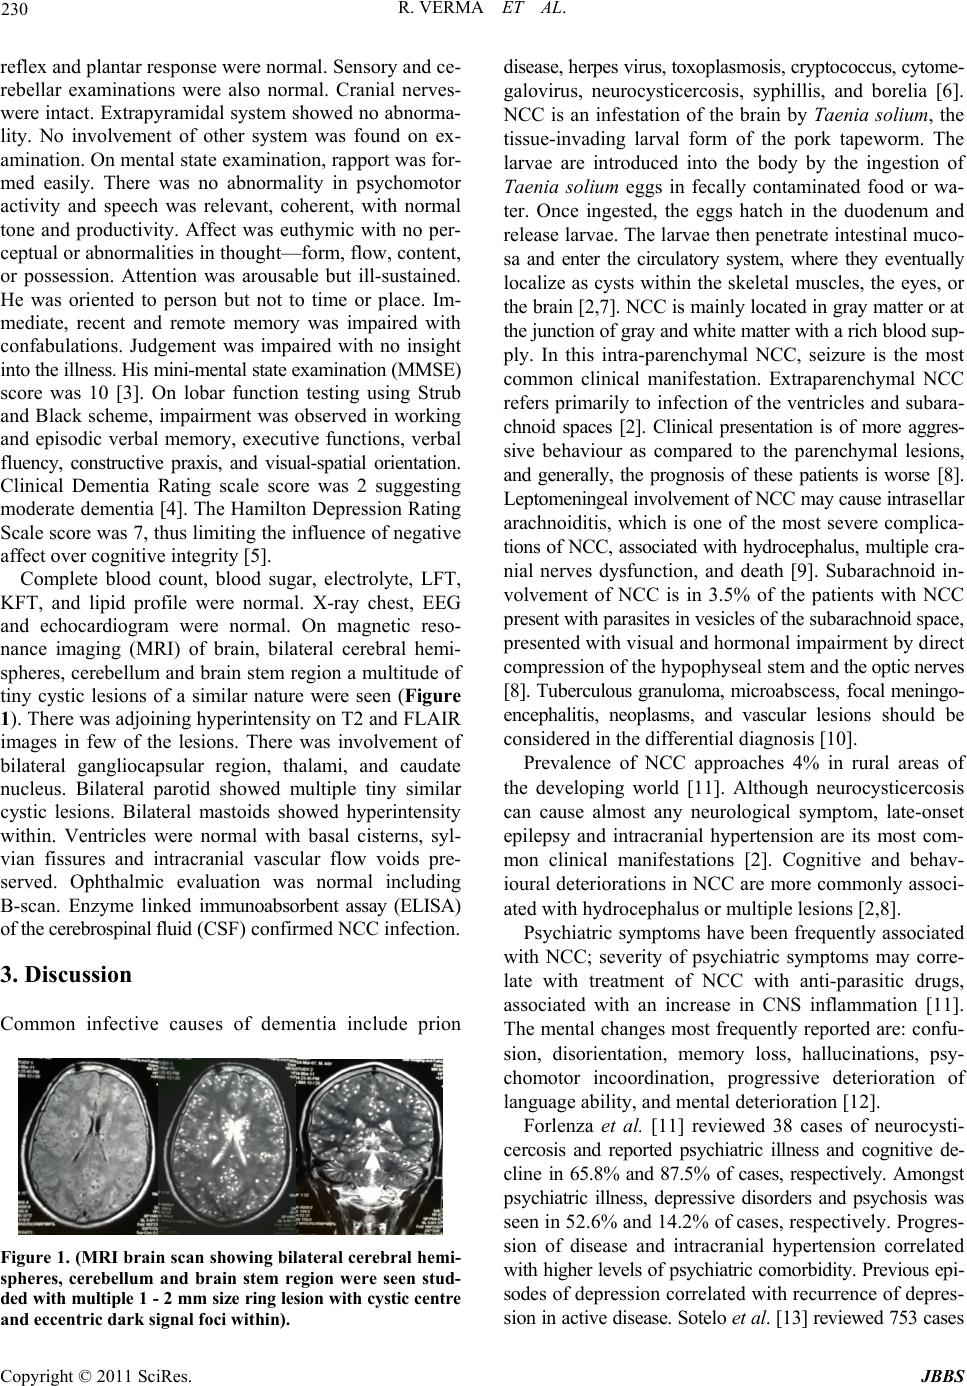 R. VERMA ET AL. 230 reflex and plantar response were normal. Sensory and ce- rebellar examinations were also normal. Cranial nerves- were intact. Extrapyramidal system showed no abnorma- lity. No involvement of other system was found on ex- amination. On mental state examination, rapport was for- med easily. There was no abnormality in psychomotor activity and speech was relevant, coherent, with normal tone and productivity. Affect was euthymic with no per- ceptual or abnormalities in though t—form, flow, con tent, or possession. Attention was arousable but ill-sustained. He was oriented to person but not to time or place. Im- mediate, recent and remote memory was impaired with confabulations. Judgement was impaired with no insight into the illness. His mini-mental state examination (MMSE) score was 10 [3]. On lobar function testing using Strub and Black scheme, impairment was observed in working and episodic verbal memory, executive functions, verbal fluency, constructive praxis, and visual-spatial orientation. Clinical Dementia Rating scale score was 2 suggesting moderate dementia [4]. The Hamilton Depression Rating Scale score was 7, thus limiting the influence of negative affect over cognitive integrity [5]. Complete blood count, blood sugar, electrolyte, LFT, KFT, and lipid profile were normal. X-ray chest, EEG and echocardiogram were normal. On magnetic reso- nance imaging (MRI) of brain, bilateral cerebral hemi- spheres, cerebellum and brain stem region a multitude of tiny cystic lesions of a similar nature were seen (Figure 1). There was adjoin ing hyperinten sity on T2 and FLAIR images in few of the lesions. There was involvement of bilateral gangliocapsular region, thalami, and caudate nucleus. Bilateral parotid showed multiple tiny similar cystic lesions. Bilateral mastoids showed hyperintensity within. Ventricles were normal with basal cisterns, syl- vian fissures and intracranial vascular flow voids pre- served. Ophthalmic evaluation was normal including B-scan. Enzyme linked immunoabsorbent assay (ELISA) of the cerebrospinal fluid (CSF) confirmed NC C infection. 3. Discussion Common infective causes of dementia include prion Figure 1. (MRI brain scan showing bilateral cerebral hemi- spheres, cerebellum and brain stem region were seen stud- ded with multip le 1 - 2 mm size ring lesion with cy stic centre and eccentric dark signal foci within). disease, herpes virus, toxoplasmosis, cryptococcus, cytome- galovirus, neurocysticercosis, syphillis, and borelia [6]. NCC is an infestation of the brain by Taenia solium, the tissue-invading larval form of the pork tapeworm. The larvae are introduced into the body by the ingestion of Taenia solium eggs in fecally contaminated food or wa- ter. Once ingested, the eggs hatch in the duodenum and release larvae. The larvae then penetrate intestinal muco- sa and enter the circulatory system, where they eventually localize as cysts within the skeletal muscles, the eyes, or the brain [2,7]. NCC is mainly lo cated in gray matter or at the junction of gray and white matter with a rich blood sup- ply. In this intra-parenchymal NCC, seizure is the most common clinical manifestation. Extraparenchymal NCC refers primarily to infection of the ventricles and subara- chnoid spaces [2]. Clinical presentation is of more aggres- sive behaviour as compared to the parenchymal lesions, and generally, the prognosis of these patients is worse [8]. Leptomeningeal involvement of NCC may cause intrasell a r arachnoiditis, which is one of the most severe complica- tions of NCC, associated with hydrocephalus, multiple cra- nial nerves dysfunction, and death [9]. Subarachnoid in- volvement of NCC is in 3.5% of the patients with NCC presen t with parasites in vesicles of the subarachnoid space, presented with visual and hormonal impairment by direct compression of the hypophyseal ste m and the optic nerves [8]. Tuberculous granuloma, microab sc es s, focal meningo- encephalitis, neoplasms, and vascular lesions should be considered in the differential diagnosis [10]. Prevalence of NCC approaches 4% in rural areas of the developing world [11]. Although neurocysticercosis can cause almost any neurological symptom, late-onset epilepsy and intracranial hypertension are its most com- mon clinical manifestations [2]. Cognitive and behav- ioural deteriorations in NCC are more commonly associ- ated with hydrocephalus or multiple lesions [2,8]. Psychiatric symptoms have been frequently associated with NCC; severity of psychiatric symptoms may corre- late with treatment of NCC with anti-parasitic drugs, associated with an increase in CNS inflammation [11]. The mental changes most frequently reported are: confu- sion, disorientation, memory loss, hallucinations, psy- chomotor incoordination, progressive deterioration of language ability, and mental deterioration [12]. Forlenza et al. [11] reviewed 38 cases of neurocysti- cercosis and reported psychiatric illness and cognitive de- cline in 65.8% and 87.5% of cases, respectively. Amongst psychiatric illness, depressive disorders and psychosis was seen in 52.6% and 14.2% of cases, respectively. Progres- sion of disease and intracranial hypertension correlated with h igher levels of psychi atric como rbidity. Pr evious ep i- sodes of depression correlated with recurrence of depres- s ion in act ive dise ase. Sote lo et al. [13] reviewed 753 case s Copyright © 2011 SciRes. JBBS  231 R. VERMA ET AL. and reported intellectual deterioration in 15.8%, psycho- sis in 4.7%, and behavioral disturbance in 2.7%. These s ympto ms w ere mor e commo n wi th hyd roceph alus o r mul - tiple lesions. In a review of 23 cases, Loo and Braude found that in 56%, the presenting symptom was psychi- atric, while abnormal mental status examination results were a presenting sign in 43% [14]. McCormick et al. [15] reviewed 127 cases and found that 38% had intrac- ranial hypertension; 10% had increased intracranial pres- sure and dementia. In a review of 17 cases, Grisolia and Wiederholt reported that 18% exhibited altered mental status because of increased intracranial pressure [16]. Scharf reviewed 238 cases; at some point during the course of illness, 33% experienced altered mental status [17]. Two percent presented with dementia, 3% with psycho- sis. Wadia et al. reported three cases of disseminated cysticercosis (involving brain and muscle tissue); all ex- hibited dementia, and two cases experienced psychosis [18]. Ther e are a lso c ase re ports of v aried presentatio n of NCC including pure motor hemiparesis, alexia and manic episodes [19-22]. Dixon and Lipscomb reported schizophrenic and manic- like episodes as possible initial signs of neurocysticerco- sis and found only 5 cases of true dementia in 450 patients (1.1%) [23]. Andrade et al. [24] in a cross-sectional con- trolled study reported dementia in 5 (12.5%) of 40 pa- tients with NCC and attributed this to a synergistic inter- action of cysticercus lesions and local inflammation. In their view, antiepileptic drug use and seizure frequency could not account for the cognitive features. They found no correlation between cognitive scores and number, lo- calization, or type of NCC lesions on MRI. Rosselli et al. [25] reported a severe case of dementia associated with a parenchymous miliary neurocysticercosis without motor seizures whose EEG showed epileptic-like focal dis- charges. The clinical presentation was of headaches, as- sociated with apathy, poor school work and finally hallu- cinations, confusion and excitement in apparently par- oxysmal episodes. Diagana et al. [26] studied cognitive impairment in an Ecuadorian urban Andean community known to be an endemic zone for Taenia solium taeniasis and cysticercosis. In a sample of 227 adults over the age of 40 years assessed using Mini mental state tests (MMS), the overall prevalence of cognitiv e impairment was 8.4% (19/227). In the elderly above the age of 75 years the prevalence of cognitive impairment was 23.5%. The au- thors linked this high prevalence of dementia to the en- demic nature of Taenia solium taeniasis and cysticercosis in this community. The authors postulated that parasitic encephalopathy which was present in 20% persons in this Andean community could play a part in early dam- age of cognitive function and hence result in such high prevalence of dementia. The single case report of NCC presenting only dementia as per our knowledge was by Jha and Ansari [27]. Various pathophysiological mechanisms have been sug- gested to explain the symptom production by NCC infec- tion. Fuentes suggested that psychiatric symptoms asso- ciated with NCC were not due to the direct effect of the parasite on a definite region of the brain but were rather related to mechanical alterations in CSF pressure. More- over, inflammatory injury of the brain parenchyma may also play some role [28]. Parasites may induce expres- sion of several classes of genes in the CNS of the host and exceeds the gene expression seen in inflammatory processes. These genes encode proteins or neuropeptides involved in the regulation of vital physiologic and be- havioral processes, which have led to the behavioral ma- nipulation hypothesis [29,30]. It has been observed that NCC affects brain regions that are distant from the loca- tion of the cysticerci [31]. Thus location of lesion itself appears insufficient to caus e cognitive changes. Dementia syndrome observed in patients with NCC could be a combined effect, resulting from multiple pa- rasitic and vascular lesions, disrupting frontal-parietal-tem- poral networks related to intellectual functioning in pa- tients with vulnerable brains (because of repeated epilep- tic seizures, low educational levels, advanced age) [32]. One study suggests that dementia occurs frequently in patients with untreated NCC, and it is reversible in most cases [32]. Most studies for evaluating cognition in NCC have taken patients having associated seizures and their influence over assessment is indeed a bias. Dementia as an initial presentation of NCC is a rare occurrence, and even rarer is its occurrence solely. The case described here is of a miliar cysticercosis, affecting both cortical and subcortical structures within the cere- bral parenchyma. Our case did not present with any of the common symptoms of NCC and the diagnosis was made on the basis of MRI and ELISA reports. 4. Conclusions We describe a 44-year-old man with a multiple NCC stud- ded over whole cortex. Patients with unusual clinical ma- nifestations should be investigated more thoroughly. NCC should be considered in the differential diagnosis of pa- tients presenting with cognitive and disorganised behav- ioural symptoms in absence of any other psychopatho- logy even in absence of gross neurological signs. Prompt intervention is also recommended for accurate diagnosis, to prevent progression of the disease, and to avoid ire- versible loss of the cognitive functions. 5. References [1] O. H. Del Brutto, V. Rajshekhar, A. C. White Jr., V. C. Tsang, T. E. Nash, O. M. Takayanagui, et al., “Proposed Copyright © 2011 SciRes. JBBS  R. VERMA ET AL. 232 Di agnostic Criteria for Neurocy sticercosis,” Neurology, Vol . 57, No. 2, 2001, pp. 177-183. [2] H. H. Garcia and O. H. Del Brutto, “Neurocysticercosis: Updated Concepts about an Old Disease,” Lancet Neu- rology, Vol. 4, No. 10, 2005, pp. 653-661. doi:10.1016/S1474-4422(05)70194-0 [3] M. F. Folstein, S. E. Folstein and P. R. McHugh, ““Mini-Mental State”: A Practical Method for Grading the Cognitive State of Patients for the Clinician,” Journal of Psychiatric Research, Vol. 12, No. 3, 1975, pp. 189- 198. doi:10.1016/0022-3956(75)90026-6 [4] J. C. Morris, “The Clinical Dementia Rating (CDR): Cur- rent Version and Scoring Rules,” Neurology, Vol. 43, 1993, pp. 2412-2414. [5] M. Hamilton, “A Rating Scale for Depression,” Journal of Neurology, Neurosurgery and Psychiatry, Vol. 23, No. 1, 1960, pp. 56-62. doi:10.1136/jnnp.23.1.56 [6] O. P. Almeida and N. T. Lautenschlager, “Dementia As- sociated with Infectious Diseases,” International Psy- chogeriatric, Vol. 17, Suppl. 1, 2005, pp. 65-77. doi:10.1017/S104161020500195X [7] A. Carpio, “Neurocysticercosis: An Update,” The Lancet Infectious Diseases, Vol. 2, No. 12, 2002, pp. 751-762. doi:10.1016/S1473-3099(02)00454-1 [8] S. Sinha and B. S. Sharma, “Neurocysticercosis: A Re- view of Current Status and Management,” Journal of Clinical Neuroscience, Vol. 16, No. 7, 2009, pp. 867-876. doi:10.1016/j.jocn.2008.10.030 [9] N. Arriada-Mendicoa, M. A. Celis-López, J. Higuera- Calleja and T. Corona-Vázquez, “Imaging Features of Se- llar Cysticercosis,” American Journal of Neuroradiology, Vol. 24, No. 7, 2003, pp. 1386-1389. [10] V. Rajshekhar, R. P. Haran, G. S. Prakash and M. J. Chandy, “Differentiating Solitary Small Cysticercus Granulomas and Tuberculomas in Patients with Epilepsy. Clinical and Computerized Tomographic Criteria,” Jour- nal of Neurosurgery, Vol. 78, No. 3, 1993, pp. 402-407. doi:10.3171/jns.1993.78.3.0402 [11] O. V. Forlenza, A. H. Filho, J. P. Nobrega, L. dos Ramos Machado, N. G. de Barros, C. H. de Camargo, et al., “Psychiatric Manifestations of Neurocysticercosis: A Study of 38 Patients from a Neurology Clinic in Brazil,” Jour- nal of Neurology, Neurosurgery & Psychiatry, Vol. 62, No. 6, 1997, pp. 612-616. doi:10.1136/jnnp.62.6.612 [12] F. Cendes and M. Ferreira, “Manifestacoes Psiquiatricas da Neurocisticercose,” Jornal Brasileiro de Psiquiatria, Vol. 35, No. 2, 1986, pp. 101-106. [13] J. Sotelo, V. Geurrero and F. Rubio, “Neurocysticercosis: A New Classification Based on Active and Inactive Forms,” Archives of Internal Medicine, Vol. 145, No. 3, 1985, pp. 442-445. doi:10.1001/archinte.145.3.442 [14] L. Loo and A. Braude, “Cerebral Cysticercosis in San Diego: A Review of 23 Cases and a Review of the Lite ra - Ture,” Medicine, Vol. 61, No. 6, 1982, pp. 341-359. [15] G. F. McCormick, C. S. Zee and J. Heiden, “Cysticerco- sis Cerebri: Review of 127 Cases,” Archives of Neurology, Vol. 39, No. 9, 1982, pp. 534-539. [16] J. S. Grisolia and W. C. Wiederholt, “CNS Cysticerco- sis,” Archives of Neurology, Vol. 39, No. 9, 1982, pp. 540-544. [17] D. Scharf, “Neurocysticercosis: Two Hundred Thirty- Eight Cases from a California Hospital,” Archives of Ne- urology, Vol. 45, No. 7, 1988, pp. 777-780. [18] N. Wadia, S. Desai and M. Bhatt, “Disseminated Cysti- cercosis: New Observations, Including CT Scan Findings and Experience with Treatment by Praziquantel,” Brain, Vol. 111, No. 3, 1988, pp. 597-614. doi:10.1093/brain/111.3.597 [19] F. Barinagarrementeria and O. H. Del Brutto, “Neurocys- ticercosis and Pure Motor Hemiparesis,” Stroke, Vol. 19, No. 9, 1988, pp. 1156-1158. doi:10.1161/01.STR.19.9.1156 [20] B. N. Mishra and S. P. Swain, “Psychiatric Morbidity Following Neurocysticercosis,” Indian Journal of Psy- chiatry, Vol. 46, No. 3, 2004, pp. 268-269. [21] A. Verma, N. N. Singh and S. Misra, “Transitory Alexia without Agraphia: A Disconnection Syndrome Due to Neurocysticercosis,” Neurology India, Vol. 52, No. 3, 2004, pp. 378-379. [22] D. K. Pal, A. Carpio and J. W. A. S. Sander, “Neurocys- ticercosis and Epilepsy in Developing Countries,” Jour- nal of Neurology, Neurosurgery & Psychiatry, Vol. 68, No. 2, 2000, pp. 137-143. doi:10.1136/jnnp.68.2.137 [23] H. B. F. Dixon and F. M. Lipscornbe, “Cysticercosis: An Analysis and Follow-Up of 450 Cases,” Medical Re- search Council Special Report Series No. 299, Her Ma- jesty’s Stationery Office, London, 1961. [24] D. Ciampi de Andrade, C. L. Rodrigues, R. Abraham, L. H. Castro, J. A. Livramento, L. R. Machado, et al., “Cog- nitive Impairment and Dementia in Neurocysticercosis: A Cross-Sectional Controlled Study,” Neurology, Vol. 74, No. 16, 2010, pp. 1288-1295. doi:10.1212/WNL.0b013e3181d9eda6 [25] A. Rosselli, M. Rosselli, A. Ardila and B. Penagos, “Se- vere Dementia Associated with Neurocysticercosis,” In- ternational Journal of Neuroscience, Vol. 41, No. 1-2, 1988, pp. 87-95. [26] M. Diagana, M. E. Cruz, A. Tabo, I. Cruz, M. Dumas and P. M. Preux, “Cognitive Disorders in an Andean Com- munity Located in a Cysticercosis Endemic Zone of Ec- uador,” Medecine Tropicale, Vol. 65, No. 4, 2005, pp. 343-345. [27] S. Jha and M. K. Ansari, “Dementia as the Presenting Manifestation of Neurocysticercosis: A Report of Two Patients,” Neurology Asia, Vol. 15, No. 1, 2010, pp. 83- 87. [28] A. Biswas, A. Prasad and K. S. Anand, “Cysticercal De- Mentia,” Journal of Association of Physicians of India, Vol. 46, No. 6, 1998, p. 569. [29] R. M. Ho ek , R. E. va n K es te re n, A . B . S mit , M . d e J ong- Brink and W. P. Geraerts, “Altered Gene Expression in the Host Brain Caused by a Trematode Parasite: Neuropeptide Copyright © 2011 SciRes. JBBS  R. VERMA ET AL. Copyright © 2011 SciRes. JBBS 233 Genes Are Preferentially Affected during Parasitosis,” Proceedings of the National Academy of Sciences of the United States of America, Vol. 94, No. 25, 1997, pp. 14072-14076. doi:10.1073/pnas.94.25.14072 [30] A. Vyas, S. K. Kim, N. Giacomini, J. C. Bo oth roy d a n d R. M. Sapolsky, “Behavioral Changes Induced by Toxoplas- ma Infection of Rodents Are Highly Specific to Aversion of Cat Odors,” Proceedings of the National Academy of Sciences of the United States of America, Vol. 104, No. 15, 2007, pp. 6442-6447. doi:10.1073/pnas.0608310104 [31] M. M. Bianchin, T. R. Velasco, O. M. Takayanagui and A. C. Sakamoto, “Neurocysticercosis, Mesial Temporal Lobe Epilepsy, and Hippocampal Sclerosis: An Associa- tion Largely Ignored,” Lancet Neurology, Vol. 5, No. 1, 2006, pp. 20-21. doi:10.1016/S1474-4422(05)70269-6 [32] J. Ramirez-Bermudez, J. Higuera, A. L. Sosa, E. Lopez- Meza, M. Lopez-Gomez and T. Corona, “Is Dementia Reversible in Patients with Neurocysticercosis?” Journal of Neurology, Neurosurgery & Psychiatry, Vol. 76, No. 8, 2005, pp.1164-1166. doi:10.1136/jnnp.2004.052126 |