

Paper Menu >>
Journal Menu >>
 Open Journal of Stomatology, 2011, 1, 69-74 doi:10.4236/ojst.2011.13012 Published Online September 2011 (http://www.SciRP.org/journal/OJST/ OJST ). Published Online September 2011 in SciRes. http://www.scirp.org/journal/OJST Swallowing threshold parameters of subjects with complete dentures and overdentures Dick J. Witter1, F. Anneke Tekamp1, Ad P. Slagter2, Cees M. Kreulen1, Nico H. J. Creugers1* 1Department of Oral Function and Prosthetic Dentistry, College of Dental Science, Radboud University Nijmegen Medical Centre, Nijmegen, The Netherlands; 2Department of Special Dental Care, Leeuwarden Medical Centre, Leeuwarden, The Netherlands. Email: *[email protected]; [email protected]; [email protected]; [email protected]; [email protected] Received 29 June 2011; revised 15 August 2011; accepted 27 August 2011. ABSTRACT Aim: To compare the chewing process and swallow- ing threshold parameters of subjects with complete dentures and overdentures with data obtained from subjects with complete natural dentitions. Method- ology: The chewing process in terms of swallowing threshold parameters of four groups of subjects with complete dentures (all females) was quantified by sieving particles after chewing of an artificial test ‘food’ and compared with that of subjects with com- plete natural dentitions as a reference group (33 sub- jects). All subjects (except those of the reference group) had a complete denture in the upper jaw. Re- garding the lower jaw two groups with complete dentures (with high (24 subjects), respectively low mandible (12 subjects)) and two groups with over- dentures (implant-retained (22 subjects), respectively natural root supported (19 subjects)) were composed. Results: The ‘overdenture-implants’ group needed significantly more chewing cycles and time (mean: 45 cycles in 32 seconds) until ‘swallowing’ compared to the group with complete natural dentitions (mean: 26 cycles in 19 seconds until ‘swallowing’). Also the ‘complete denture-low mandible’ group needed sig- nificantly more cycles and time (mean: 52 cycles in 44 seconds) until ‘swallowing’ than the complete denti- tion group. In the ‘overdenture-natural roots’ group these outcomes (33 cycles in 24 seconds) were not significantly different compared with the complete dentition group. The ‘complete denture-high mandi- ble’ group (32 cycles in 26 seconds) needed not sig- nificantly more cycles until ‘swallowing’, however time until ‘swallowing’ was significantly longer com- pared to the complete dentition group. All denture groups had significantly larger mean particle sizes when ‘swallowing’ (sizes in the order of 3 mm) than the natural dentition group (about 2 mm). Conclu- sion: Despite efforts to compensate for a reduced chewing efficiency, subjects with complete dentures (including overdentures) had 50% larger median par- ticle sizes when ‘swallowing’ compared to subjects with complete natural dentitions. Keywords: Swallowing Threshold; Chewing Efficiency; Complete Denture; Overdenture; Oral Implant 1. INTRODUCTION Chewing efficiency can be defined as the capacity to pulverize food particles during a given number of chew- ing cycles, for instance to half of the original particle size [1]. Regarding particle size reduction during chew- ing, it has been stated that “denture wearers reach only 25% of dentate chewing performance” [2], and “chewing efficiency of denture wearers is less than one-sixth that of subjects with a dentition” [3]. However, chewing effi- ciency is only one parameter in the chewing process and depends of variables such as bite force, salivary flow and dental status including prosthodontic status. In order to describe the chewing process as a whole, the number of chewing cycles and the time needed until swallowing are also relevant parameters together with the result of the chewing process, i.e. the particle size reduction until subjects feel the urge to swallow. These parameters have been referred as swallowing threshold parameters [4,5]. Swallowing threshold parameters together with the chewing frequency as derived from the number of ch- ewing cycles and the time until swallowing are consid- ered appropriate to describe how people manage their chewing process [4,5]. Therefore, swallowing threshold parameters outcomes can be used to indicate to what extent people adapt to loss of teeth or prosthodontic de- vices, e.g. by more chewing cycles until swallowing or by swallowing larger food particles. Bite force, chewing efficiency and their relationship were previously analyzed for subjects with complete (over) denture prostheses and for natural dentitions [1]. 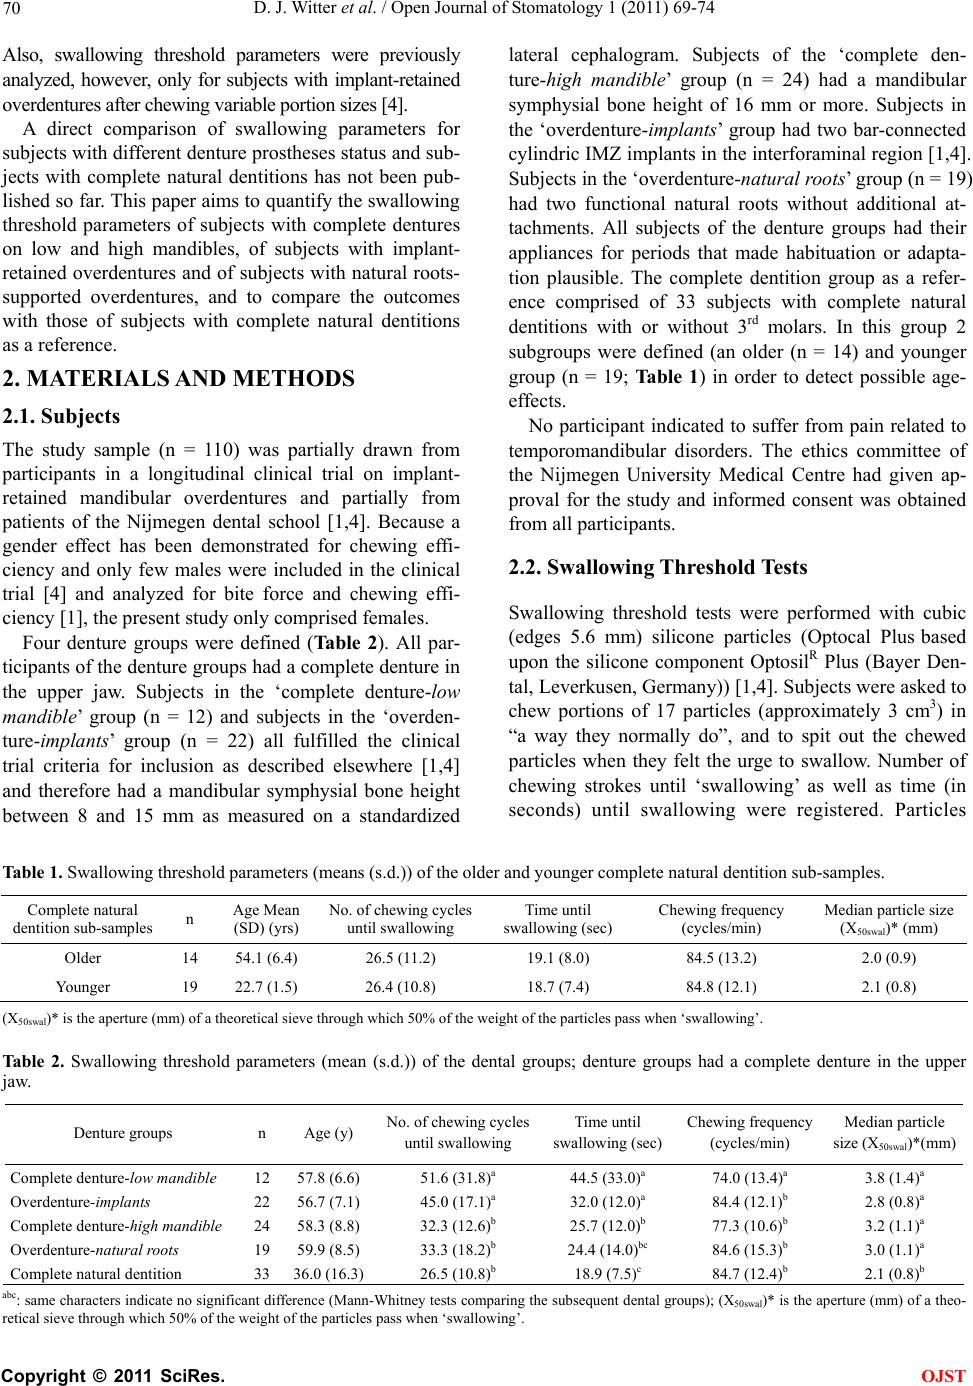 D. J. Witter et al. / Open Journal of Stomatology 1 (2011) 69-74 70 Also, swallowing threshold parameters were previously analyzed, however, only for subjects with implant-retained overdentures after chewing variable portion sizes [4]. A direct comparison of swallowing parameters for subjects with different denture prostheses status and sub- jects with complete natural dentitions has not been pub- lished so far. This paper aims to quantify the swallowing threshold parameters of subjects with complete dentures on low and high mandibles, of subjects with implant- retained overdentures and of subjects with natural roots- supported overdentures, and to compare the outcomes with those of subjects with complete natural dentitions as a reference. 2. MATERIALS AND METHODS 2.1. Subjects The study sample (n = 110) was partially drawn from participants in a longitudinal clinical trial on implant- retained mandibular overdentures and partially from patients of the Nijmegen dental school [1,4]. Because a gender effect has been demonstrated for chewing effi- ciency and only few males were included in the clinical trial [4] and analyzed for bite force and chewing effi- ciency [1], the present study only comprised females. Four denture groups were defined (Ta b l e 2 ). All par- ticipants of the denture groups had a complete denture in the upper jaw. Subjects in the ‘complete denture-low mandible’ group (n = 12) and subjects in the ‘overden- ture-implants’ group (n = 22) all fulfilled the clinical trial criteria for inclusion as described elsewhere [1,4] and therefore had a mandibular symphysial bone height between 8 and 15 mm as measured on a standardized lateral cephalogram. Subjects of the ‘complete den- ture-high mandible’ group (n = 24) had a mandibular symphysial bone height of 16 mm or more. Subjects in the ‘overdenture-implants’ group had two bar-connected cylindric IMZ implants in the interforaminal region [1,4]. Subjects in the ‘overdenture-natural roots’ group (n = 19) had two functional natural roots without additional at- tachments. All subjects of the denture groups had their appliances for periods that made habituation or adapta- tion plausible. The complete dentition group as a refer- ence comprised of 33 subjects with complete natural dentitions with or without 3rd molars. In this group 2 subgroups were defined (an older (n = 14) and younger group (n = 19; Tab le 1) in order to detect possible age- effects. No participant indicated to suffer from pain related to temporomandibular disorders. The ethics committee of the Nijmegen University Medical Centre had given ap- proval for the study and informed consent was obtained from all participants. 2.2. Swallowing Thr eshold Tests Swallowing threshold tests were performed with cubic (edges 5.6 mm) silicone particles (Optocal Plus based upon the silicone component OptosilR Plus (Bayer Den- tal, Leverkusen, Germany)) [1,4]. Subjects were asked to chew portions of 17 particles (approximately 3 cm3) in “a way they normally do”, and to spit out the chewed particles when they felt the urge to swallow. Number of chewing strokes until ‘swallowing’ as well as time (in seconds) until swallowing were registered. Particles Table 1. Swallowing threshold parameters (means (s.d.)) of the older and younger complete natural dentition sub-samples. Complete natural dentition sub-samples n Age Mean (SD) (yrs) No. of chewing cycles until swallowing Time until swallowing (sec) Chewing frequency (cycles/min) Median particle size (X50swal)* (mm) Older 14 54.1 (6.4) 26.5 (11.2) 19.1 (8.0) 84.5 (13.2) 2.0 (0.9) Younger 19 22.7 (1.5) 26.4 (10.8) 18.7 (7.4) 84.8 (12.1) 2.1 (0.8) (X50swal)* is the aperture (mm) of a theoretical sieve through which 50% of the weight of the particles pass when ‘swallowing’. Ta b le 2 . Swallowing threshold parameters (mean (s.d.)) of the dental groups; denture groups had a complete denture in the upper jaw. Denture groups n Age (y) No. of chewing cycles until swallowing Time until swallowing (sec) Chewing frequency (cycles/min) Median particle size (X50swal)*(mm) Complete denture-low mandible Overdenture-implants Complete denture-high mandible Overdenture-natural ro ots Complete natural dentition 12 22 24 19 33 57.8 (6.6) 56.7 (7.1) 58.3 (8.8) 59.9 (8.5) 36.0 (16.3) 51.6 (31.8)a 45.0 (17.1)a 32.3 (12.6)b 33.3 (18.2)b 26.5 (10.8)b 44.5 (33.0)a 32.0 (12.0)a 25.7 (12.0)b 24.4 (14.0)bc 18.9 (7.5)c 74.0 (13.4)a 84.4 (12.1)b 77.3 (10.6)b 84.6 (15.3)b 84.7 (12.4)b 3.8 (1.4)a 2.8 (0.8)a 3.2 (1.1)a 3.0 (1.1)a 2.1 (0.8)b abc: same characters indicate no significant difference (Mann-Whitney tests comparing the subsequent dental groups); (X50swal)* is the aperture (mm) of a theo- retical sieve through which 50% of the weight of the particles pass when ‘swallowing’. C opyright © 2011 SciRes. OJST  D. J. Witter et al. / Open Journal of Stomatology 1 (2011) 69-74 71 were air-dried for at least one week and sieved for 20 minutes in a stack up to 12 sieves, with square meshes decreasing from 5.6 mm at the top to 0.5 mm at the bot- tom and a bottom plate (Laboratory Sieving machine VS1000; F. Kurt Retsch, Haan, Germany). Frequent in- termittent eccentric movements of the sieves gave ir- regularly shaped particles (as after chewing) opportuni- ties for favorable positions to fall through the square meshes. After the drying period, the sizes of the chewed particles were assessed by determining the aperture of a theoretical sieve through which 50% of the weight of the particles can pass and this was expressed as the median particle size (X50swal) [4, 5]. Tests were carried out twice. 2.3. Statistical Analyses To determine the added value for repeating the chewing tests, Spearman’s correlation coefficient was used to assess the relation between the two measurements in each subject. All correlations (for the number of chewing cycles, the time until ‘swallowing’, X50swal , and chewing frequency) were 0.85 or higher. This indicates a very high correlation between the first and second test. In the main analysis, the number of chewing cycles, and the time until ‘swallowing’, and X50swal were averaged. The chewing frequency was calculated from these mean val- ues as the number of chewing cycles per minute. The two subgroups ‘complete dentition-older’ and ‘complete dentition-younger’ were compared in order to detect possible age effects (Mann-Whitney tests). For reason of irregular distributions of the outcomes, non- parametric tests were used: Kruskal-Wallis tests to detect group effects comparing all five dental groups. If the groups differed significantly according to the Kruskal- Wallis test, Mann-Whitney tests were used to analyze differences between the five subsequent dental groups with the following sequence: complete denture-lo w mandi- ble, overdenture-implants, complete denture-high man- dible, overdenture-natural roots, and complete natural dentition. Next, the relation between the number of chewing cycles until ‘swallowing’, the time until ‘swal- lowing’, and X50swal was assessed (Spearmans’s Rho). For the analyses, SPSS program, version 16.0 was used. P-values ≤ 0.05 were considered significant. 3. RESULTS Swallowing threshold parameters of the older and younger complete natural dentition sub-samples did not differ significantly (Table 1; all 4 tests: P ≥ 0.392). Therefore, the sub-samples were combined to the com- plete natural dentition group for statistical analyses (n = 33; Table 2). Descriptive statistics and presence of statistical sig- nificant differences between the groups regarding the four outcome variables are given in Table 2. Concerning the number of chewing cycles until ‘swal- lowing’ the Kruskal-Wallis test revealed a significant difference (P < 0.001). Amongst the denture groups a dichotomy can be observed: a high number of chewing cycles for the ‘complete denture-low mandible’ and the ‘overdenture-implants’ groups compared to the other two denture groups (‘high mandible’ and ‘natural-roots’) and the control group. Regarding the time until ‘swallowing’, the Kruskal- Wallis test again revealed a significant difference (P < 0.001). An analogous dichotomy for the denture groups can be distinguished: the ‘complete denture-low mandi- ble’ and ‘overdenture-implants’ groups chewed longer than the other two denture groups. However, all denture groups with the exception of the ‘overdenture-natural roots’ group used significantly longer time until ‘swal- lowing’ than the complete natural dentition group (con- trol). For chewing frequency, the Kruskal-Wallis test again showed a significant difference, but this outcome was less clear (P = 0.046). The frequency was significantly lowest in the ‘complete denture-low mandible’ group, without a significant difference between the other (sub- sequent) groups. For X50swal, the Kruskal-Wallis test showed a clear cut significant difference (P < 0.001). All denture groups had similar X50swal scores in the order of 3 mm while the complete natural dentition group showed a X50swal of approximately 2 mm. Within all dental groups, the number of chewing cy- cles until ‘swallowing’ was highly significant correlated with time until ‘swallowing’ (Spearman’s Rho’s ranged from 0.87 to 0.95; all P-values < 0.001). As a conse- quence the chewing frequency was more or less constant within each group. Moreover, for all five groups the number of chewing cycles until ‘swallowing’ was sig- nificant negatively correlated with X50swal (Spearman’s Rho’s ranged between –0.45 and –0.87; all P-values 0.037 or lower). 4. DISCUSSION 4.1. Study Design The dental groups of this study were convenient samples of subjects participating in other studies of the Nijmegen dental school, and selected on the basis of availability. As only a small number of males was included in the clinical trial on implant-retained overdentures [4], males were eventually not included in this study. It has been demonstrated in that clinical trial that males chewed their food more efficiently than females, as they achieved C opyright © 2011 SciRes. OJST  D. J. Witter et al. / Open Journal of Stomatology 1 (2011) 69-74 72 greater particle size reduction using the same number of chewing cycles [4]. Although gender was found to have a small indirect effect on chewing function because of bite force [6], it is plausible that the relationships found in the present study also apply to males. The criterion of a symphysial bone height of 16 mm as applied in this study originates from the inclusion criteria of the original clinical trial [4]. This cut-off cor- responds with Cawood Class V: “a flat ridge form, in- adequate in height and width” [7], which might com- promise complete denture function and thus gives rele- vance for using implants. In the previous study investigating chewing efficiency and bite force [1], subjects with complete dentitions were slightly younger than those of the denture groups. Therefore, a group of young adults was included in order to detect possible age effects. In the present study age effects were not found (Table 1), which is in accordance with findings of others [6,8]. Therefore, both age groups were combined for further analyses. Analyses revealed a very high correlation between the repeated measurements within each subject. This implies a marginal added value of the second test. Consequently, in similar studies a restriction to one test only can be advised. In cases the Kruskal-Wallis test showed an overall dif- ference between groups, the Mann-Whitney was applied. This test was chosen to minimize the number of post-hoc tests. However, this test only compares subsequent (ad- jacent) groups in a more or less logical sequence, for instance starting from ‘poor’ to ‘good’ outcomes as ex- pected beforehand. For the three primary outcomes this appeared to be an appropriate approach because the out- comes coincided with the sequence of the groups. How- ever, for chewing frequency this was not the case. Here two groups not being subsequent groups, i.e. the ‘com- plete denture-low mandible’ and the ‘complete den- ture-high mandible’ groups were found to deviate from the other groups. Consequently, for chewing frequency the labeling of the groups (Table 2) to indicate differ- ences or similarities amongst non-adjacent groups is too crude. 4.2. Chewing Test Outcomes The relative similarity between the outcomes of the first and the second test indicates that the chewing process until ‘swallowing’ is fairly constant within a subject for a specific type of food. On the other hand, the large dif- ferences in outcomes together with large standard devia- tions (Ta bl e 2 ) indicate wide variations among subjects. This implies that the chewing process is an individually determined and adapted process e.g. to denture function [9,10]. It can be subject of debate whether chewing just a single type of artificial test ‘food’ represents ‘real life’ chewing function. The difference in particle size reduc- tion between ‘good’ and ‘bad’ chewers in such a test depends partly on food consistency, and the firm artifi- cial test ‘food’ as used in the present study might have magnified differences between ‘good’ and ‘bad’ chewers [5,11]. Moreover, it has been shown that larger portions to chew until ‘swallowing’ increase X50swal, and the number of chewing cycles until ‘swallowing’ increases linearly with the volume [4,12], but it is unknown wh- ether this increase is proportionally amongst dental groups. Despite these shortcomings the outcomes of this study are considered to be indicative for clinically rele- vant swallowing parameters when comparing groups with different dental or prosthodontic status. 4.3. Compensation for Impaired Chewing Capacity It has been stated that chewing efficiency of complete denture wearers is substantially inefficient compared to subjects with complete natural dentitions: less than one-sixth [3], or even one-seventh [13]. The present study on the other hand, focusing on chewing until ‘swallowing’ reveals a less dramatic pic- ture. Compensation for the reduced chewing efficiency by more chewing cycles and longer time until ‘swallow- ing’ in the denture groups resulted overall in a 40% to 50% larger X50swal than in the complete dentition group, however subjects with ‘complete denture-low mandible’ had approximately twice larger X50swal (Table 2). When people use more chewing cycles until ‘swal- lowing’ and chew with lower frequency, however swal- low larger particles, this reflects the effectiveness of their chewing process. Compared to the controls, sub- jects in the ‘complete denture-low mandib l e ’ group used a higher number of chewing cycles until ‘swallowing’ (factor 1.9), had lower chewing frequency (factor 1.1), and had larger outcome X50swal (factor 1.8). Although these are dependent variables, these figures can be inter- preted as that the chewing effectiveness is 1.9 (higher number of chewing cycles) × 1.1 (lower chewing fre- quency) × 1.8 (larger X50swal) = 3.8 times lower than that of the controls. Following this interpretation, in the ‘complete denture-high mandible’ group the chewing effectiveness was 1.2 × 1.1 × 1.5 = 2.0 times lower; in the ‘overdenture-implants’ group 1.7 × 1.0 × 1.3 = 2.2 lower, and in the ‘overdenture-natural roots’ group 1.3 × 1.0 × 1.4 = 1.8 times lower than that of subjects with complete natural dentitions. With respect to interventions aiming to achieve a more acceptable chewing process, the application of implants (mostly in low mandibles) or the preservation C opyright © 2011 SciRes. OJST  D. J. Witter et al. / Open Journal of Stomatology 1 (2011) 69-74 73 of natural roots are considered valid interventions. However, improvement of chewing effectiveness is lim- ited to the level of the ‘complete denture-high mandible’ group. This indicates that mandibular implant-retained overdenture treatment is most effective in terms of im- proved masticatory performance in persons with a less than adequate mandibular ridge. This suggestion has been stated also by others [14], irrespective different mesostructure modalities including bar-clip (as in this study), ball or magnet attachments [15]. As stated previously, the relatively large standard de- viations in X50swal denote substantial individual variation within groups. In other words, the differences within groups are large compared to the mean differences amongst groups. Just as an illustration, the subject with the lowest number of chewing cycles before ‘swallow- ing’ was found in the ‘complete denture-low mandible’ group. It should be noted that denture status is just one of the chewing efficiency determinants. Other determi- nants are saliva, muscles (influencing bite force), and cultural habits and personality. In other words, also cul- tural and personality traits determine ‘slow’ and ‘fast’ swallowers [9,10,16-18]. The multifactorial nature of the chewing process undoubtedly explains the large indi- vidual differences in the outcomes of this study on swallowing threshold parameters. This individual varia- tion is considered unproblematic since the assumed link between chewing function and deficient dietary intake is based only on relatively weak correlations and cannot confer a causal relationship [19], as it is not clear to what extent human digestion depends on chewing [20]. 5. CONCLUSIONS 1) Despite efforts to compensate for their reduced chew- ing efficiency by a larger number of chewing cycles until ‘swallowing’, subjects with mandibular (over)dentures and maxillary complete dentures had approximately 40% - 80% larger X50swal than subjects with complete natural dentitions. 2) The outcomes of swallowing threshold parameters of subjects with overdentures retained by implants or natural roots were on average comparable to those of subjects with complete dentures on a ‘high’ mandible. 3) Apart from dental and denture status, large indi- vidual differences in outcomes of swallowing threshold parameters were observed indicating ‘slow’ and ‘fast’ swallowers. REFERENCES [1] Fontijn-Tekamp, F.A., Slagter, A.P., Van der Bilt, A., et a l. (2000) Biting and chewing in overdentures, full dentures, and natural dentitions. Journal of Dental Research, 79, 1519-1524. doi:10.1177/00220345000790071501 [2] Pereira, L.J., Gaviao, M.B.D. and Van der Bilt, A. (2006) Influence of oral characteristics and food products on masticatory function. Acta Odontologica Scandinavica, 64, 193-201. doi:10.1080/00016350600703459 [3] Kapur, K.K. and Soman, S.D. (1994) Masticatory per- formance and efficiency in denture wearers. Journal of Prosthetic Dentistry, 92, 107-111. doi:10.1016/j.prosdent.2004.03.026 [4] Fontijn-Tekamp, F.A., Slagter, A.P., Van der Bilt, A., et a l. (2004) Swallowing thresholds of mandibular implant- retained overdentures with variable portion sizes. Clini- cal Oral Implants Research, 15, 375-380. doi:10.1111/j.1600-0501.2004.01006.x [5] Slagter, A.P., Bosman, F. and Van der Bilt, A. (1993) Comminution of two artificial test foods by dentate and edentulous subjects. Journal of Oral Rehabilitation, 20, 159-176. doi:10.1111/j.1365-2842.1993.tb01599.x [6] Hatch, J.P., Shinkai, R.S.A., Sakai, S., et al. (2000) De- terminants of masticatory performance in dentate adults. Archives of Oral Biology, 46, 641-648. doi:10.1016/S0003-9969(01)00023-1 [7] Cawood, J.I. and Howell, R.A. (1988) A classification of the edentulous jaws. International Journal of Oral & Maxillofacial Surgery, 17, 232-236. doi:10.1016/S0901-5027(88)80047-X [8] Palmer, C.A. (2005) Age-related changes in oral health status. Effects on diet and nutrition. In: Touger-Decker, R., Sirois, D.A. and Mobley, C.C., Eds., Nutrition and Oral Medicine, Humana Press Inc., Totowa, New Jersey, 31-43. doi:10.1385/1-59259-831-5:031 [9] Van der Bilt, A., Engelen, L., Pereira, L.J., et al. (2006) Oral physiology and mastication. Physiology & Behavior, 89, 22-27. doi:10.1016/j.physbeh.2006.01.025 [10] Ueda, T., Sakurai, K. and Sugiyama, T. (2006) Individual difference in the number of chewing strokes and its de- terminant factors. Journal of Oral Rehabilitation, 33, 85- 93. doi:10.1111/j.1365-2842.2006.01537.x [11] Engelen, L., Fontijn-Tekamp, A. and Van der Bilt, A. (2005) The influence of product and oral characteristics on swallowing. Archives of Oral Biololgy, 50, 739-747. doi:10.1016/j.archoralbio.2005.01.004 [12] Fontijn-Tekamp, F.A., Van der Bilt, A., Abbink, J.H., et al. (2004) Swallowing threshold and masticatory per- formance in dentate adults. Physiology & Behavior, 83, 431-436. doi:10.1016/j.physbeh.2004.08.026 [13] Slagter, A.P., Olthoff, L.W., Steen, W.H.A., et al. (1992) Comminution of food by complete-denture wearers. Journal of Dental Research, 71, 380-386. doi:10.1177/00220345920710020601 [14] Kimoto, K. and Garrett, N.R. (2003) Effect of mandibu- lar ridge height on masticatory performance with man- dibular conventional and implant-assisted overdentures. International Journal of Oral & Maxillofacial Implants, 18, 523-530. [15] Van Kampen, F.M.C., Van der Bilt, A., Cune, M.S., et al. (2004) Masticatory function with implant-supported over- dentures. Journal of Dental Research, 83, 708-711. doi:10.1177/154405910408300910 [16] Sreebny, L.M. (2000) Saliva in health and disease: An appraisal and update. International Dental Journal, 50, 140-161. doi:10.1111/j.1875-595X.2000.tb00554.x C opyright © 2011 SciRes. OJST  D. J. Witter et al. / Open Journal of Stomatology 1 (2011) 69-74 Copyright © 2011 SciRes. 74 OJST [17] Shinkawa, T., Hayashida, N., Mori, K., et al. (2009) Poor chewing ability is associated with lower muccosal mois- ture in elderly individuals. The Tohoku Journal of Ex- perimental Medicine, 219, 26-267. doi:10.1620/tjem.219.263 [18] Van der Bilt, A. (2011) Assessment of mastication with implications for oral rehabilitation: A review. Journal of Oral Rehabilitation, 38, 754-780. doi:10.1111/j.1365-2842.2010.02197.x [19] N’Gom, P.I. and Woda, A. (2002) Influence of impaired mastication on nutrition. Journal of Prosthetic Dentistry, 87, 667-673. doi:10.1067/mpr.2002.123229 [20] Wilding, R.J.C. (1993) The association between chewing efficiency and occlusal contact area in man. Archives of Oral Biology, 38, 589-596. doi:10.1016/0003-9969(93)90124-5 |