

Paper Menu >>
Journal Menu >>
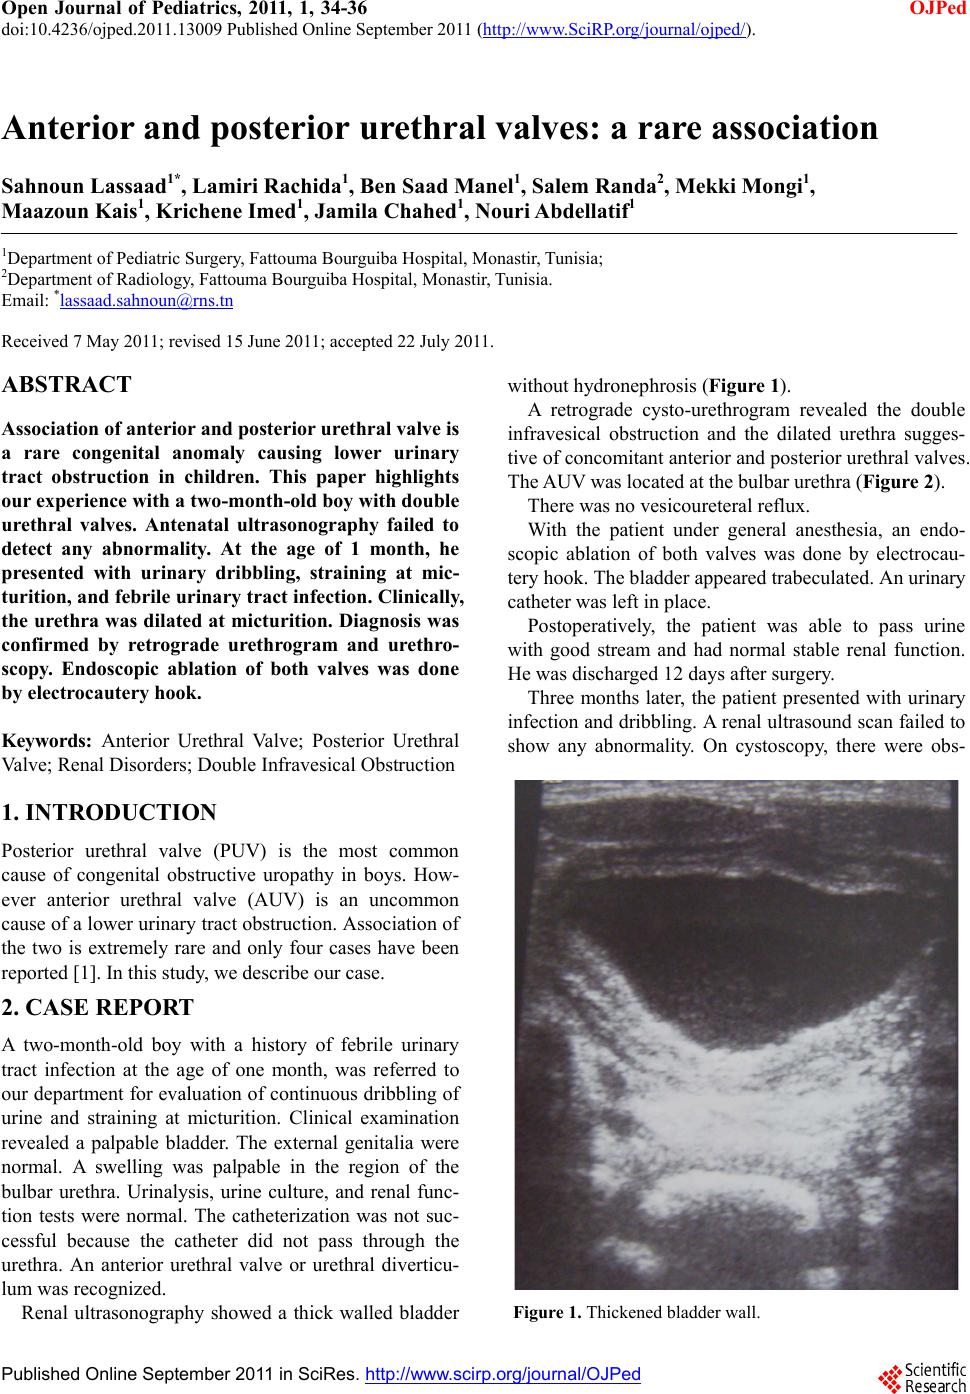 Open Journal of Pediatrics, 2011, 1, 34-36 doi:10.4236/ojped.2011.13009 Published Online September 2011 (http://www.SciRP.org/journal/ojped/ OJPed ). Published Online September 2011 in SciR es. http://www.scirp.org/journal/OJPed Anterior and posterior urethral valves: a rare association Sahnoun Lassaad1*, Lamiri Rachida1, Ben Saad Manel1, Salem Randa2, Mekki Mongi1, Maazoun Kais1, Krichene Imed1, Jamila Chahed1, Nouri Abdellatif1 1Department of Pediatric Surgery, Fattouma Bourguiba Hospital, Monastir, Tunisia; 2Department of Radiology, Fattouma Bourguiba Hospital, Monastir , Tunisia. Email: *[email protected] Received 7 May 2011; revised 15 June 2011; accepted 22 July 2011. ABSTRACT Association of anterior and posterior urethral valve is a rare congenital anomaly causing lower urinary tract obstruction in children. This paper highlights our experience with a two-month-old boy with double urethral valves. Antenatal ultrasonography failed to detect any abnormality. At the age of 1 month, he presented with urinary dribbling, straining at mic- turition, and febrile urinary tract infection. Clinically, the urethra was dilated at micturition. Diagnosis was confirmed by retrograde urethrogram and urethro- scopy. Endoscopic ablation of both valves was done by electrocautery hook. Keywords: Anterior Urethral Valve; Posterior Urethral Va lve; Renal Disorders; Double Infravesical Obstruction 1. INTRODUCTION Posterior urethral valve (PUV) is the most common cause of congenital obstructive uropathy in boys. How- ever anterior urethral valve (AUV) is an uncommon cause of a lower urinary tract obstruction. Association of the two is extremely rare and only four cases have been reported [1]. In this study, we describe our case. 2. CASE REPORT A two-month-old boy with a history of febrile urinary tract infection at the age of one month, was referred to our department for evaluation of continuous dribbling of urine and straining at micturition. Clinical examination revealed a palpable bladder. The external genitalia were normal. A swelling was palpable in the region of the bulbar urethra. Urinalysis, urine culture, and renal func- tion tests were normal. The catheterization was not suc- cessful because the catheter did not pass through the urethra. An anterior urethral valve or urethral diverticu- lum was recognized. Renal ultrasonography showed a thick walled bladder without hydronephrosis (Figure 1). A retrograde cysto-urethrogram revealed the double infravesical obstruction and the dilated urethra sugges- tive of concomitant anterior and posterior urethral valves. The AUV was located at the bulbar urethra (Figure 2). There was no vesicoureteral reflux. With the patient under general anesthesia, an endo- scopic ablation of both valves was done by electrocau- tery hook. The bladder appeared trabeculated. An urinary catheter was left in place. Postoperatively, the patient was able to pass urine with good stream and had normal stable renal function. He was discharged 12 days after surgery. Three months later, the patient presented with urinary infection and dribbling. A renal ultrasou nd scan failed to show any abnormality. On cystoscopy, there were obs- Figure 1. Thic kened bl adder wal l. 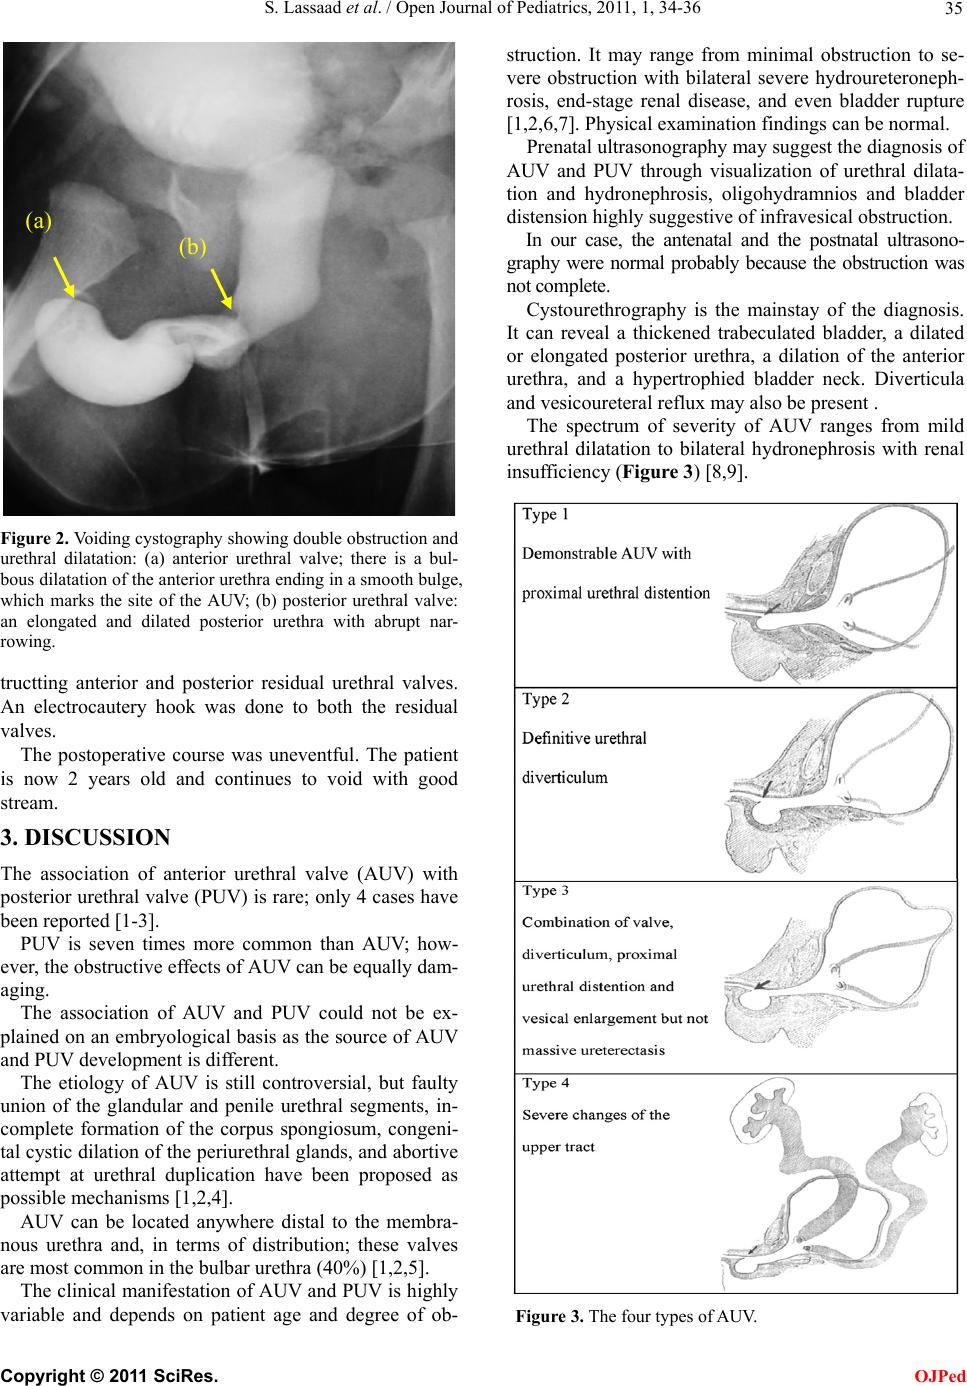 S. Lassaad et al. / Open Journal of Pediatrics, 2011, 1, 34-36 35 Figure 2. Voiding cystography showing double obstruction and urethral dilatation: (a) anterior urethral valve; there is a bul- bous dilatation of the anterior urethra ending in a smooth bulge, which marks the site of the AUV; (b) posterior urethral valve: an elongated and dilated posterior urethra with abrupt nar- rowing. tructting anterior and posterior residual urethral valves. An electrocautery hook was done to both the residual valves. The postoperative course was uneventful. The patient is now 2 years old and continues to void with good stream. 3. DISCUSSION The association of anterior urethral valve (AUV) with posterior urethral valve (PUV) is rare; only 4 cases have been reported [1-3]. PUV is seven times more common than AUV; how- ever, the obstructive effects of AUV can be equally dam- aging. The association of AUV and PUV could not be ex- plained on an embryological basis as the source of AUV and PUV development is different. The etiology of AUV is still controversial, but faulty union of the glandular and penile urethral segments, in- complete formation of the corpus spongiosum, congeni- tal cystic dilation of the periurethral glands, and abortive attempt at urethral duplication have been proposed as possible mechanisms [1,2,4]. AUV can be located anywhere distal to the membra- nous urethra and, in terms of distribution; these valves are most common in the bulbar urethra (40%) [1,2,5]. The clinical manifestation of AUV and PUV is highly variable and depends on patient age and degree of ob- struction. It may range from minimal obstruction to se- vere obstruction with bilateral severe hydroureteroneph- rosis, end-stage renal disease, and even bladder rupture [1,2,6,7]. Physical examination fin di n gs ca n be no rmal. Prenatal ultraso nography may sug gest the diagnosis of AUV and PUV through visualization of urethral dilata- tion and hydronephrosis, oligohydramnios and bladder distension highly suggestive of infravesical obstruction. (a) In our case, the antenatal and the postnatal ultrasono- graphy were normal probably because the obstruction was not complete. (b) Cystourethrography is the mainstay of the diagnosis. It can reveal a thickened trabeculated bladder, a dilated or elongated posterior urethra, a dilation of the anterior urethra, and a hypertrophied bladder neck. Diverticula and vesicoureteral reflux may also be present . The spectrum of severity of AUV ranges from mild urethral dilatation to bilateral hydronephrosis with renal insufficiency (Figure 3) [8,9]. Figure 3. The four types of AUV. C opyright © 2011 SciRes. OJPed  S. Lassaad et al. / Open Journal of Pediatrics, 2011, 1, 34-36 Copyright © 2011 SciRes. 36 The simplest form is the type 1 like our case [5]. There are various treatment methods such as open ure- throtomy and excision of the valve, segmental urethrec- tomy of the valve-bearing area along with a primary end- to-end anastomosis, cold disruption and transurethral resection of the valve. But endoscopic valve ablation by electrocautery has been the procedure of choice. In our case the endoscopic resection gave good results after 6 months of follow up. OJPed 4. CONCLUSIONS Association of AUV and PUV is a rare entity generally described in case reports. It can cause early proximal urinary tract damage and renal failure if not intervened in time. Transurethral resection is the treatment of choice. REFERENCES [1] Bhagat, S.K., Gopalakrishnan, G., Kekre, N.S. and Ku- mar, S. (2008) Anterior and posterior urethral valves with subcoronal hypospadias: A rare association. Journal of Pediatric Surgery, 43, E23-E25. [2] Kajbafzadeh, A.M., Jangouk, P. and Ahmadi Yazdi, C. (2005) Anterior urethral valve associated with posterior urethral valves. Journal of Pediatric Urology, 1, 433-435. doi:10.1016/j.jpurol.2005.05.007 [3] Graham, S.D. Jr., Krueger, R.P. and Glenn, J.F. (1982) Anterior urethral diverticulum associated with posterior urethral valves. Journal of Urology, 128, 376e8. [4] McLellan, D.L., Gaston, M.V., Diamond, D.A., Lebovitz, R.L., Mandel, J. , Atal a, A., et al. (2004) Anterior urethral valves and diverticula in children: A result of ruptured Cowper’s duct cyst. British Journal of Urology Interna- tional, 94, 375e8. [5] Kibar, Y., Coban, H., Irkilata, H.C., Erdemir, F., Seckin, B. and Dayanc, M. (2007) Anterior urethral valves: An uncommon cause of obstructive uropathy in children. Journal of Pediatric Urology, 3, 350-353. [6] Firlit, C.F. and King, L.R. (1972). Anterior urethral val- ves in children. Journal of Urology, 108, 972e6. [7] Aygün, C., Güven, O., et al. (2001) Anterior valve as a cause of end stage renal disease. International Journal of Urology, 8, 141-143. doi:10.1046/j.1442-2042.2001.00270.x [8] Narashiman, K.L., Choudhary, S.K. and Kaur, B. (2005) Anterior urethral valves. Indian Pediatrics, 42, 708-710. [9] Bhagat, S.K., Gopalakrishnan, G., Kekre, N.S. and Ku- mar, S. (2008) Anterior and posterior urethral valves with subcoronal hypospadias: A rare association. Journal of Pediatric Surgery, 43, e23-e25. doi:10.1016/j.jpedsurg.2008.04.026 |