

Paper Menu >>
Journal Menu >>
 Open Journal of Pediatrics, 2011, 1, 30-33 doi:10.4236/ojped.2011.13008 Published Online September 2011 (http://www.SciRP.org/journal/ojped/ OJPed ). Published Online September 2011 in SciR es. http://www.scirp.org/journal/OJPed Chronological changes in Epstein-Barr virus genome and subsets of peripheral mononuclear cells in a case of HLH Yukayo Ukeba-Terashita1, Yoshinori Saita1, Yoshinori Ito2, Hirokazu Kanegane3, Hiroshi Kimura4, Ichiro Kobayashi1,5* 1Department of Pediatrics, Kitami Red Cross Hospital, Kitami, Japan; 2Department of Pediatrics, Nagoya University Graduate School of Medicine, Nagoya, Japan; 3Department of Pediatrics, Graduate School of Medicine, University of T o yama, To yama, Japan; 4Department of Virology, Nagoya University Graduate School of Medicine, Nagoya, Japan; 5Department of Pediatrics, Hokkaido University Graduate School of Medicine, Sapporo, Japan. Email: *[email protected] Received 30 April 2011; revised 1 June 2011; accepted 15 July 2011. ABSTRACT Hemophagocytic lymphohistiocytosis (HLH) is a rare disorder characterized by high grade fever, heap- tosplenomegaly, lymphadenopathy and cytope- nia in association with hypercytokinemia and mac- rophage activation. Epstein-Barr virus (EBV) is a common cause of HLH particularly in Asian countries. Al- though EBV usually infects B cells and causes infec- tious mononucleosis, it is detected predominantly in CD8+ T cells in EBV-associated HLH. In the present study we found the EBV genome in various lineages of the lymphoid cells including T, B, and natural kil- ler cells in a 14-months-old boy with mild EBV-asso- ciated HLH. Furthermore, chronological changes in the copy number of EBV-DNA in each lineage are reported. Profound decrease in the number of pe- ripheral natural killer cells at the early stage could be involved in the development of HLH. Keywords: Epstein-Barr Virus; Hemophagocytic Lympho- histio Cytosis; Natural Killer Cell 1. INTRODUCTION Hemophagocytic lymphohistiocytosis (HLH) is a rare disorder characterized by high grade fever, hepatosple- nomegaly, lymphadenopathy and cytopenia in associa- tion with hypercytokinemia and macrophage activation [1]. HLH is classified into two clinical entities; primary HLH which develops in inherited diseases such as fa- milial hemophagocytic lymphohistiocytosis (FHL) or pr- imary immunodeficiency, and secondary HLH which develops associated with other acquired disorders such as infection, collagen vascular diseases and malignancy [1]. Sixty percent of the secondary HLH in children is associated with Epstein-Barr virus (EBV) in Japan [2]. Although most cases of EBV-HLH have been reported from Asian countries, reports from other regions have been increasing [3,4]. EBV is a ubiquitous human h erpes virus which usually infects B cells and causes self-lim- iting infectious mononucleosis (IM). On the other hand, persistent or recurrent IM-like disease associated with abnormally high levels of both anti-EBV antibodies and EBV genome is known as chronic active EBV infection (CAEBV) [5]. EBV-associated HLH (EBV-HLH) occurs in association with either CAEBV or a primary infection of the virus [1-5]. Recent reports have demonstrated that EBV infects NK or CD4+ T cells in CAEBV, whereas it dominantly infects CD8+ T cells in EBV-HLH [5,6]. We report here a case of HLH associated with a primary infection of EBV and the chronological changes in EBV-DNA of each lymphoid cell subset. 2. CASE REPORT A previously healthy 14-month-old boy was admitted to our hospital because of fever up to 41˚C persisting for four days. He was born to non-consanguineous healthy parents and had no history suggesting immunodeficiency or hypersensitivity to mosquito bite. On the third hospi- tal day, cervical lymphadenopathy and hepatospleno- megaly were noted. Laboratory examination showed: white blood cell count 7.89 × 10⁹/l (neutrophils 17%, lymphocytes 55%), hemoglobin 98 g/l, platelet count 45 × 109/l, aspartate transaminase 543 IU/l, alanine transami- nase 204 IU/l, total cho lesterol 0.81 g/l, triglyceride 2.24 g/l, C-reactive protein 115.3 mg/l, ferritin 2090 g/ l. Coa gu - lation study showed: prothrombin time 17.8 seconds, activated partial thromboplastin time 51.8 seconds, fi- brinogen 2.66 g/l (reference range 2.00 g/l - 4.00 g/l) and fibrin degradation products 93.9 g/ml (< 10 g/ml), sug- 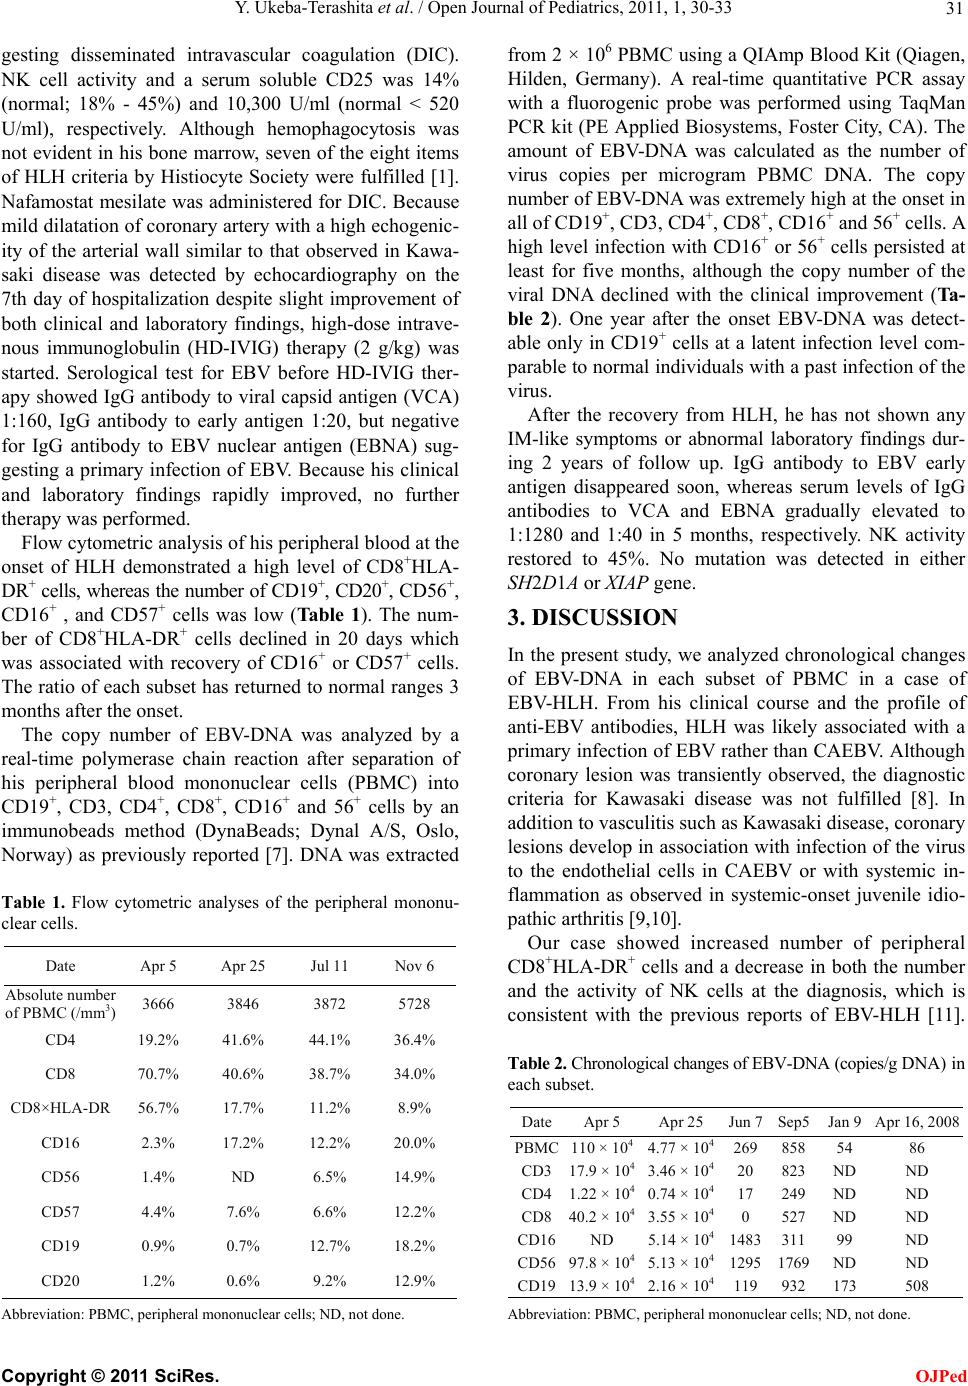 Y. Ukeba-Terashita et al. / Open Journal of Pediatrics, 2011, 1, 30-33 31 gesting disseminated intravascular coagulation (DIC). NK cell activity and a serum soluble CD25 was 14% (normal; 18% - 45%) and 10,300 U/ml (normal < 520 U/ml), respectively. Although hemophagocytosis was not evident in his bone marrow, seven of the eight items of HLH criteria by Histiocyte Society were fulfilled [1]. Nafamostat mesilate was administered for DIC. Because mild dilatation of coronary artery with a high echog enic- ity of the arterial wall similar to that observed in Kawa- saki disease was detected by echocardiography on the 7th day of hospitalization despite slight improvement of both clinical and laboratory findings, high-dose intrave- nous immunoglobulin (HD-IVIG) therapy (2 g/kg) was started. Serological test for EBV before HD-IVIG ther- apy showed IgG antibody to viral capsid antigen (VCA) 1:160, IgG antibody to early antigen 1:20, but negative for IgG antibody to EBV nuclear antigen (EBNA) sug- gesting a primary infection of EBV. Because his clinical and laboratory findings rapidly improved, no further therapy was performed. Flow cytometric analysis of his peripheral blood at the onset of HLH demonstrated a high level of CD8+HLA- DR+ cells, wher eas the number of CD19+, CD20+, CD5 6+, CD16+ , and CD57+ cells was low (Ta b l e 1 ). The num- ber of CD8+HLA-DR+ cells declined in 20 days which was associated with recovery of CD16+ or CD57+ cells. The ratio of each subset has returned to normal ranges 3 months after the onset. The copy number of EBV-DNA was analyzed by a real-time polymerase chain reaction after separation of his peripheral blood mononuclear cells (PBMC) into CD19+, CD3, CD4+, CD8+, CD16+ and 56+ cells by an immunobeads method (DynaBeads; Dynal A/S, Oslo, Norway) as previously reported [7]. DNA was extracted Table 1. Flow cytometric analyses of the peripheral mononu- clear cells . Date Apr 5 Apr 25 Jul 11 Nov 6 Absolute number of PBMC (/mm3) 3666 3846 3872 5728 CD4 19.2% 41.6% 44.1% 36.4% CD8 70.7% 40.6% 38.7% 34.0% CD8×HLA-DR 56.7% 17.7% 11.2% 8.9% CD16 2.3% 17.2% 12.2% 20.0% CD56 1.4% ND 6.5% 14.9% CD57 4.4% 7.6% 6.6% 12.2% CD19 0.9% 0.7% 12.7% 18.2% CD20 1.2% 0.6% 9.2% 12.9% Abbreviation: PBMC, peripheral mononuclear cells; ND, not done. from 2 × 10⁶ PBMC using a QIAmp Blood Kit (Qiagen, Hilden, Germany). A real-time quantitative PCR assay with a fluorogenic probe was performed using TaqMan PCR kit (PE Applied Biosystems, Foster City, CA). The amount of EBV-DNA was calculated as the number of virus copies per microgram PBMC DNA. The copy number of EBV-DNA was extremely high at the onset in all of CD19+, CD3, CD4+, CD8+, CD16+ and 56+ cells. A high level infection with CD16+ or 56+ cells persisted at least for five months, although the copy number of the viral DNA declined with the clinical improvement (Ta- ble 2). One year after the onset EBV-DNA was detect- able only in CD19+ cells at a latent infection level com- parable to normal individuals with a past infection of the virus. After the recovery from HLH, he has not shown any IM-like symptoms or abnormal laboratory findings dur- ing 2 years of follow up. IgG antibody to EBV early antigen disappeared soon, whereas serum levels of IgG antibodies to VCA and EBNA gradually elevated to 1:1280 and 1:40 in 5 months, respectively. NK activity restored to 45%. No mutation was detected in either SH2D1A or XIAP gene. 3. DISCUSSION In the present study, we analyzed chronological changes of EBV-DNA in each subset of PBMC in a case of EBV-HLH. From his clinical course and the profile of anti-EBV antibodies, HLH was likely associated with a primary infection of EBV rather than CAEBV. Although coronary lesion was transiently observed, the diagnostic criteria for Kawasaki disease was not fulfilled [8]. In addition to vasculitis such as Kawasaki disease, coronary lesions develop in association with infection of the virus to the endothelial cells in CAEBV or with systemic in- flammation as observed in systemic-onset juvenile idio- pathic arthritis [9,10]. Our case showed increased number of peripheral CD8+HLA-DR+ cells and a decrease in both the number and the activity of NK cells at the diagnosis, which is consistent with the previous reports of EBV-HLH [11]. Table 2. Chronological changes of EBV-DNA (copies/g DNA) in each subset. DateApr 5 Apr 25 Jun 7 Sep5 Jan 9 Apr 16, 2008 PBMC110 × 1044.77 × 104269 858 54 86 CD317.9 × 1043.46 × 10420 823 ND ND CD41.22 × 1040.74 × 10417 249 ND ND CD840.2 × 1043.55 × 1040 527 ND ND CD16ND 5.14 × 1041483 311 99 ND CD5697.8 × 1045.13 × 1041295 1769 ND ND CD1913.9 × 1042.16 × 104119 932 173 508 Abbreviation: PBMC, peripheral mononuclear cell s ; ND, not done. C opyright © 2011 SciRes. OJPed  Y. Ukeba-Terashita et al. / Open Journal of Pediatrics, 2011, 1, 30-33 32 The dominant population of EBV-infected cells is re- ported to be CD8+ T cells in EBV-HLH, whereas the ma jor target s of EBV in CAEBV are CD4+ T cells or NK cells [5-7]. EBV-infected CD8+Tcells are activated and produce cytokines such as IFN-γ, TNF-α and inter- leukin-6, which activate macrophages and endothelial cells resulting in hemophagocytosis, DIC, and multi- organ failure [1,5,12]. NK cells, as well as EBV-specific cytotoxic T cells (CTL), play a critical role in the elimi- nation of EBV-infected cells [1]. This is supported by the fact that the functional defects in cytotoxic activity of CTL and NK cells such as X-linked lymphoproliferative syndrome and FHL predispose for EBV-HLH [1]. In acute IM the number of NK cells, although it usually increases, is inversely correlated with the severity of the disease [13]. Thus, the numerical defect of NK cells as observed in our case could cause the development of EBV-HLH or severe IM. Our case showed subsequent recovery of both NK activity and the number of CD16+ , 56+ or 57+cells as well as decline in CD8+HLA-DR+ cells, which was associated with clinical improvement. Furthermore, no mutation was detected in causative genes of XLP such as SH2DA or XIAP gene. Thus, al- though mutations of other FHL-related genes have not been tested, the numerical and functional abnormality was unlikely to be intrinsic to his NK cells. Of note was the finding that high lev els of EBV-DNA was detected in CD16+ and 56+ cells, in addition to T and B cells, despite the decreased number of the subsets in our case. Al- though other methods such as in situ hybridization and immunohistochemistry were not performed, a high level of infection in CD 16+ and 56+ cells was confirmed by serial examination for several months. The copy number of EBV-DNA in PBMC of our case was comparable to that in previously reported cases of EBV-HLH, CAEBV and post-transplantational lymphoproliferative disorder [14]. Although EBV-HLH has a tendency to have larger viral burdens than acute phase of IM, it is difficult to differentiate between these two diseases simply by viral load in whole PBMC [15]. The copy number of EBV- DNA gradually declined in all of the subsets and was finally detectable in B cells only at a latency level one year after the onset of the disease. These findings are in contrast to NK cell-type CAEBV or NK cell lymphoma which shows a clonal expansion of EBV-infected NK cells [5]. It is known that EBV is able to infect NK cells at an early stage of IM, although the precise mechanisms of infection remain unclear [16]. As well, EBV genome is also detected in bo th NK and B cells under some con- ditions such as EBV-HLH but usually at a lower level than CD8+ T cells [6]. Isobe et al have reported that in vitro infection of EBV induces apoptosis of NK cells [17]. Thus, it is possible that the infection by EBV in- duced apoptosis of NK cells in vivo and allowed un- regulated activation of EBV-infected CD8+T cells. De- creased number of peripheral B cells in association with HLH as observed in our case has also been reported [18]. Imashuku et al have demonstrated depletion of B cells in the spleen of the patients with HLH and suggested in- volvement of cytokines produced by activated T or NK cells and/or Fas-FasL-mediated apoptosis [18]. Although our case showed both clinical and labora- tory improvement before the commencement of HD- IVIG therapy suggesting self-limiting nature, it is possi- ble that the therapy accelerated the improvement by its anti-inflammatory mechanism [19]. Further studies are required to clarify the mechanisms of the decrease in the number of peripheral NK cells in EBV-HLH without un- derlying primary immunodeficiencies or FHL. In conclusion, EBV infected various subsets of PBMC including NK cells in a case of HLH associated with a primary infection of EBV. EBV genome gradually de- clined in association with his clinical improvement and was finally detectable in only B cells at a latency level. Transient decrease in NK cells could be involved in the development of EBV-HLH in our case. REFERENCES [1] Henter, J.-I., Horne, A.C., Aricó, M., et al. (2007) HLH- 2004: Diagnostic and therapeutic guidelines for hemo- phagocytic lymphohistiocytosis. Pediatric Blood & Can- cer, 48, 124-131. doi:10.1002/pbc.21039 [2] Ishii, E., Ohga, S., Imashuku, S., et al. (2007) Nation- wide survey of hemophagocytic lymphohistiocytosis in Japan. International Journal of Hematology, 86, 58-65. doi:10.1532/IJH97.07012 [3] Beutel, K., Gross-Wieltsch, U., Wiesel, T., Zur Stadt, U., Janka, G. and Wagner, H.-J. (2009) Infection of T lym- phocytes in Epstein-Barr virus-associated hemophago- cytic lymphohistiocytosis in children of non-Asian origin. Pediatric Blood & Cancer, 53, 184-190. [4] Sonke, G.S., Ludwig, I., Van Oosten, H., et al. (2008) Poor utcomes of chronic active Epstein-Barr virus infec- tion and hemophagocytic lymphohistiocytosis in non-Ja- panese adult patients. Clinical Infectious Diseases, 47, 105-108. doi:10.1086/588790 [5] Kimura, H. (2006) Pathogenesis of chronic active Ep- stein-Barr virus infection: Is this an infectious disease, lymphoproliferative disorder, or immunodeficiency? Re- views in Medical Virology, 16, 251-261. doi:10.1002/rmv.505 [6] Kasahara, Y., Yachie, A., Takei, K., et al. (2001) Differ- ential cellular target of Epstein-Barr virus (EBV) infec- tion between acute EBV-associated hemophagocytic lym- phohistiocytosis and chronic active EBV infection. Blood, 98, 1882-1888. doi:10.1182/blood.V98.6.1882 [7] Kimura, H., Hoshino, Y., Kanegane, H., et al. (2001) Cli- nical and virological characteristics of chronic active Ep- stein-Barr virus infection. Blood, 98, 280-286. doi:10.1182/blood.V98.2.280 C opyright © 2011 SciRes. OJPed  Y. Ukeba-Terashita et al. / Open Journal of Pediatrics, 2011, 1, 30-33 Copyright © 2011 SciRes. 33 OJPed [8] Ayusawa, M., Sonobe, T., Ue mura, S., et al., (2005) Revi- sion of diagnostic guidelines for Kawasaki di sease (the 5th revised edition). Pediatrics International, 47, 232-234. |d oi:10.1111/j.1442-200x.2005.02033.x [9] Kikuta, H., Sakiyama, Y., Matsumoto. S., et al. (1993) Detection of Epstein-Barr virus DNA in cardiac and aor- tic tissues from chronic, active Epstein-Barr virus infec- tion associated with Kawasaki disease-like coronary ar- tery aneurysms. Journal of Pediatrics, 123, 90-92. doi:10.1016/S0022-3476(05)81546-X [10] Binstadt, B.A., Levine, J.C., Nigrovic, P.A., et al. (2005) Coronary artery dilation among patients presenting with systemic-onset juvenile idiopathic arthritis. Pediatrics, 116, e89-e93. doi:10.1542/peds.2004-2190 [11] Kogawa, K., Lee, S.M., Vilanueva, J., et al. (2002) Per- forin expression in cytotoxic lymphocytes from patients with hemophagocytic lymphohistiocytosis and their fam- ily member s. Blood, 99, 61-66. doi:10.1182/blood.V99.1.61 [12] Chuang, H.-C., Hsie, W.-C., Wang, H.-C., et al. (2005) Epstein-Barr virus LMP1 inhibits the expression of SAP gene and upregulates Th1 cytokines in the pathogenesis of hemophagocytic syndrome. Blood, 106, 3090-3096. doi:10.1182/blood-2005-04-1406 [13] Williams, H., McAulay, K., Macsween, K.F., et al. (2005) The immune response to primary EBV infection: A role for natural killer cells. British Journal of Haematology, 129, 266-274. doi:10.1111/j.1365-2141.2005.05452.x [14] Kimura, H., Morita, M., Yabuta, Y., et al. (1999) Quanti- tative analysis of Epstein-Barr virus load by using real- time PCR assay. Journal of Clinical Microbiology, 37, 132. [15] Kimura, H., Hoshino, Y., Hara, S., et al. (2002) Viral lo ad in Epstein-Barr virus-associated hemophagocytic syn- drome. Microbiology and Immunology, 46, 579-582. [16] Trempat, P., Tabiasco, J., Andre, P., et al. (2002) Evi- dence for early infection of nonneoplastic natural killer cells by Epstein-Barr virus. Journal of Virology, 76, 11139-11142. doi:10.1128/JVI.76.21.11139-11142.2002 [17] Isobe, Y., Sugimoto, K., Yang, L, et al. (2004) Epstein- Barr virus infection of human natural killer cell lines and peripheral blood natural killer cells. Cancer Research, 64, 2167-2174. [18] Imashuku, S., Obayashi, M., Hosoi, G., et al. (2000) Splenectomy in haemophagocytosis: Report of histopa- thological changes with CD19; B-cell depletion and therapeutic results. British Journal of Haematology, 108, 505-510. doi:10.1046/j.1365-2141.2000.01904.x [19] Nimmerjahn, F. and Ravetch, J.V. (2008) Anti-inflam- matory actions of intravenous immunoglobulin. Annual Review of Immunology, 26, 513-533. doi:10.1146/annurev.immunol.26.021607.090232 |