

Paper Menu >>
Journal Menu >>
 Surgical Science, 2011, 2, 257-261 doi:10.4236/ss.2011.25057 Published Online July 2011 (http://www.SciRP.org/journal/ss) Copyright © 2011 SciRes. SS Liver Transplantation in a Monolu ng Patient: A Strategy of Sequential Treatments of Multiple Lung Tuberculosis Cavitations and Hepatocellular Carc inoma on Hepatitis B Related Virus Cirrhosis Dino Donataccio1, Paola Del Bravo2, Albert o Masotto3, Marcello Ceola4, Francesco Calabrò5, Matteo Donataccio1* 1Liver Transplant Unit, Ospedale Civile Maggiore, Verona, Italy 2 Infectious Disease Unit, Ospedale Po liclinico, Verona, Italy 3Gastroenterology Unit, Ospedale Sacro Cuore-Don Calabria, Negrar, It al y 4Anesthesia and Resuscitation Unit, Ospedale Civile Maggiore, Verona, Italy 5Thoracic Surgery Unit, Ospedale Civile Maggiore, Verona, Italy E-mail: [email protected] Received April 18, 2011; revised May 27, 2011; accepted June 8, 2011 Abstract The presence of extrahepatic infection is a contraindication for liver transplantation, even more if supported by an advanced pulmonary tuberculosis with persistent cavitation not curable with medical treatment. We report a case of a young patient with hepatocellular carcinoma on hepatitis B virus related liver cirrhosis and multiple lung tuberculosis cavitations. The patient was referred to our centre for liver transplantation. We adopted a strategy with sequential treatments. First a left extra-pericardial pneumonectomy was performed without opening the infected cavern, followed by a therapy with rifampicin, isoniazid and ethambutol for a period of nine months. After the cure of tuberculosis, the monolung patient eventually was listed for liver transplantation. An accurate planning of a multistep therapeutical strategy, an appropriate anesthetic man- agement and a meticulous surgical technique allowed to successfully transplant a young patient suffering from three life-threatening diseases: cavitary tuberculosis, hepatitis B virus cirrhosis and hepatocellular car- cinoma. Thirty months after liver transplantation the patient is in good health, with normal liver function, forced expiratory volume in one second of 42% (1.53 liters) and without any tuberculosis disease reactiva- tion. Keywords: Mycobacterium Tuberculosis, Infection, Pneumonectomy, Liver Disease, Liver Surgery 1. Introduction Tuberculosis (TB) is a serious infection due to Myco- bacterium Tuberculosis, with an estimated prevalence of 13.7 million cases world-wide [1]. The frequency of the disease varies geographically, with particular regions (Asia and Africa) having a higher prevalence than other areas of the world [2]. Several factors place transplanted patients at a greater risk of developing active TB. A pre- vious TB infection increases the likelihood of TB devel- oping after transplantation [3]. The number of pre-trans- plant patients with a positive tuberculin skin test (TST) underestimates the number of patients infected with TB because end-stage liver disease may result in cutaneous anergy, which decreases the sensitivity of the TST. Pa- tients with compensated cirrhosis should be considered for the treatment of TB. Patients with decompensated cirrhosis should defer therapy to the period after trans- plantation. Patients with active TB should not undergo transplantation; exceptions might be considered for pa- tients with well-controlled infections. In general, active TB is an absolute contraindication for transplantation [4]. The presence of extrahepatic infection is a contraindica- tion for liver transplantation, even more if supported by an advanced pulmonary tuberculosis with persistent cavitation not curable with medical treatment. The aim of 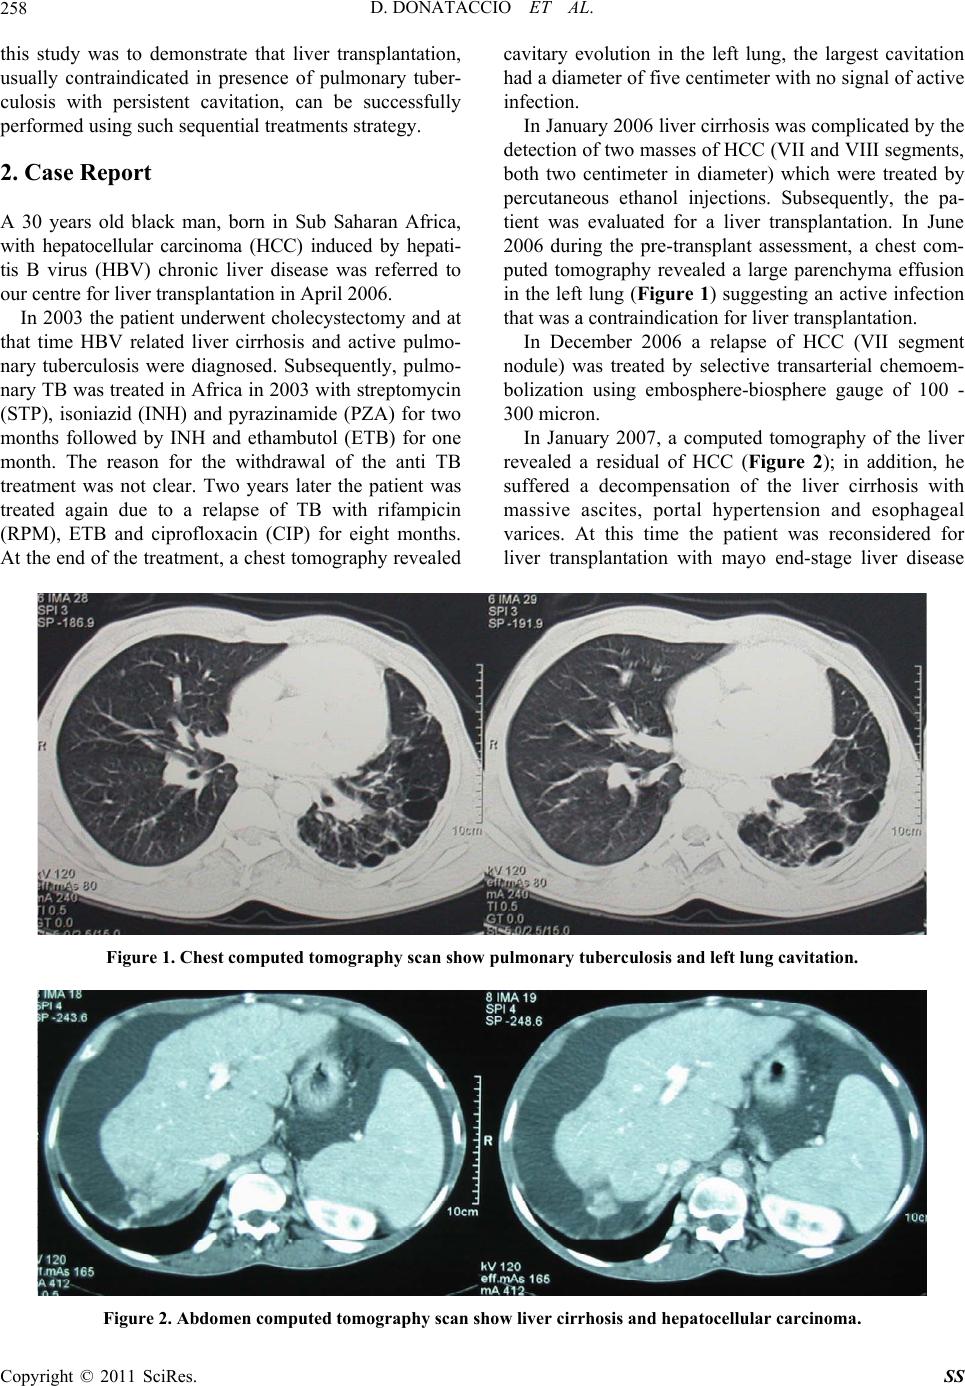 D. DONATACCIO ET AL. 258 this study was to demonstrate that liver transplantation, usually contraindicated in presence of pulmonary tuber- culosis with persistent cavitation, can be successfully performed using such sequential treatments strategy. 2. Case Report A 30 years old black man, born in Sub Saharan Africa, with hepatocellular carcinoma (HCC) induced by hepati- tis B virus (HBV) chronic liver disease was referred to our centre for liver transplantation in April 2006. In 2003 the patient underwent cholecystectomy and at that time HBV related liver cirrhosis and active pulmo- nary tuberculosis were diagnosed. Subsequently, pulmo- nary TB was treated in Africa in 2003 with streptomycin (STP), isoniazid (INH) and pyrazinamide (PZA) for two months followed by INH and ethambutol (ETB) for one month. The reason for the withdrawal of the anti TB treatment was not clear. Two years later the patient was treated again due to a relapse of TB with rifampicin (RPM), ETB and ciprofloxacin (CIP) for eight months. At the end of the treatment, a chest tomography revealed cavitary evolution in the left lung, the largest cavitation had a diameter of five centimeter with no signal of active infection. In January 2006 liv er cirrhosis was co mplicated by the detection of two masses of HCC (VII and VIII seg ments, both two centimeter in diameter) which were treated by percutaneous ethanol injections. Subsequently, the pa- tient was evaluated for a liver transplantation. In June 2006 during the pre-transplant assessment, a chest com- puted tomography revealed a large parenchyma effusion in the left lung (Figure 1) suggesting an active infection that was a contraindication for liver tran splantation. In December 2006 a relapse of HCC (VII segment nodule) was treated by selective transarterial chemoem- bolization using embosphere-biosphere gauge of 100 - 300 micron. In January 2007, a computed tomography of the liver revealed a residual of HCC (Figure 2); in addition, he suffered a decompensation of the liver cirrhosis with massive ascites, portal hypertension and esophageal varices. At this time the patient was reconsidered for liver transplantation with mayo end-stage liver disease Figure 1. Chest computed tomography scan show pulmonary tuberculosis and left lung cavitation. Figure 2. Abdomen co mpute d tomography sc an show liver cirrhosis and hepatocellular carcinoma. Copyright © 2011 SciRes. SS 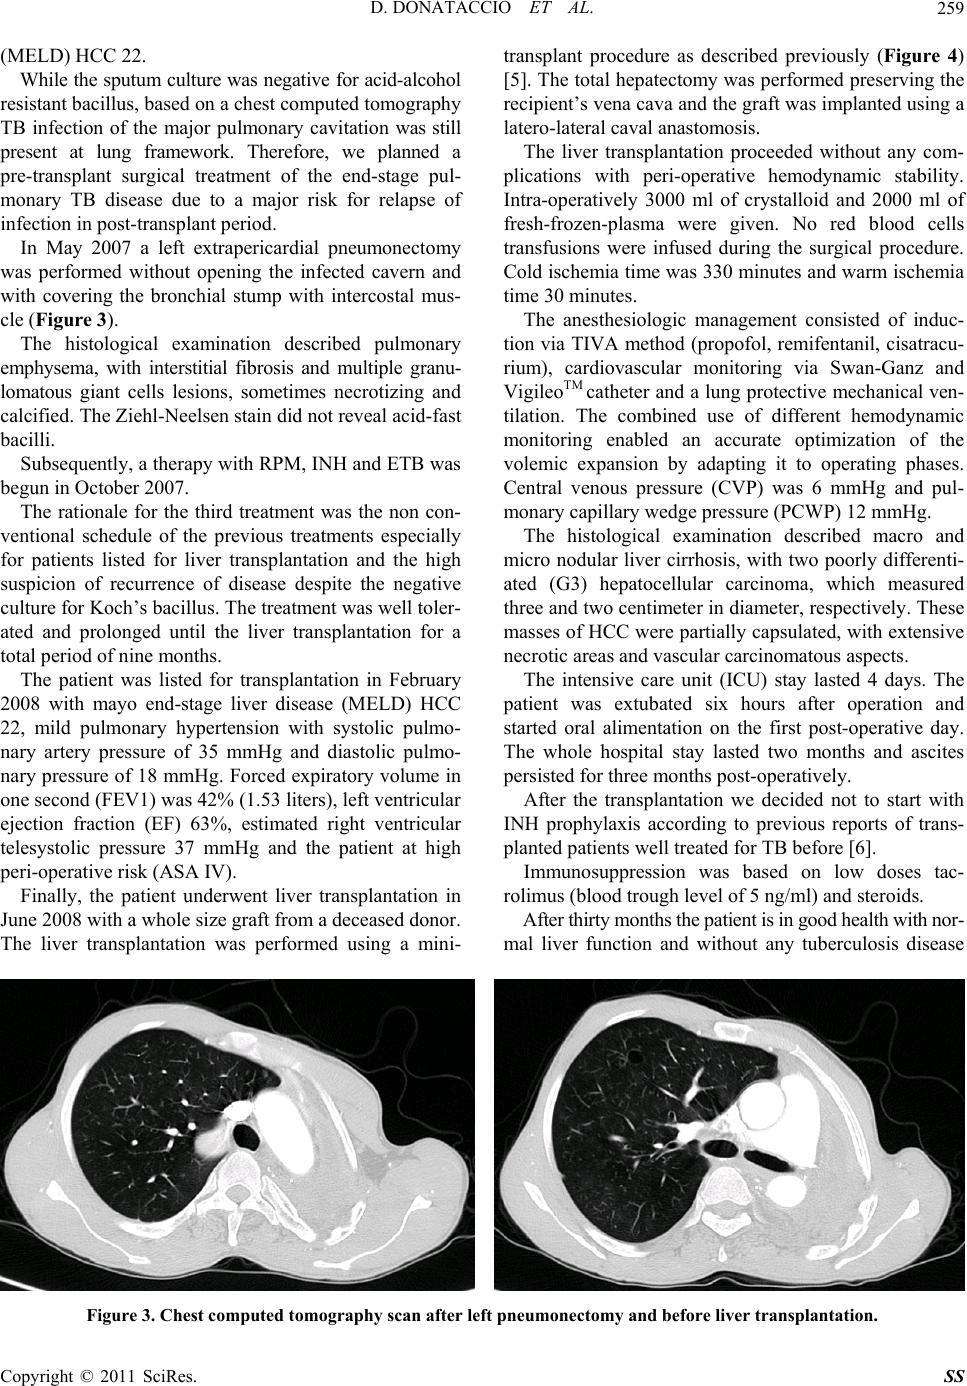 D. DONATACCIO ET AL.259 (MELD) HCC 22 . While the sputum culture was negative for acid-alcohol resistant bacillus, based on a chest computed to mography TB infection of the major pulmonary cavitation was still present at lung framework. Therefore, we planned a pre-transplant surgical treatment of the end-stage pul- monary TB disease due to a major risk for relapse of infection in post-transplant period. In May 2007 a left extrapericardial pneumonectomy was performed without opening the infected cavern and with covering the bronchial stump with intercostal mus- cle (Figure 3). The histological examination described pulmonary emphysema, with interstitial fibrosis and multiple granu- lomatous giant cells lesions, sometimes necrotizing and calcified. The Ziehl-Neelsen stain did not reveal acid-fast bacilli. Subsequently, a therapy with RPM, INH and ETB was begun in October 2007. The rationale for the third treatment was the non con- ventional schedule of the previous treatments especially for patients listed for liver transplantation and the high suspicion of recurrence of disease despite the negative culture for Koch’s bacillus. The treatment was well toler- ated and prolonged until the liver transplantation for a total period of nine months. The patient was listed for transplantation in February 2008 with mayo end-stage liver disease (MELD) HCC 22, mild pulmonary hypertension with systolic pulmo- nary artery pressure of 35 mmHg and diastolic pulmo- nary pressure of 18 mmHg. Forced expiratory volume in one second (FEV1) was 42% (1 .53 liters), left ventricu lar ejection fraction (EF) 63%, estimated right ventricular telesystolic pressure 37 mmHg and the patient at high peri-operative risk (ASA IV). Finally, the patient underwent liver transplantation in June 2008 with a whole size graft from a deceased donor. The liver transplantation was performed using a mini- transplant procedure as described previously (Figure 4) [5]. The total hepatectomy was performed preserving the recipient’s vena cava and the graft was implanted using a latero-lateral caval anastomosis. The liver transplantation proceeded without any com- plications with peri-operative hemodynamic stability. Intra-operatively 3000 ml of crystalloid and 2000 ml of fresh-frozen-plasma were given. No red blood cells transfusions were infused during the surgical procedure. Cold ischemia time was 330 minutes and warm ischemia time 30 minutes. The anesthesiologic management consisted of induc- tion via TIVA method (propofol, remifentanil, cisatracu- rium), cardiovascular monitoring via Swan-Ganz and VigileoTM catheter and a lung protectiv e mechanical ven- tilation. The combined use of different hemodynamic monitoring enabled an accurate optimization of the volemic expansion by adapting it to operating phases. Central venous pressure (CVP) was 6 mmHg and pul- monary capillary wedge pressure (PCWP) 12 mmHg. The histological examination described macro and micro nodular liver cirrhosis, with two poorly differenti- ated (G3) hepatocellular carcinoma, which measured three and two centimeter in diameter, respectively. These masses of HCC were partially capsulated, with extensive necrotic areas and vascular carcinomatous aspects. The intensive care unit (ICU) stay lasted 4 days. The patient was extubated six hours after operation and started oral alimentation on the first post-operative day. The whole hospital stay lasted two months and ascites persisted for three months post-operatively. After the transplantation we decided not to start with INH prophylaxis according to previous reports of trans- planted patients well treated for TB before [6]. Immunosuppression was based on low doses tac- rolimus (blood trough level of 5 ng/ml) and steroids. After thirty months the patient is in good health with nor- mal liver function and without any tuberculosis disease Figure 3. Chest computed tomography scan after left pneumonectomy and be fore liver transplantation. Copyright © 2011 SciRes. SS 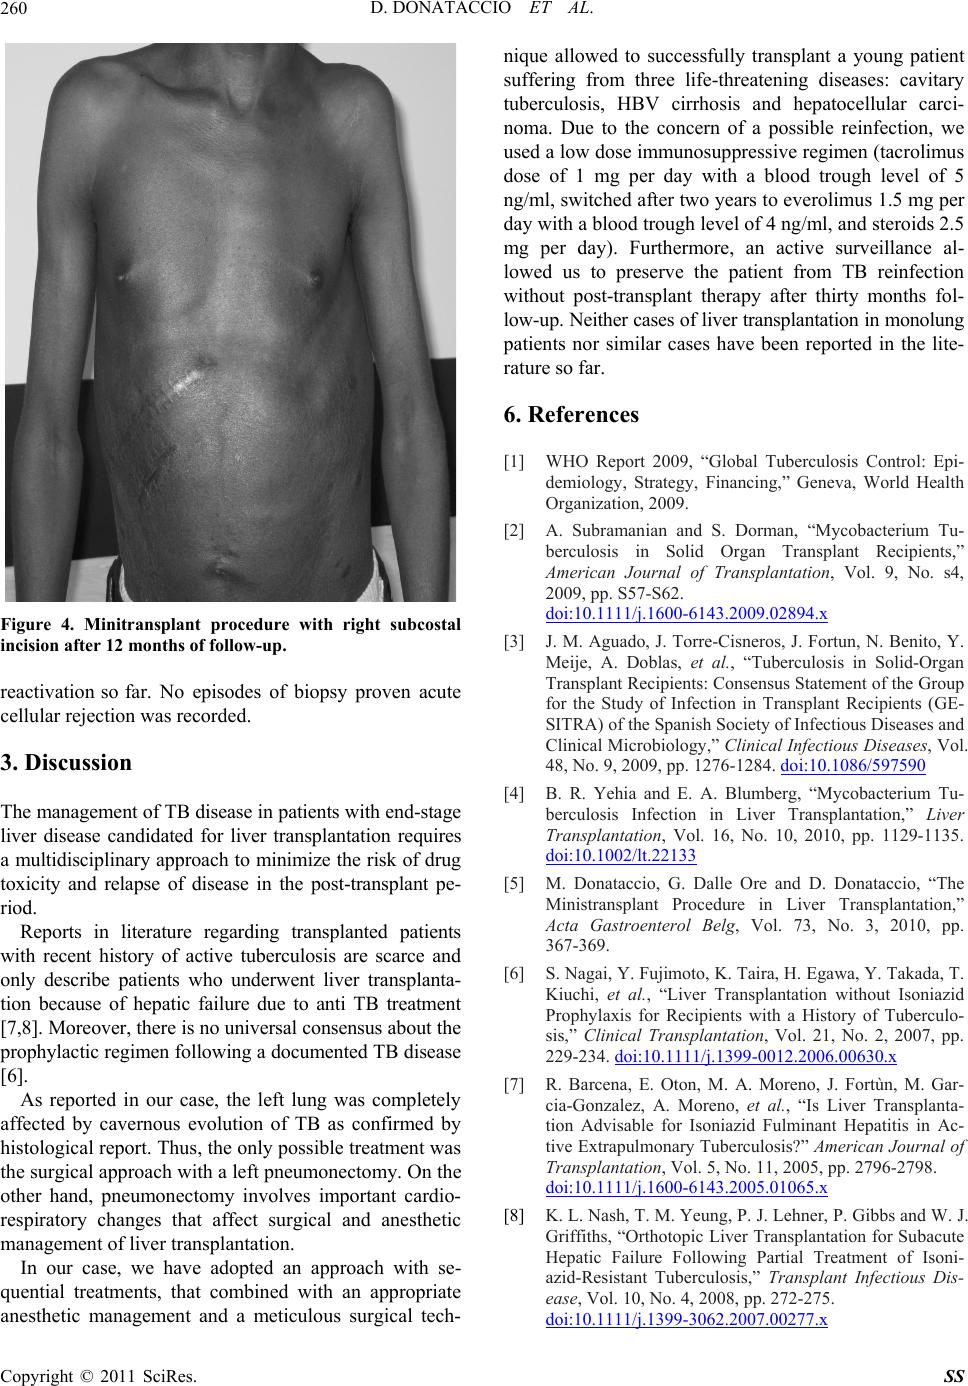 D. DONATACCIO ET AL. Copyright © 2011 SciRes. SS 260 Figure 4. Minitransplant procedure with right subcostal incision after 12 months of follow-up. reactivation so far. No episodes of biopsy proven acute cellular rejection was recorded . 3. Discussion The management of TB disease in patients with end-stage liver disease candidated for liver transplantation requires a multidisciplinary approach to minimize the risk of drug toxicity and relapse of disease in the post-transplant pe- riod. Reports in literature regarding transplanted patients with recent history of active tuberculosis are scarce and only describe patients who underwent liver transplanta- tion because of hepatic failure due to anti TB treatment [7,8]. Moreover, there is no universal consensus about the prophylactic regimen following a documented TB disease [6]. As reported in our case, the left lung was completely affected by cavernous evolution of TB as confirmed by histological report. Thus, the only possible treatment was the surgical approach with a left pneumonectomy. On the other hand, pneumonectomy involves important cardio- respiratory changes that affect surgical and anesthetic management of liver transplantation. In our case, we have adopted an approach with se- quential treatments, that combined with an appropriate anesthetic management and a meticulous surgical tech- nique allowed to successfully transplant a young patient suffering from three life-threatening diseases: cavitary tuberculosis, HBV cirrhosis and hepatocellular carci- noma. Due to the concern of a possible reinfection, we used a low dose immunosuppressive regimen (tacrolimus dose of 1 mg per day with a blood trough level of 5 ng/ml, switched after two years to everolimus 1.5 mg per day with a blood trough level of 4 ng/ml, and steroids 2.5 mg per day). Furthermore, an active surveillance al- lowed us to preserve the patient from TB reinfection without post-transplant therapy after thirty months fol- low-up. Neither cases of liver transplantation in monolung patients nor similar cases have been reported in the lite- rature so far. 6. References [1] WHO Report 2009, “Global Tuberculosis Control: Epi- demiology, Strategy, Financing,” Geneva, World Health Organization, 2009. [2] A. Subramanian and S. Dorman, “Mycobacterium Tu- berculosis in Solid Organ Transplant Recipients,” American Journal of Transplantation, Vol. 9, No. s4, 2009, pp. S57-S62. doi:10.1111/j.1600-6143.2009.02894.x [3] J. M. Aguado, J. Torre-Cisneros, J. Fortun, N. Benito, Y. Meije, A. Doblas, et al., “Tuberculosis in Solid-Organ Transplant Recipients: Consensus Statement of the Group for the Study of Infection in Transplant Recipients (GE- SITRA) of the Spanish Society of Infectious Diseases and Clinical Microbiology,” Clinical Infectious Diseases, Vol. 48, No. 9, 2009, pp. 1276-1284. doi:10.1086/597590 [4] B. R. Yehia and E. A. Blumberg, “Mycobacterium Tu- berculosis Infection in Liver Transplantation,” Liver Transplantation, Vol. 16, No. 10, 2010, pp. 1129-1135. doi:10.1002/lt.22133 [5] M. Donataccio, G. Dalle Ore and D. Donataccio, “The Ministransplant Procedure in Liver Transplantation,” Acta Gastroenterol Belg, Vol. 73, No. 3, 2010, pp. 367-369. [6] S. Nagai, Y. Fujimoto , K. Tair a, H. Egawa, Y. T akada, T. Kiuchi, et al., “Liver Transplantation without Isoniazid Prophylaxis for Recipients with a History of Tuberculo- sis,” Clinical Transplantation, Vol. 21, No. 2, 2007, pp. 229-234. doi:10.1111/j.1399-0012.2006.00630.x [7] R. Barcena, E. Oton, M. A. Moreno, J. Fortùn, M. Gar- cia-Gonzalez, A. Moreno, et al., “Is Liver Transplanta- tion Advisable for Isoniazid Fulminant Hepatitis in Ac- tive Extrapulmonary Tuberculosis?” American Journal of Transplantation, Vol. 5, No. 11, 2005, pp. 2796-2798. doi:10.1111/j.1600-6143.2005.01065.x [8] K. L. Nash, T. M. Yeung, P. J. Lehner, P. Gibbs and W. J. Griffiths, “Orthotopic Liver Transplantation for Subacute Hepatic Failure Following Partial Treatment of Isoni- azid-Resistant Tuberculosis,” Transplant Infectious Dis- ease, Vol. 10, No. 4, 2008, pp. 272-275. doi:10.1111/j.1399-3062.2007.00277.x  D. DONATACCIO ET AL. Copyright © 2011 SciRes. SS 261 Abbreviations TB: tuberculosis; TST: tuberculin skin test; HCC: hepa- tocellular carcinoma; HBV: hepatitis B virus; STP: streptomycin; INH: isoniazid; PZA: pyrazinamide; ETB: ethambutol; RPM: rifampicin; CIP: ciprofloxacin. |