

Paper Menu >>
Journal Menu >>
 Open Journal of Stomatology, 2013, 3, 510-514 OJST http://dx.doi.org/10.4236/ojst.2013.39084 Published Online December 2013 (http://www.scirp.org/journal/ojst/) Necessity of Magnetic Resonance Imaging (MRI) using an appropriate sequence for diagnosis of trigeminal neuralgia associated with intracranial tumor Yoko Yamazaki1*, Tomoko Niimi1, Yuko Ando1, Daisuke Tomizawa1, Masahiko Shimada2 1Orofacial Pain Clinic, Tokyo Medical and Dental University Dental Hospital, Tokyo, Japan 2Orofacial Pain Management, Oral Restitution, Oral Health Sciences, Graduate School of Medical and Dental Sciences, Tokyo Medical and Dental University, Tokyo, Japan Email:*[email protected] Received 18 November 2013; revised 19 December 2013; accepted 28 December 2013 Copyright © 2013 Yoko Yamazaki et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT Aims: Trigeminal neuralgia is generally caused by neurovascular compression. In rare cases intracranial tumors may also lead to this condition. The present study was conducted to identify clinical symptoms and testing methods that are useful for early detection of trigeminal neuralgia associated with intracranial tumor. Methods: Five patients with trigeminal neu- ralgia suspected to be due to intracranial tumor, who visited our department for the first time during the period between February 2007 and March 2009, were examined. We analyzed the medical records and MRI findings of these patients. The clinical symptoms of subjects were compared to those presented at the In- ternational Classification of Headache Disorders. Re- sults: There were no feature symptoms to trigeminal neuralgia caused by intracranial tumors compared with trigeminal neuralgia in general. None of the pa- tients complained of spontaneous headache and nau- sea, which are clinical symptoms characteristic of brain tumor. Head MRI at our hospital was the most accurate method to detect intracranial tumors. Fi- nally four of five patients received brain surgery to remove tumors. Conclusion: Small tumors and roots of the trigeminal nerve may not create accurate im- ages by regular head MRI. Therefore, MRI using the imaging sequence which enables accurate visualiza- tion of roots of the trigeminal nerve is essential to confirm the presence of tumors in patients with sus- pected trigeminal neuralgia. Keywords: Trigeminal Neuralgia; Intracranial Tumor; Benign Tumor; MRI; Neurosurgery 1. INTRODUCTION Trigeminal neuralgia is an excruciating type of pain that occurs in the face and oral cavity. It greatly interferes with daily activities of patients, including eating and face washing. Neurovascular compression is a widely known cause of trigeminal neuralgia [1]. In rare cases intra- cranial tumors may also lead to this condition. For the treatment of trigeminal neuralgia associated with intra- cranial tumors, the tumors are often removed by neuro- surgical procedures in order to eliminate pain [2]. How- ever, the surgery must be performed early because com- plete removal of the tumor may become impossible or the surgery may damage other nerves as the size of the tumor increases. In trigeminal neuralgia pain arises in the areas of the jaw, oral cavity and face; as a result some patients first visit a dentist for treatment of the condition. If clinical features or testing methods to identify trigeminal neural- gia caused by tumors were known, dentists could easily refer patients to neurosurgeons and this could contribute to early detection of tumors. The present study was conducted to identify clinical symptoms and testing methods that are useful for early detection of intracranial tumors. We retrospectively ex- amined the clinical symptoms and imaging tests of pa- tients with trigeminal neuralgia treated at the Orofacial Pain Clinic, Tokyo Medical and Dental University Hos- pital of Dentistry, whose neuralgia was speculated to be caused by intracranial tumors. 2. METHODS Five patients with trigeminal neuralgia suspected to be due to intracranial tumor, who visited our department for the first time during the period between February 2007 *Corresponding author. OPEN ACCESS 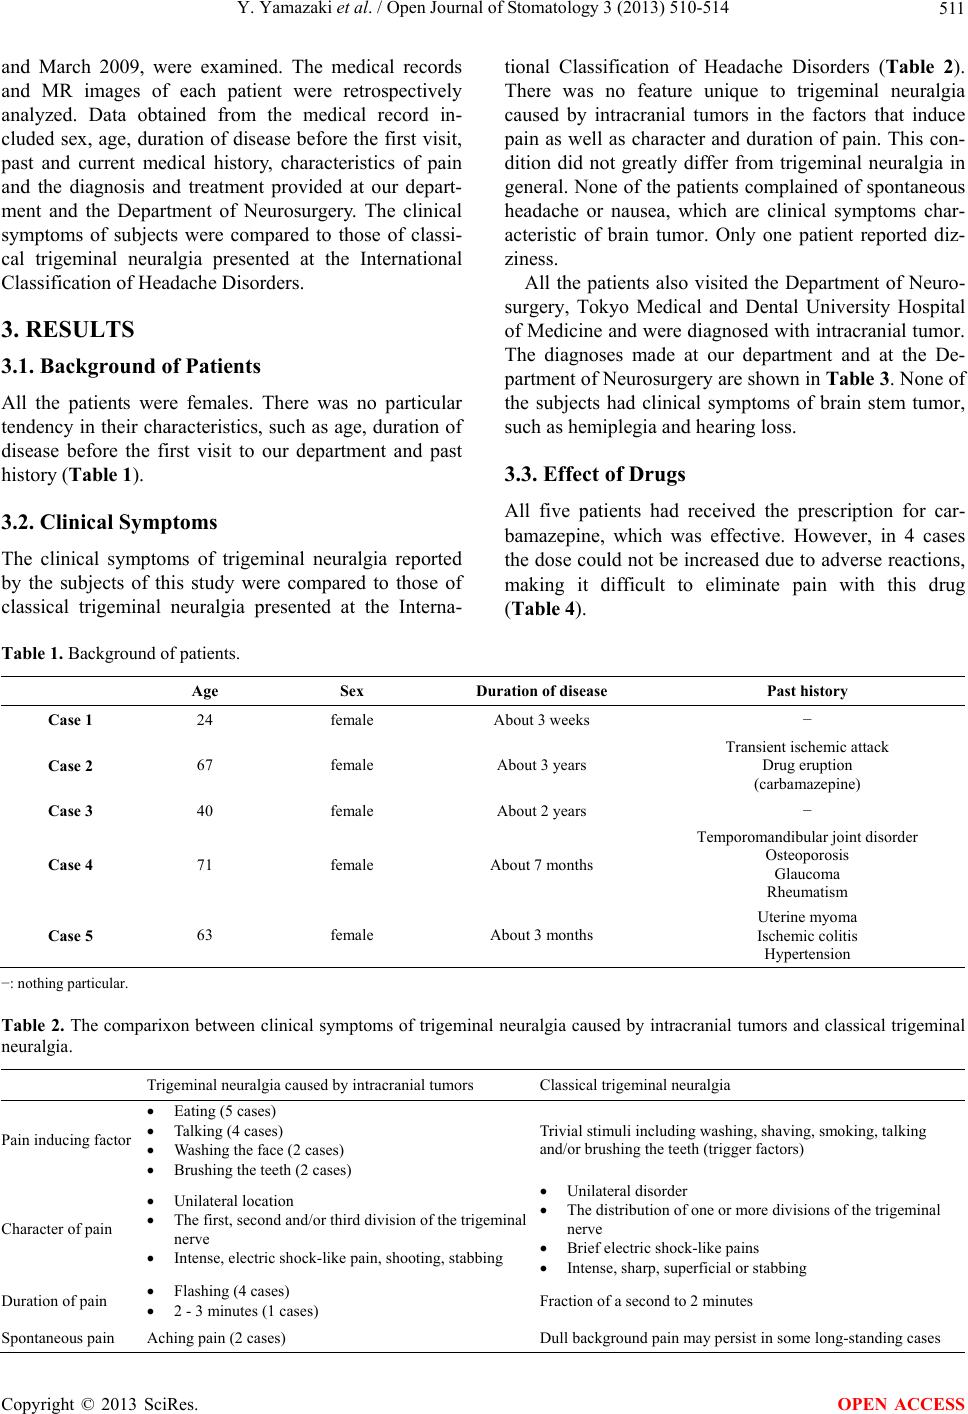 Y. Yamazaki et al. / Open Journal of Stomatology 3 (2013) 510-514 511 and March 2009, were examined. The medical records and MR images of each patient were retrospectively analyzed. Data obtained from the medical record in- cluded sex, age, duration of disease before the first visit, past and current medical history, characteristics of pain and the diagnosis and treatment provided at our depart- ment and the Department of Neurosurgery. The clinical symptoms of subjects were compared to those of classi- cal trigeminal neuralgia presented at the International Classification of Headache Disorders. 3. RESULTS 3.1. Background of Patients All the patients were females. There was no particular tendency in their characteristics, such as age, duration of disease before the first visit to our department and past history (Table 1). 3.2. Clinical Symptoms The clinical symptoms of trigeminal neuralgia reported by the subjects of this study were compared to those of classical trigeminal neuralgia presented at the Interna- tional Classification of Headache Disorders (Table 2). There was no feature unique to trigeminal neuralgia caused by intracranial tumors in the factors that induce pain as well as character and duration of pain. This con- dition did not greatly differ from trigeminal neuralgia in general. None of the patients complained of spontaneous headache or nausea, which are clinical symptoms char- acteristic of brain tumor. Only one patient reported diz- ziness. All the patients also visited the Department of Neuro- surgery, Tokyo Medical and Dental University Hospital of Medicine and were diagnosed with intracranial tumor. The diagnoses made at our department and at the De- partment of Neurosurgery are shown in Table 3. None of the subjects had clinical symptoms of brain stem tumor, such as hemiplegia and hearing loss. 3.3. Effect of Drugs All five patients had received the prescription for car- bamazepine, which was effective. However, in 4 cases the dose could not be increased due to adverse reactions, making it difficult to eliminate pain with this drug (Table 4). Table 1. Background of patients. Age Sex Duration of disease Past history Case 1 24 female About 3 weeks − Case 2 67 female About 3 years Transient ischemic attack Drug eruption (carbamazepine) Case 3 40 female About 2 years − Case 4 71 female About 7 months Temporomandibular joint disorder Osteoporosis Glaucoma Rheumatism Case 5 63 female About 3 months Uterine myoma Ischemic colitis Hypertension −: nothing particular. Table 2. The comparixon between clinical symptoms of trigeminal neuralgia caused by intracranial tumors and classical trigeminal neuralgia. Trigeminal neuralgia caused by intracranial tumors Classical trigeminal neuralgia Pain inducing factor Eating (5 cases) Talking (4 cases) Washing the face (2 cases) Brushing the teeth (2 cases) Trivial stimuli including washing, shaving, smoking, talking and/or brushing the teeth (trigger factors) Character of pain Unilateral location The first, second and/or third division of the trigeminal nerve Intense, electric shock-like pain, shooting, stabbing Unilateral disorder The distribution of one or more divisions of the trigeminal nerve Brief electric shock-like pains Intense, sharp, superficial or stabbing Duration of pain Flashing (4 cases) 2 - 3 minutes (1 cases) Fraction of a second to 2 minutes Spontaneous pain Aching pain (2 cases) Dull background pain may persist in some long-standing cases Copyright © 2013 SciRes. OPEN ACCESS 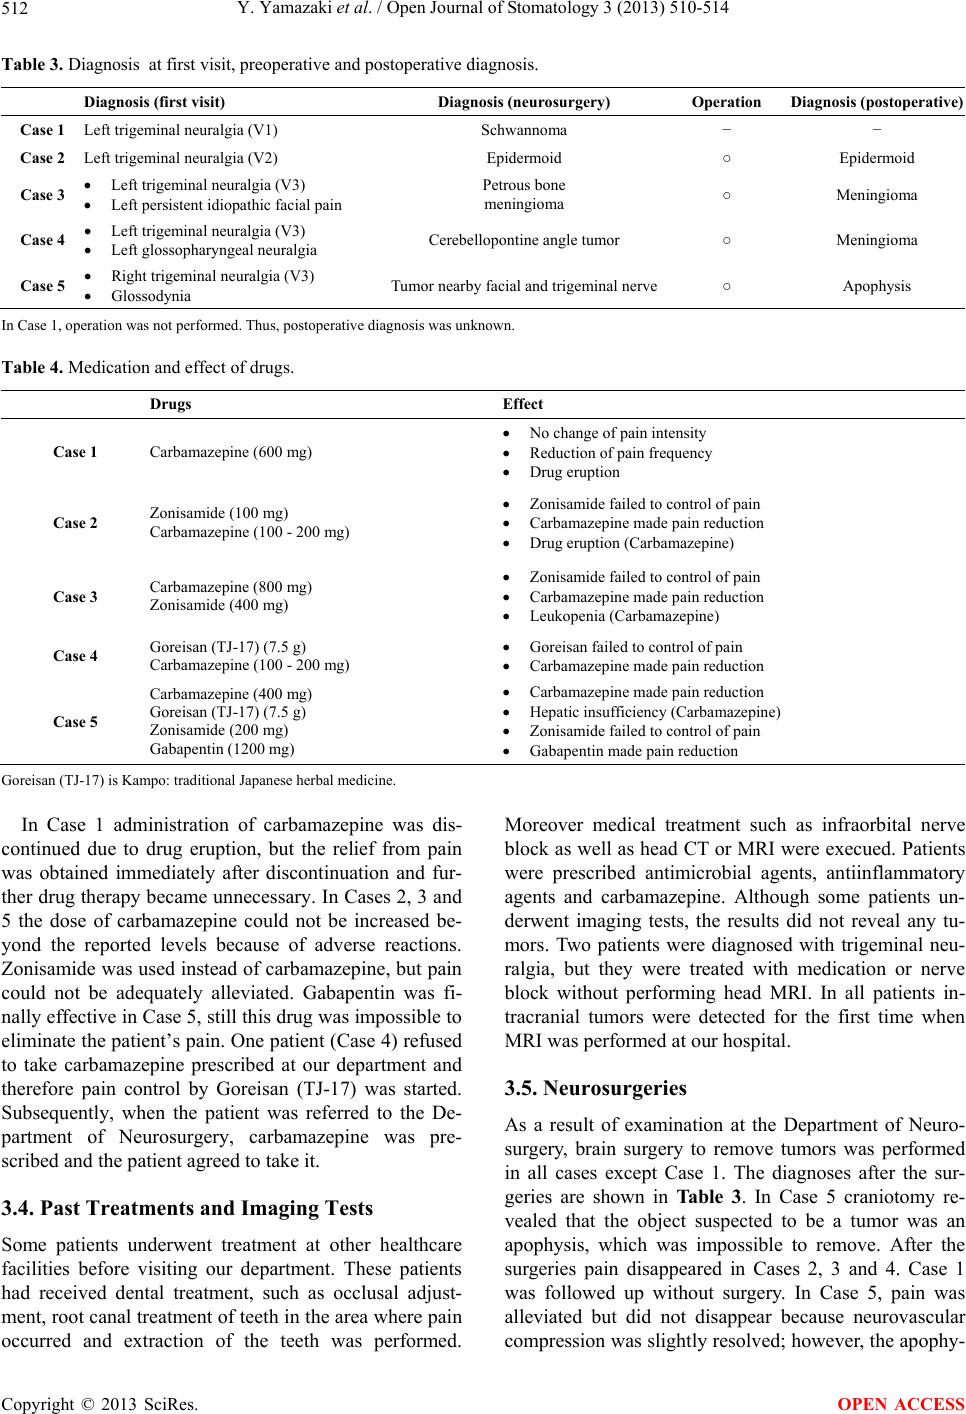 Y. Yamazaki et al. / Open Journal of Stomatology 3 (2013) 510-514 512 Table 3. Diagnosis at first visit, preoperative and postoperative diagnosis. Diagnosis (first visit) Diagnosis (neurosurgery) Operation Diagnosis (postoperative) Case 1 Left trigeminal neuralgia (V1) Schwannoma − − Case 2 Left trigeminal neuralgia (V2) Epidermoid ○ Epidermoid Case 3 Left trigeminal neuralgia (V3) Left persistent idiopathic facial pain Petrous bone meningioma ○ Meningioma Case 4 Left trigeminal neuralgia (V3) Left glossopharyngeal neuralgia Cerebellopontine angle tumor ○ Meningioma Case 5 Right trigeminal neuralgia (V3) Glossodynia Tumor nearby facial and trigeminal nerve○ Apophysis In Case 1, operation was not performed. Thus, postoperative diagnosis was unknown. Table 4. Medication and effect of drugs. Drugs Effect Case 1 Carbamazepine (600 mg) No change of pain intensity Reduction of pain frequency Drug eruption Case 2 Zonisamide (100 mg) Carbamazepine (100 - 200 mg) Zonisamide failed to control of pain Carbamazepine made pain reduction Drug eruption (Carbamazepine) Case 3 Carbamazepine (800 mg) Zonisamide (400 mg) Zonisamide failed to control of pain Carbamazepine made pain reduction Leukopenia (Carbamazepine) Case 4 Goreisan (TJ-17) (7.5 g) Carbamazepine (100 - 200 mg) Goreisan failed to control of pain Carbamazepine made pain reduction Case 5 Carbamazepine (400 mg) Goreisan (TJ-17) (7.5 g) Zonisamide (200 mg) Gabapentin (1200 mg) Carbamazepine made pain reduction Hepatic insufficiency (Carbamazepine) Zonisamide failed to control of pain Gabapentin made pain reduction Goreisan (TJ-17) is Kampo: traditional Japanese herbal medicine. In Case 1 administration of carbamazepine was dis- continued due to drug eruption, but the relief from pain was obtained immediately after discontinuation and fur- ther drug therapy became unnecessary. In Cases 2, 3 and 5 the dose of carbamazepine could not be increased be- yond the reported levels because of adverse reactions. Zonisamide was used instead of carbamazepine, but pain could not be adequately alleviated. Gabapentin was fi- nally effective in Case 5, still this drug was impossible to eliminate the patient’s pain. One patient (Case 4) refused to take carbamazepine prescribed at our department and therefore pain control by Goreisan (TJ-17) was started. Subsequently, when the patient was referred to the De- partment of Neurosurgery, carbamazepine was pre- scribed and the patient agreed to take it. 3.4. Past Treatments and Imaging Tests Some patients underwent treatment at other healthcare facilities before visiting our department. These patients had received dental treatment, such as occlusal adjust- ment, root canal treatment of teeth in the area where pain occurred and extraction of the teeth was performed. Moreover medical treatment such as infraorbital nerve block as well as head CT or MRI were execued. Patients were prescribed antimicrobial agents, antiinflammatory agents and carbamazepine. Although some patients un- derwent imaging tests, the results did not reveal any tu- mors. Two patients were diagnosed with trigeminal neu- ralgia, but they were treated with medication or nerve block without performing head MRI. In all patients in- tracranial tumors were detected for the first time when MRI was performed at our hospital. 3.5. Neurosurgeries As a result of examination at the Department of Neuro- surgery, brain surgery to remove tumors was performed in all cases except Case 1. The diagnoses after the sur- geries are shown in Table 3. In Case 5 craniotomy re- vealed that the object suspected to be a tumor was an apophysis, which was impossible to remove. After the surgeries pain disappeared in Cases 2, 3 and 4. Case 1 was followed up without surgery. In Case 5, pain was alleviated but did not disappear because neurovascular compression was slightly resolved; however, the apophy- Copyright © 2013 SciRes. OPEN ACCESS  Y. Yamazaki et al. / Open Journal of Stomatology 3 (2013) 510-514 513 sis could not be removed. 4. DISCUSSION Trigeminal neuralgia is one of the most painful afflic- tions of humanity [3], which substantially lowers the patient’s quality of life. It is roughly divided into classi- cal and symptomatic trigeminal neuralgia [4]. Trigeminal neuralgia caused by tumors as examined in this study is a rare type of symptomatic trigeminal neuralgia and its overall incidence is low [5]. Ono et al. reported that among 243 patients with trigeminal neuralgia, pain was attributed to pontine angle tumors in 25 patients (10.3%) [6]. Other studies reported that about 10% of trigeminal neuralgia cases were caused by brain tumors [2,7]. At our department about 2.9% of trigeminal neuralgia cases were caused by brain tumors during the study period. All five patients examined in this study visited the Department of Neurosurgery and four of them later un- derwent craniotomy. After the tumors were removed, the pain disappeared in three patients, indicating that pain control in trigeminal neuralgia caused by intracranial tumors requires tumor resection. On the other hand, in Case 5 with a bony prominence compressing nerves, pain was alleviated but not eliminated after the surgery. The compression of the trigeminal nerve remained, because the bony prominence could not be resection. Tumors that cause trigeminal neuralgia include sch- wannoma, meningioma and epidermoid cyst, which are mostly benign [8]. Because benign tumors grow slowly and are unlikely to cause intracranial hypertension, clini- cal symptoms such as nausea and dizziness do not de- velop so often [9]. However, when tumors grow and oc- cupy a large volume in the vicinity of brain stem, they can not only affect the trigeminal nerve but also influ- ence activities of daily life. Moreover, when tumors in- crease in size, complete resection would be difficult be- cause of the possibility of damaging various nerves dur- ing the surgery. Therefore, it could be essential that early detection of intracranial tumors is performed and a con- tinuous follow-up is necessary. There were no characteristic clinical symptoms in this study. Other investigators reported that there was no clinical feature characteristic of trigeminal neuralgia caused by tumors [9]. Some reports suggest that vascular compression or tumoral compression produces the same pathologic findings. Therefore, the present study indicates that it is difficult to speculate about the presence or absence of tumors based only on clinical symptoms. The present study demonstrated that head MRI was the most accurate method to detect tumors. In the algo- rithm for diagnosis of trigeminal neuralgia proposed by Kleef et al., MRI is given high priority in the diagnostic procedure [10]. There is also a report suggesting that MRI was useful in diagnosis of symptomatic trigeminal neuralgia [11,12]. In our department head MRI is performed for almost all patients with suspected trigeminal neuralgia. The MRI device used in Tokyo Medical and Dental Univer- sity Hospital (Magnetom Vision; Siemens, Erlangen, Germany) creates images with a magnetic force of 1.5 Tesla. Because early-stage tumors are small and roots of the trigeminal nerve occupy a very limited area, regular head MRI may not create accurate images. Therefore, MRI using an imaging sequence that allows for accurate visualization of roots of the trigeminal nerve would be necessary. We use fast imaging with steady-state preci- sion (FISP) and constructive interference in steady state (CISS) as well as T1 and T2-weighted images. These imaging sequences use the following paramaters; FISP: 39/6.5 (repetition time msec/echo time msec), 20˚ flip angle, CISS: 12.25/5.9, 70˚ flip angle on CISS. In par- ticular CISS enables visualization of not only arteries but also veins [13]. In FISP and CISS we enlarge the image of the area of pons and visualize it with a slice width of 1 mm. By doing so, we can see the details of the area of roots of the trigeminal nerve (Figure 1). Therefore, small tumors that cannot be confirmed by regular MRI could be detected using this method, so head MRI would be the most accurate method to detect intracranial tumors at our hospital whether or not patients are examined with regu- lar MRI at other hospitals. Figure 1. This image is MRI using an imaging sequence of CISS in Case 2. The arrow is an epidermoid tumor in the left cerebellopontine angle. On CISS imaging, the blood vessel and the nerve were shown as structures with a low signal intensity, and the cerebrospinal fluid was shown as a structure with a high signal intensity. The structures were clearly visualized. Copyright © 2013 SciRes. OPEN ACCESS  Y. Yamazaki et al. / Open Journal of Stomatology 3 (2013) 510-514 Copyright © 2013 SciRes. 514 [7] Nomura, T., Ikezaki, K., Matsushima, T. and Fukui, M. (1994) Trigeminal neuralgia: Differentiation between in- tracranial mass lesions and ordinary vascular compres- sion as causative lesions. Neurosurgical Review, 17, 51- 57. http://dx.doi.org/10.1007/BF00309988 Thus, MRI using an appropriate imaging sequence seems to be indispensable for the detection of tumors. 5. ACKNOWLEDGEMENTS [8] Love, S. and Coakham, H.B. (2001) Trigeminal neuralgia: Pathology and pathogenesis. Brain, 124, 2347-2360. http://dx.doi.org/10.1093/brain/124.12.2347 The authors thank the Department of oral and maxillofacial radiology, Tokyo Medical and Dental Hospital of dentistry for presenting details of MRI. [9] Cirak, B., Kiymaz, N. and Arslanoglu. A. (2004) Trige- minal neuralgia caused by intracranial epidermoid tumor: Report of a case and review of the different therapeutic modalities. Pain Physician, 7, 129-132. REFERENCES [1] Kabatas, S., Karasu, A., Civelek, E., Sabanci, A.P., Hep- gul, K.T. and Teng, Y.D. (2009) Microvascular decom- pression as a surgical management for trigeminal neural- gia: Long-term follow-up and review of the literature. Neurosurgical Review, 32, 87-93. http://dx.doi.org/10.1007/s10143-008-0171-3 [10] van Kleef, M., van Genderen, W.E., Narouze, S., Nur- mikko, T.J., van Zundert, J., Geurts, J.W. and Mekhail, N. (2009) 1. Trigeminal neuralgia. Pain Practice: The Offi- cial Journal of World Institute of Pain, 9, 252-259. [11] Goh, B.T., Poon, C.Y. and Peck, R.H. (2001) The impor- tance of routine magnetic resonance imaging in trigemi- nal neuralgia diagnosis. Oral Surgery, Oral Medicine, Oral Pathology, Oral Radiology, and Endodontics, 92, 424-429. http://dx.doi.org/10.1067/moe.2001.115130 [2] Barker 2nd, F.G., Jannetta, P.J., Babu, R.P., Pomonis, S., Bissonette, D.J. and Jho, H.D. (1996) Long-term outcome after operation for trigeminal neuralgia in patients with posterior fossa tumors. Journal of Neurosurgery, 84, 818- 825. http://dx.doi.org/10.3171/jns.1996.84.5.0818 [12] Gronseth, G., Cruccu, G., Alksne, J., Argoff, C., Brainin, M., Burchiel, K., Nurmikko, T. and Zakrzewska, J.M. (2008) Practice parameter: the diagnostic evaluation and treatment of trigeminal neuralgia (an evidence-based re- view): Report of the Quality Standards Subcommittee of the American Academy of Neurology and the European Federation of Neurological Societies. Neurology , 71, 1183- 1190. http://dx.doi.org/10.1212/01.wnl.0000326598.83183.04 [3] Okeson, J.P. (2005) Neuropathic pains. In: Harmon, L., Ed., Bell’s orofacial pains: The clinical management of orofacial pain, Sixth Edition, Quintessence, Tokyo, 449- 517. [4] Headache Classification Subcommittee of the Interna- tional Headache Society (2004) The international classi- fication of headache disorders: 2nd edition. Cephalalgia, 24, 9-160. [13] Yoshino, N., Akimoto, H., Yamada, I., Nagaoka, T., Tetsumura, A., Kurabayashi, T., Honda, E., Nakamura, S. and Sasaki, T. (2003) Trigeminal neuralgia: Evaluation of neuralgic manifestation and site of neurovascular com- pression with 3D CISS MR imaging and MR angiogra- phy. Radiology, 228, 539-545. http://dx.doi.org/10.1148/radiol.2282020439 [5] Cirak, B., Kiymaz, N. and Arslanoglu, A. (2004) Trige- minal neuralgia caused by intracranial epidermoid tumor: Report of a case and review of the different therapeutic modalities. Pain Physician, 7, 129-132. [6] Nakagawa, K., Aoyagi, M., Kawano, Y. and Ohno, K. (2009) Clinical and operative findings in patients with trigeminal neuralgia caused by brain tumors. No Shinkei Geka, 37, 863-871. OPEN ACCESS |