

Paper Menu >>
Journal Menu >>
 Open Journal of Stomatology, 2013, 3, 504-506 OJST http://dx.doi.org/10.4236/ojst.2013.39082 Published Online December 2013 (http://www.scirp.org/journal/ojst/) Calcifying cystic odontogenic tumour manifesting in the maxillary antrum: Case report Eunice Kihara1, Richard Owino2, Josiah Otwoma1, Elizabeth Dimba1, Mark Chindia1 1Department of Oral & Maxillofacial Surgery—Oral Pathology & Oral Medicine, University of Nairobi, Nairobi, Kenya 2Department of Paediatric Dentistry & Orthodontics, University of Nairobi, Nairobi, Kenya Email: [email protected] Received 31 October 2013; revised 1 December 2013; accepted 12 December 2013 Copyright © 2013 Eunice Kihara et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT A case is presented of a 15-year-old boy who mani- fested the calcifying cystic odontogenic tumour (CCOT) in the left maxillary antrum of an unknown duration. In addition, the patient had a high arched palate and multiple impacted teeth of the normal series and su- pernumerary type including mesiodens as demon- strated in an orthopantomograph. Keywords: Case Reports; Odontogenic Cyst; Calcifying; Odontogenic Tumours; Maxillary Sinus 1. INTRODUCTION Generally, benign odontogenic neoplasms are relatively rare lesions that are derived from either the epithelial an d mesenchymal components or the remnant elements of the developing tooth germs. These lesions are often classi- fied according to location as p eripheral or central entities [1-4]. In this category of diseases, the calcifying cystic odontogenic tumour (CCOT) is a particularly rare benign entity that is characterized by an ameloblastoma-like epithelium and ghost cells that have the potential to un- dergo calcification [4-6]. The lesion usually appears as a painless, slow-growing tumour that may involve the maxilla or mandible in the anterior segments [1,3]. We report a 15-year-old boy who presented with CCOT man- ifesting in the left maxillary antrum associated with den- tal malformation, tooth impaction and a high arched pal- ate. 2. CASE REPORT A 15-year-old boy was referred to our clinic for evalua- tion and management of a persistent swelling of the left maxilla that had, apparently, been noted nearly two years previously. Over that period, the swelling had been es- sentially painless. However, the patient reported that the swelling had then become painful. In addition, he also experienced a feeling of stuffiness in the left nostril. The patient’s general medical and dental history was unre- markable. On examination, the patient manifested a non- tender mass causing facial asymmetry with fullness in the left nasolabial fo ld extending towards the bod y of the zygoma. Intraorally, there was total left maxillary sulcu- lar fullness, a mixed dentition and a generalized malposi- tioning of some teeth in both arches in addition to a high arched palate. A panoramic radiograph rev ealed multiple bony impacted teeth of the normal series and thos e of the supernumerary type and mesiodens “Figure 1”. The ra- diograph also demonstrated a remarkably expanded op- acified left maxillary sinus. Under a local anaesthetic, aspiration of the lesion yielded a shimmering amber-coloured cystic fluid. Then an open incisional biopsy was obtained which on histo- pathological examination demonstrated a fibrous capsule associated with odontogenic cells with low mitotic indi- ces and no pleomorphism. In addition, there were armo- phous areas of eosinophilic material interspersed within the cells. Ghost cells were prominent “Figure 2”. The tu- mour was, thereafter, totally extirpated under general anaesthesia “Figure 3”. The patient remains well after about a 1-year regular follow up. 3. DISCUSSION The most recent WHO classification proposes the diag- nostic designations CCOT and dentinogenic ghost cell tumour (DGCT) to differentiate between the cystic and solid lesion [5]. Remarkably, these lesions may occur in association with other odontogenic tumours including, in most instances, the adenomatoid odontogenic tumour [7], ameloblastoma and odontoma [6] and odontogenic kera- tocystic tumour [8]. Practically, then, obtaining an ade- quate biopsy sp ecimen that is represen tative of the entire lesion during histopathological analysis has to be man- OPEN ACCESS 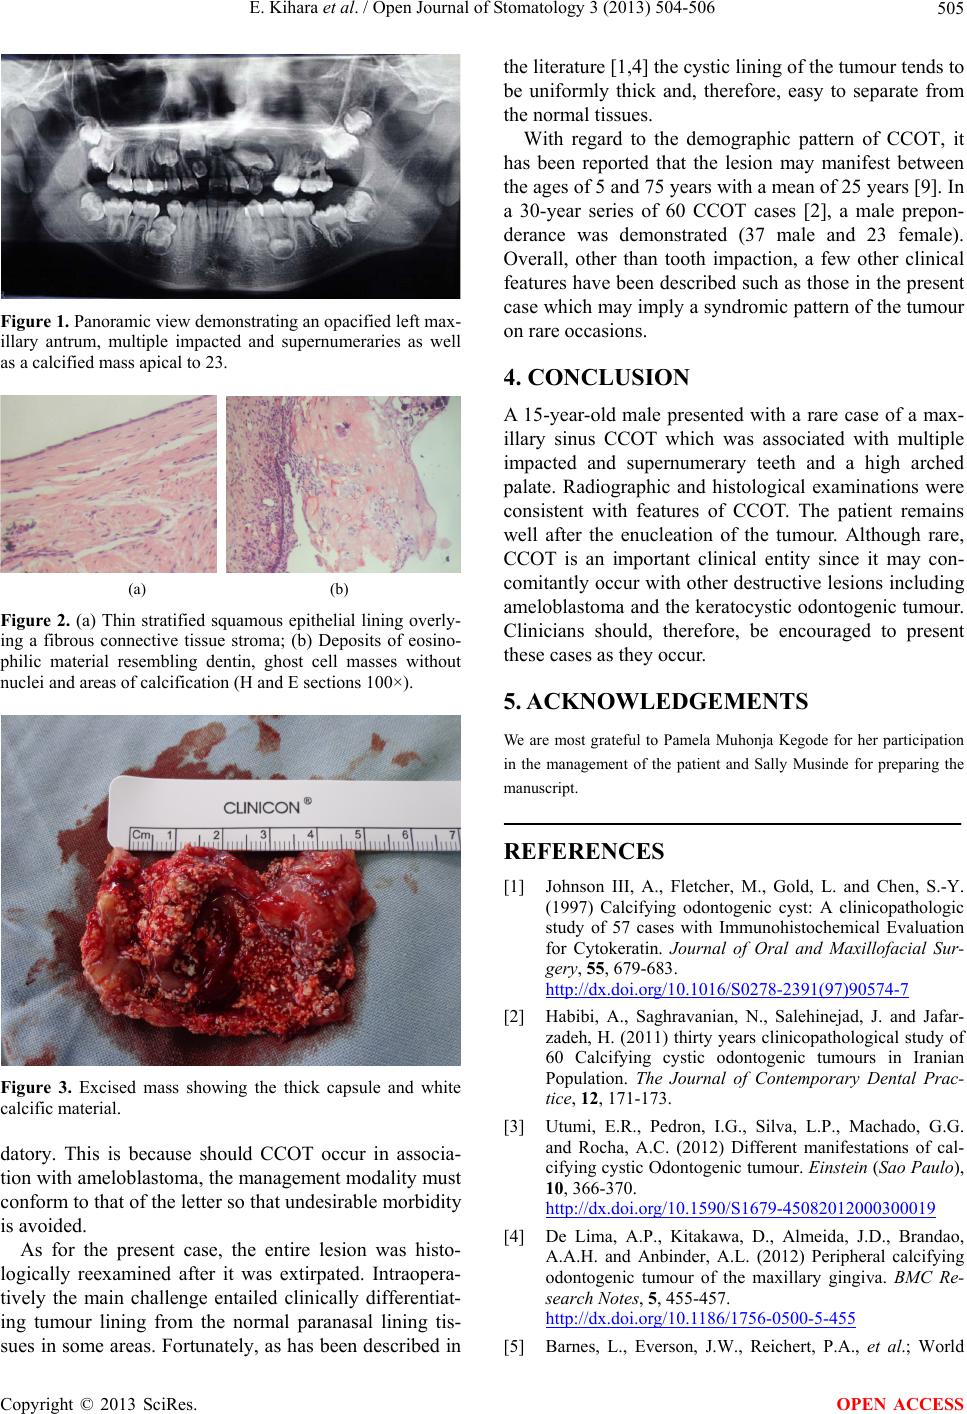 E. Kihara et al. / Open Journal of Stomatology 3 (2013) 504-506 505 Figure 1. Panoramic view demonstrating an opacified left max- illary antrum, multiple impacted and supernumeraries as well as a calcified mass apical to 23. (a) (b) Figure 2. (a) Thin stratified squamous epithelial lining overly- ing a fibrous connective tissue stroma; (b) Deposits of eosino- philic material resembling dentin, ghost cell masses without nuclei and areas of calcification (H and E sections 100×). Figure 3. Excised mass showing the thick capsule and white calcific material. datory. This is because should CCOT occur in associa- tion with ameloblastoma, the management modality must conform to that of th e letter so that und esirable morbid ity is avoided. As for the present case, the entire lesion was histo- logically reexamined after it was extirpated. Intraopera- tively the main challenge entailed clinically differentiat- ing tumour lining from the normal paranasal lining tis- sues in some areas. Fortunately, as has been described in the literature [1,4] the cystic linin g of the tumour tends to be uniformly thick and, therefore, easy to separate from the normal tissues. With regard to the demographic pattern of CCOT, it has been reported that the lesion may manifest between the ages of 5 and 75 years with a mean of 25 years [9]. In a 30-year series of 60 CCOT cases [2], a male prepon- derance was demonstrated (37 male and 23 female). Overall, other than tooth impaction, a few other clinical features have been described such as those in the present case which may imply a syndromic pattern of the tumour on rare occasions. 4. CONCLUSION A 15-year-old male presented with a rare case of a max- illary sinus CCOT which was associated with multiple impacted and supernumerary teeth and a high arched palate. Radiographic and histological examinations were consistent with features of CCOT. The patient remains well after the enucleation of the tumour. Although rare, CCOT is an important clinical entity since it may con- comitantly occur with other destructive lesions including ameloblastoma and the keratocystic odontogenic tumour. Clinicians should, therefore, be encouraged to present these cases as they occur. 5. ACKNOWLEDGEMENTS We are most grateful to Pamela Muhonja Kegode for her participation in the management of the patient and Sally Musinde for preparing the manuscript. REFERENCES [1] Johnson III, A., Fletcher, M., Gold, L. and Chen, S.-Y. (1997) Calcifying odontogenic cyst: A clinicopathologic study of 57 cases with Immunohistochemical Evaluation for Cytokeratin. Journal of Oral and Maxillofacial Sur- gery, 55, 679-683. http://dx.doi.org/10.1016/S0278-2391(97)90574-7 [2] Habibi, A., Saghravanian, N., Salehinejad, J. and Jafar- zadeh, H. (2011) thirty years clinicopathological study of 60 Calcifying cystic odontogenic tumours in Iranian Population. The Journal of Contemporary Dental Prac- tice, 12, 171-173. [3] Utumi, E.R., Pedron, I.G., Silva, L.P., Machado, G.G. and Rocha, A.C. (2012) Different manifestations of cal- cifying cystic Odontogenic tumour. Einstein (Sao Paulo), 10, 366-370. http://dx.doi.org/10.1590/S1679-45082012000300019 [4] De Lima, A.P., Kitakawa, D., Almeida, J.D., Brandao, A.A.H. and Anbinder, A.L. (2012) Peripheral calcifying odontogenic tumour of the maxillary gingiva. BMC Re- search Notes, 5, 455-457. http://dx.doi.org/10.1186/1756-0500-5-455 [5] Barnes, L., Everson, J.W., Reichert, P.A., et al.; World Copyright © 2013 SciRes. OPEN ACCESS  E. Kihara et al. / Open Journal of Stomatology 3 (2013) 504-506 Copyright © 2013 SciRes. OPEN ACCESS 506 Health Organisation Classification of Tumours (2005) Pathology and genetics of tumours of the head and neck. Chapter 6. Odontogenic tumours. IARC, Lyon, 283-327. [6] Slootweg, P.J. (2007) Dental pathology: A practical in- troduction. Springer, Berlin. [7] Zeitoun, I.M., Dhanrajani, P.J. and Masodomi, H.A. (1996) Adenomatoid odontogenic tumour arising in cal- cifying Odontogenic cyst. Journal of Oral and Maxillo- facial Surgery, 54, 634-637. http://dx.doi.org/10.1016/S0278-2391(96)90650-3 [8] Basile, J.R., Klene, C. and Lin, Y.L. (2010) Calcifying odontogenic cyst with odontogenic keratocyst: A case report and review of the literature. Oral Surgery, Oral Medicine, Oral Pathology, Oral Radiology and Endodon- tology, 109, e 4 0 -e45. http://dx.doi.org/10.1016/j.tripleo.2009.12.026 [9] Daniels, J.S.M. (2006) Recurrent calcifying odontogenic cyst involving the maxillary sinus. Oral Surgery, Oral Medicine, Oral Pathology, Oral Radiology and Endodon- tology, 101, 356-362. |