

Paper Menu >>
Journal Menu >>
 Vol.2, No.9, 513-516 (2013) Case Reports in Clinical Medicine http://dx.doi.org/10.4236/crcm.2013.29134 Fungal sinusitis with ocular involvement: Case report Achyut N. Pandey1*, Anil Kakde2 1Department of Ophthalmolog y, VCSG Medical College and Research Institute, Srinagar-Garhwal, Uttarakhand, India; *Corresponding Author: [email protected] 2Eye Q Super Speciality Eye Hospital, Gurgaon, India Received 7 October 2013; revised 5 November 2013; accepted 3 December 2013 Copyright © 2013 Achyut N. Pandey, Anil Kakde. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. In accordance of the Creative Commons Attribution License all Copyrights © 2013 are reserved for SCIRP and the owner of the intellectual property Achyut N. Pandey, Anil Kakde. All Copyright © 2013 are guarded by law and by SCIRP as a guardian. ABSTRACT Rhino-orbital-cerebral mucormycosis (ROCM) is an acute, often fatal, fungal infection caused by members of the class Zygomycetes and the or- der Mucorales. The genus Rhizopus accounts for most cases of ROCM. The disease is char- acterized by fungal hyphal invasion of blood vessels resulting in thrombosis and i nfarction of the nasal, paranasal sinus, orbital, and cerebral tissues. The most commonly associated condi- tion is diabetes mellitus; other associated con- ditions include immunocompromised states, re- nal disease, deferoxamine use and acidotic sta- tes. The most frequent sites of infection are pulmonary, rhinocerebral, cutaneous and dis- seminated. Rhino-orbital and Rhino-cerebral are two forms of the disease. As such the condition is a medical emergency. Early recognition and treatment are essential because it may lead to death in a few days. CROP usually begins in the palate or paranasal sinuses and rapidly spreads to the orbital contents. Proptosis, loss of vision and ophthalmoplegia occur and death from ce- rebral involvement commonly ensues. The fun- gus tends to invade arteries and cause throm- bosis and tissue infarction. Rhizopus is the most commonly isolated genus in CROP, ac- counting for almost all cases. The diagnosis can be strongly suspected by the characteristic clinical manifestations. Therapy includes the treatment of the underlying disease, surgical excision of the necrotic tissue containing fungal element s and the systemic administr ation of am- photericin-B. Here we report the clinical fea- tures of a 32-years-old man presented mucor- mycosis. Keywords: Diabetes Mellitus; Mucormycosis; Rhizopus spp. 1. CASE REPORT A 32-years-old male patient presented a history of pain in the nose and defective vision in the left eye since one week. The pain was not relieved. He was apparently all right one week prior. He was a diabetic incidientally found one week back only. On admission, he was found to be a afebrile, conscious and well oriented to the time and place, with a BP of 140/90 mmHg, a pulse of 82/min and with a swelling on the nose. Vision is in RE 6/18 and LE 6/HM. On examination patient is found to have con- vergent squint. Extra ocular movements were restricted in all six gazes, indicating the involvement of 3, 5 and 6 cranial nerve (Figure 1). Corneal sensation is decreased in BE .There was no proptosis presented. IOP is in RE 22.4 and LE 18.9. People in both eyes were round, re- acting to light both direct and consensual light reaction. Pt was dilated for fundus examination, and BE fundus found to be normal. His fasting blood sugar was 296 mg/dl, sodium was 12 mEq/L, potassium was 2.5 mEq/L., urea was 47 mg/dl, creatinin e was 0.9 mg/dl and haemo- globin was 11.7 gm%. All other lab investigations are found to be normal. His nasal swab and maxillary and eth- moid sinus curettages were received in the microbiology laboratory for KOH mounts and fungal cultures to check for mucormycosis. The microscopic examination of the biopsy material and the nasal discharge was done in 10% KOH wet mounts. It showed the characteristic broad, aseptate, branched hyphae (Figures 2, 3). The fungus was grown on Sabouraud’s dextrose agar at 37˚C. A mi- croscopic examination of the growth which was done in a lactophenol cotton blue mount, revealed that it was Rhi- zopus (Figure 4). Further patient is advised for CT scan orbit and para nasal sinuses for orbital or cerebral spread Copyright © 2013 SciRes. OPEN A CCESS 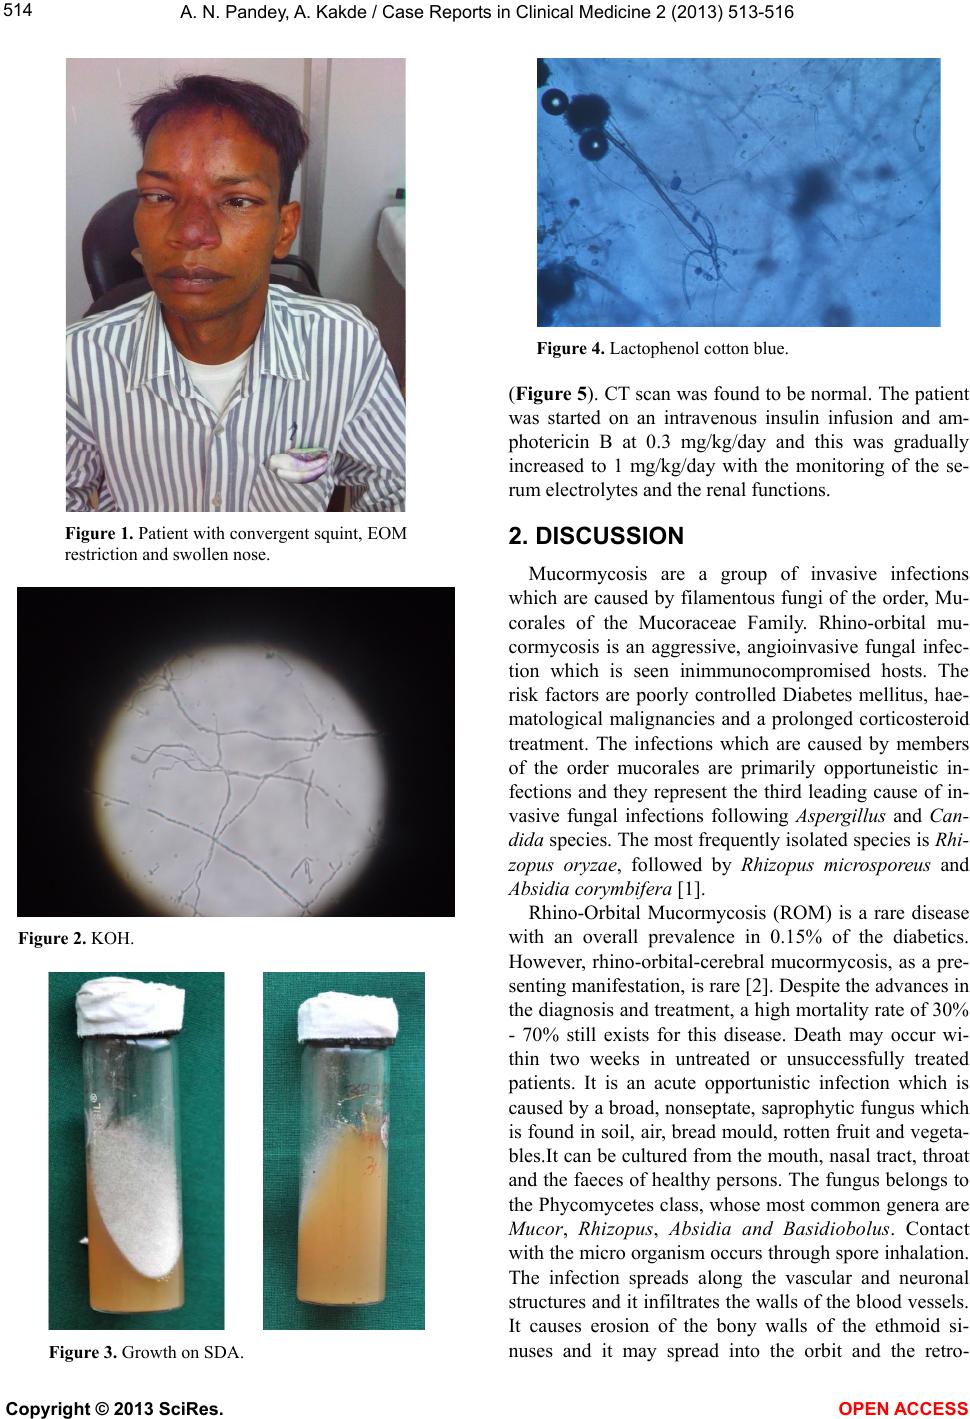 A. N. Pandey, A. Kakde / Case Reports in Clinical M edicine 2 (2013) 513-516 514 Figure 1. Patient with convergent squint, EOM restriction and swollen nose. Figure 2. KOH. Figure 3. Growth on SDA. Figure 4. Lactophenol cotton blue. (Figure 5). CT scan was found to be normal. The patient was started on an intravenous insulin infusion and am- photericin B at 0.3 mg/kg/day and this was gradually increased to 1 mg/kg/day with the monitoring of the se- rum electrolytes and the renal functions. 2. DISCUSSION Mucormycosis are a group of invasive infections which are caused by filamentous fungi of the order, Mu- corales of the Mucoraceae Family. Rhino-orbital mu- cormycosis is an aggressive, angioinvasive fungal infec- tion which is seen inimmunocompromised hosts. The risk factors are poorly controlled Diabetes mellitus, hae- matological malignancies and a prolonged corticosteroid treatment. The infections which are caused by members of the order mucorales are primarily opportuneistic in- fections and they represent the third leading cause of in- vasive fungal infections following Aspergillus and Can- dida species. The most frequently isolated species is Rhi- zopus oryzae, followed by Rhizopus microsporeus and Absidia corymbifera [1] . Rhino-Orbital Mucormycosis (ROM) is a rare disease with an overall prevalence in 0.15% of the diabetics. However, rhino-orbital-cerebral mucormycosis, as a pre- senting manifestation, is rare [2]. Despite the advances in the diagnosis and treatment, a high mortality rate of 30 % - 70% still exists for this disease. Death may occur wi- thin two weeks in untreated or unsuccessfully treated patients. It is an acute opportunistic infection which is caused by a broad, nonseptate, saprophytic fungus which is found in soil, air, bread mould, rotten fruit and vegeta- bles.It can be cultured from the mouth, nasal tract, throat and the faeces of healthy persons. The fungus belongs to the Phycomycetes class, whose most common genera are Mucor, Rh izopus, Absidi a and Basid iobolus. Contact with the micro organism occurs through spore inhalation. The infection spreads along the vascular and neuronal structures and it infiltrates the walls of the blood vessels. It causes erosion of the bony walls of the ethmoid si- nuses and it may spread into the orbit and the retro- Copyright © 2013 SciRes. OPEN A CCESS 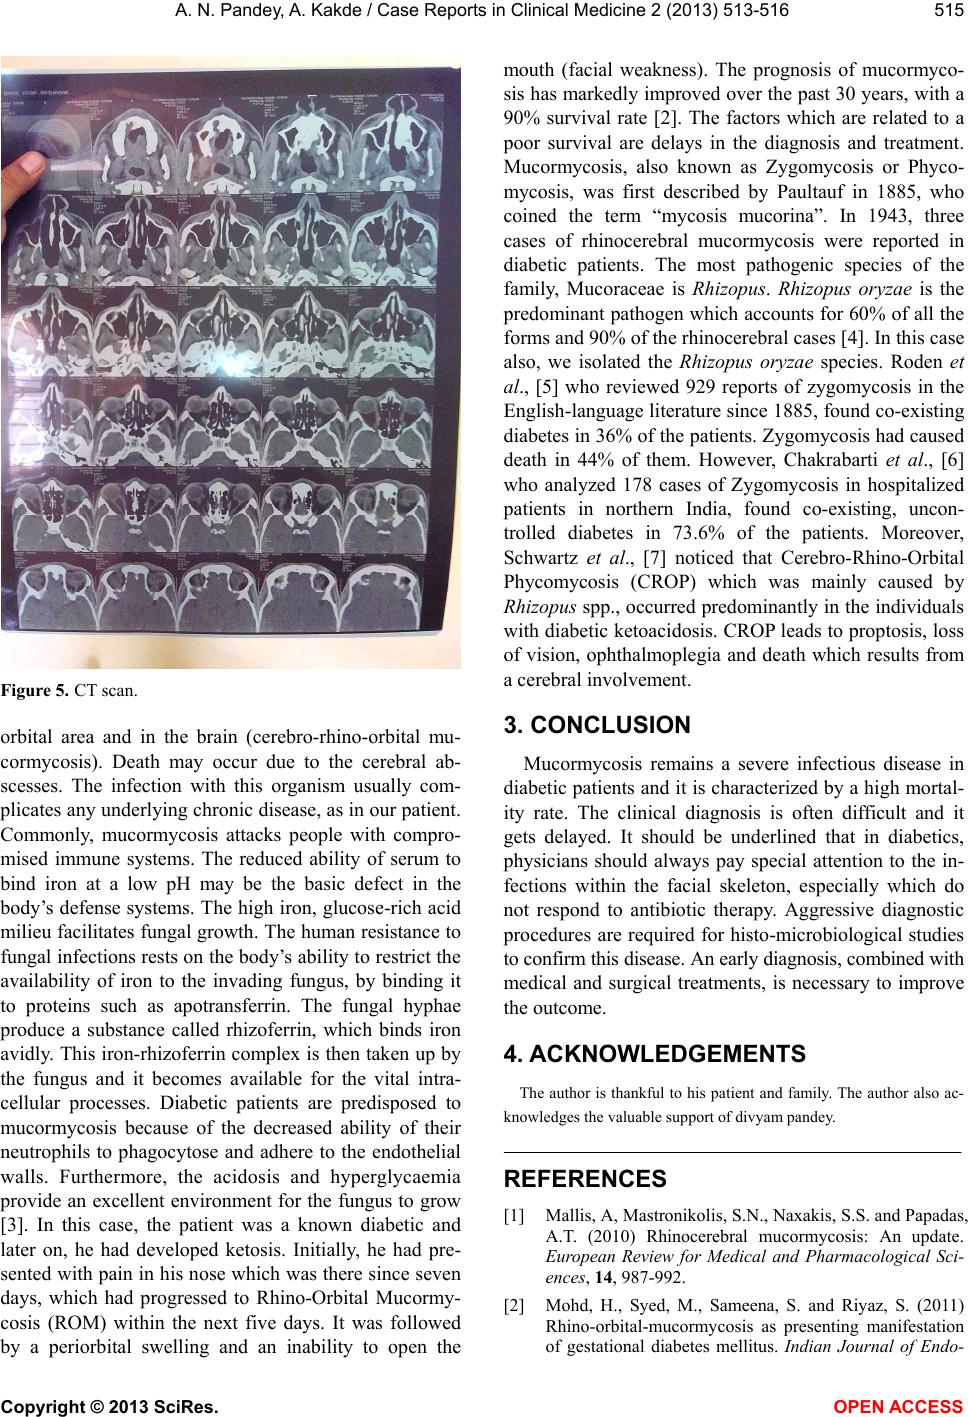 A. N. Pandey, A. Kakde / Case Reports in Clinical M edicine 2 (2013) 513-516 515 Figure 5. CT scan. orbital area and in the brain (cerebro-rhino-orbital mu- cormycosis). Death may occur due to the cerebral ab- scesses. The infection with this organism usually com- plicates any underlying chronic disease, as in our patient. Commonly, mucormycosis attacks people with compro- mised immune systems. The reduced ability of serum to bind iron at a low pH may be the basic defect in the body’s defense systems. The high iron, glucose-rich acid milieu facilitates fungal growth. Th e human resistance to fungal infections rests on the body’s ability to restrict the availability of iron to the invading fungus, by binding it to proteins such as apotransferrin. The fungal hyphae produce a substance called rhizoferrin, which binds iron avidly. This iron-rhizoferrin complex is then tak en up by the fungus and it becomes available for the vital intra- cellular processes. Diabetic patients are predisposed to mucormycosis because of the decreased ability of their neutrophils to phagocytose and adhere to the endothelial walls. Furthermore, the acidosis and hyperglycaemia provide an excellent environment for the fungus to grow [3]. In this case, the patient was a known diabetic and later on, he had developed ketosis. Initially, he had pre- sented with pain in his nose which was there since seven days, which had progressed to Rhino-Orbital Mucormy- cosis (ROM) within the next five days. It was followed by a periorbital swelling and an inability to open the mouth (facial weakness). The prognosis of mucormyco- sis has markedly improved over the past 30 years, with a 90% survival rate [2]. The factors which are related to a poor survival are delays in the diagnosis and treatment. Mucormycosis, also known as Zygomycosis or Phyco- mycosis, was first described by Paultauf in 1885, who coined the term “mycosis mucorina”. In 1943, three cases of rhinocerebral mucormycosis were reported in diabetic patients. The most pathogenic species of the family, Mucoraceae is Rhizopus. Rhizopus oryzae is the predominant path ogen which accounts for 60% of all the forms and 90% of the rhinocerebral cases [4]. In this case also, we isolated the Rhizopus oryzae species. Roden et al., [5] who reviewed 929 reports of zygomycosis in the English-language literatu re since 1885, found co-ex isting diabetes in 36% of the patien ts. Zygomycosis had caused death in 44% of them. However, Chakrabarti et al., [6] who analyzed 178 cases of Zygomycosis in hospitalized patients in northern India, found co-existing, uncon- trolled diabetes in 73.6% of the patients. Moreover, Schwartz et al., [7] noticed that Cerebro-Rhino-Orbital Phycomycosis (CROP) which was mainly caused by Rhizopus spp., occurred predominantly in the individuals with diabetic ketoacidosis. CROP leads to proptosis, loss of vision, ophthalmoplegia and death which results from a cerebral involvement. 3. CONCLUSION Mucormycosis remains a severe infectious disease in diabetic patients and it is characterized by a high mortal- ity rate. The clinical diagnosis is often difficult and it gets delayed. It should be underlined that in diabetics, physicians should always pay special attention to the in- fections within the facial skeleton, especially which do not respond to antibiotic therapy. Aggressive diagnostic procedures are required for histo-microbiological studies to confirm this disease. An early diagnosis, combined with medical and surgical treatments, is necessary to improve the outcome. 4. ACKNOWLEDGEMENTS The author is thankful to his patient and family. The author also ac- knowledges the valuable support of di vyam pandey. REFERENCES [1] Mallis, A, Mastronikolis, S.N., Naxakis, S.S. and Papadas, A.T. (2010) Rhinocerebral mucormycosis: An update. European Review for Medical and Pharmacological Sci- ences, 14, 987-992. [2] Mohd, H., Syed, M., Sameena, S. and Riyaz, S. (2011) Rhino-orbital-mucormycosis as presenting manifestation of gestational diabetes mellitus. Indian Journal of Endo- Copyright © 2013 SciRes. OPEN A CCESS  A. N. Pandey, A. Kakde / Case Reports in Clinical M edicine 2 (2013) 513-516 Copyright © 2013 SciRes. OPEN A CCESS 516 crinology and Metabolism, 15, 65-66. [3] Mathebula, S.D. (2006) Case report: Rhino-orbital mu- cormycosis. The South African op tomet rist , 65, 78-81. [4] Lamia, A., Badreddine, K., Hanene, T., Kanoun, F., Gou- bontini, A., Mnif, E., Zouiten, F., Chaker, E. and Chaa- bane, T. B. (2008) Mucormycose: A propos de quatre ob- servations. La Tunisie Medicale, 86, 165-168. [5] Roden, M.M., Zaoutis, T.E., Buchanan, W.E., et al. (2005) Epidemiology and outcome of zygomycosis: A review of 929 reported cases. Clinical Infectious Diseases, 41, 634- 653. http://dx.doi.org/10.1086/432579 [6] Chakrabarti, A., Das, A., Ma ndal, J., et al. (2006) The ri- sing trend of invasive Zygomycosis in patient with un- controlled diabetes mellitus. Medical Mycology, 44, 335- 342. http://dx.doi.org/10.1080/13693780500464930 [7] Schwart, J.N., Donnelly, E.H. and Kintworth, G.K. (1977) Ocular and orbital phycomycosis. Survey of Ophthal- mology, 22, 3-28. http://dx.doi.org/10.1016/0039-6257(77)90025-X |