

Paper Menu >>
Journal Menu >>
 Engineering, 2013, 5, 347-351 http://dx.doi.org/10.4236/eng.2013.510B070 Published Online Octob er 2013 (http://www.scirp.org/journal/eng) Copyright © 2013 SciRes. ENG Simulation of the Thermal and Mechanical Effects of a Planar Rectangular High Intensity Ultrasound Transducer to Be Used for Destroying Atherosclerotic Plaque Christakis Damianou1,2, C. Christofi2, N. Mylonas3 1Cyprus University of Technology, Limassol, Cyprus 2MEDSONIC, LTD, Limassol , C ypru s 3Frederick University Cyprus, Limassol, Cyprus Email: [email protected] Received June 2013 ABSTRACT The aim of this study is to pe rform a simulation study of the thermal and mechanical effects of a flat rectangular (3 × 10 mm2), MRI compatible transducer operating at 5 MHz for the purpose of destroying atherosclerotic plaque. The simula- tion study focuses on measuring the plaque destruction (due to the thermal of mechanical mode of ultrasound) as a function of power, time, frequency, duty factor and pulse duration. The main goal is to keep the artery temperature at a safe level. T he simulation st udy shows that with the therma l mode the te mperature in the artery cannot be kept at a safe level. Keywords: Ultrasound; Atheroscle r o tic ; Plaque; MRI 1. Introduction Atherosclerosis also known as arteriosclerotic vascular disea se (ASVD) is a condition in which fatty material collects along the walls of arteries. This fatty material thickens, hardens (forms calcium deposits), and may eventually block the arteries [1]. Calcium is a critical component of atherosclerotic plaque. The absence of calcification is strong evidence against the presence of active disease even with significant luminal stenosis. Calcification is reversible and may contribute to the for- mation of an atheroma by adding the byproducts of re- sorption to the necrotic core. The sequence of events in plaque development following injury is inflammation, followed by calcification of the damaged tissue, ending ultimately in the formation of a necrotic core [2-4]. Lifestyle changes, such as follo wing a healthy diet and exercising, are often the best treatment for atherosclero- sis. But sometimes, medication or surgical procedures may be recommended as well [5]. Over the years, re- searchers have been involved in Clinical research to de- velop medication treatments and approaches in order to reduce the risk of heart attack and other medical prob- lems caused by atherosclerosis (for example Angiotensin II receptor blockers (ARBs) [5], Angiotensin-converting enzyme (ACE)[6], Cholesterol Medications[7], Diuret- ics[8]). In advanced cases, atherosclerosis treatment may re- quire special surgical procedures such as Balloon An- gioplasty [9-12], Balloon Angioplasty and Stenting [13-15], Cutting Balloon [16 -21], Atherectomy [22,23], Surgical Bypass [24,25] and Endarterectomy [26,27] to open an artery and improve blood flow. Another treatment option could be the application of mechanical waves such as ultrasound. With ultrasound either the thermal or mechanical properties can be uti- lized. Our group uses MRI to monitor ultrasonic proto- cols and therefore, the ultrasonic transducer has to be MRI compatible. In this paper a simulation study of the thermal and mechanical effects of flat rectangular (3 × 10 mm2), MRI compatible ultrasonic transducer operating at 5 MHz for destroying atherosclerotic plaque is included. The simulation study focuses on measuring the plaque destruction (thermal of mechanical) as a function of power, time, frequency, duty factor and pulse duration. The main goal is to keep the artery temperature at a safe level. This paper includes the design of the MRI com- patible transducer. 2. Materials and Methods 2.1. Simulation Model The power field was estimated using the KZK model [28]. The temperature vs. time history was obtained by 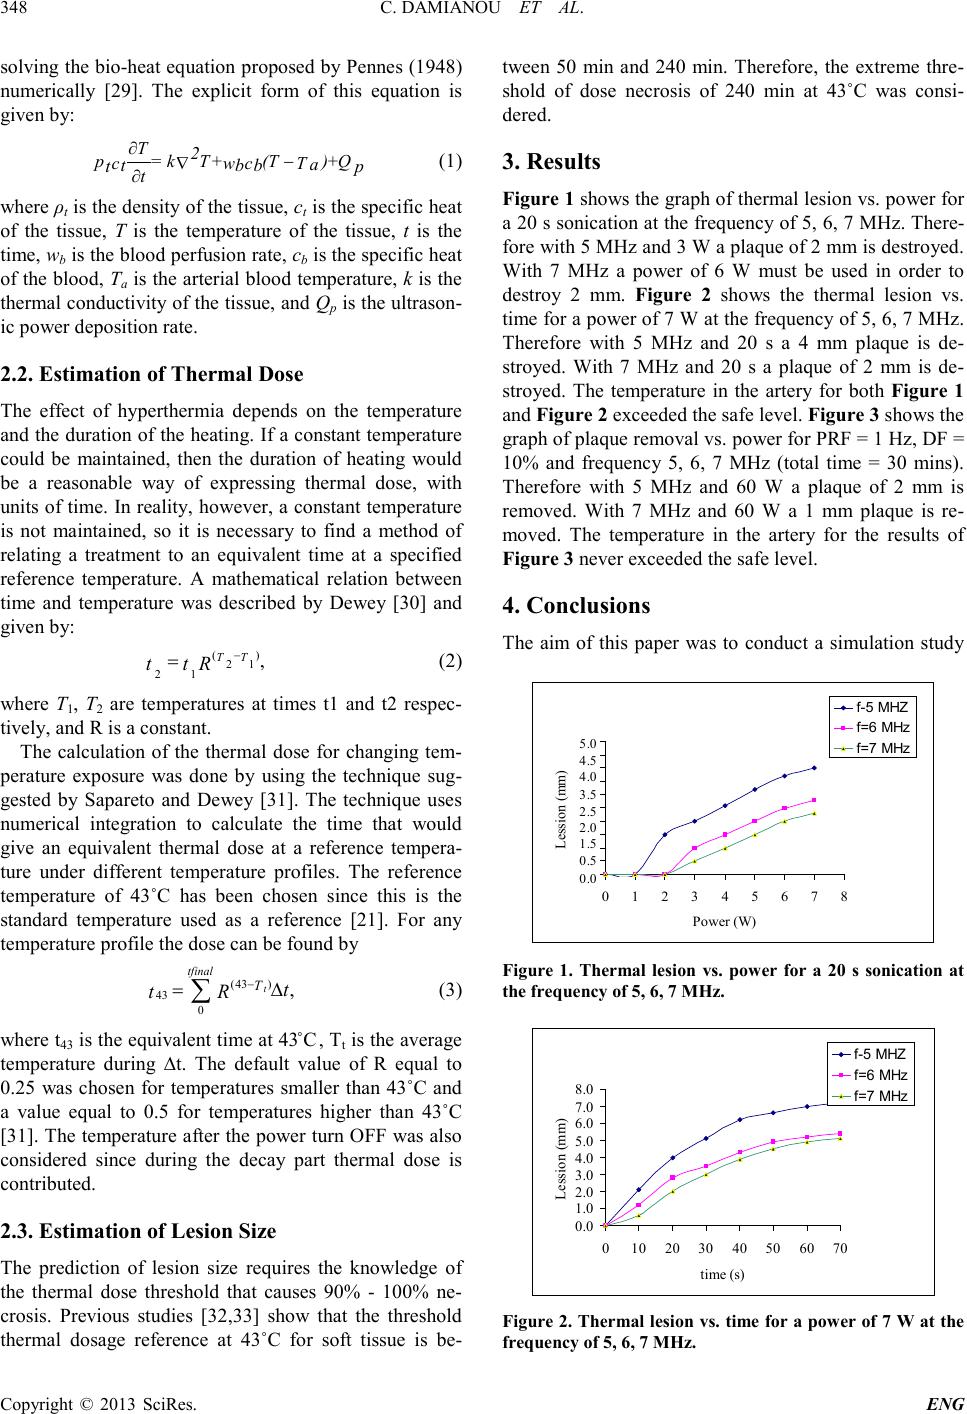 C. DAMIANOU ET AL. Copyright © 2013 SciRes. ENG 348 solvi ng t he bio-heat equation proposed by Pennes (1948) numerically [29]. The explicit form of this equation is given by: T2 = kT+(T)+ pQ cwc Ta t bb tp t ∂− ∇ ∂ (1) where ρt i s t he de nsit y of the ti ssue, ct is the specific heat of the tissue, T is the temperature of the tissue, t is the time, wb is the blood perfusion rate, cb is the specific heat of the blood, Ta is the arterial blood temperature, k is the ther mal co nducti vity of t he tissue , and Qp is the ultrason- ic power deposition rate. 2.2. Estimation of Thermal Dose The effect of hyperthermia depends on the temperature and the duration of the heating. If a constant temperature could be maintained, then the duration of heating would be a reasonable way of expressing thermal dose, with units o f time. In reali ty, ho wever, a constant temperature is not maintained, so it is necessary to find a method of relating a treatment to an equivalent time at a specified reference temperature. A mathematical relation between time and temperature was described by Dewey [30] and given by: () 21 21 , TT tt R − = (2) where T1, T2 are temperatures at times t1 and t2 respec- tively, and R is a constant. The calculation of the thermal dose for changing tem- perature exposure was done by using the technique sug- gested by Sapareto and Dewey [31]. The technique uses numerical integration to calculate the time that would give an equivalent thermal dose at a reference tempera- ture under different temperature profiles. The reference temperature of 43˚C has been chosen since this is the standard temperature used as a reference [21]. For any temperature profile the dose can be found by (43 ) 43 0 , t tfinal T t tR − = ∆ ∑ (3) where t43 is the eq uivale nt time at 4 3˚C, Tt is the average temperature during ∆t. The default value of R equal to 0.25 was chosen for temperatures smaller than 43˚C and a value equal to 0.5 for temperatures higher than 43˚C [31]. The temperature after the power turn OFF was also considered since during the decay part thermal dose is contributed. 2.3. Estimation of Lesion Size The prediction of lesion size requires the knowledge of the thermal dose threshold that causes 90% - 100% ne- crosis. Previous studies [32,33] show that the threshold thermal dosage reference at 43˚C for soft tissue is be- tween 50 min and 240 min. Therefore, the extreme thre- shold of dose necrosis of 240 min at 43˚C was consi- dered. 3. Resul ts Figure 1 sho ws the grap h of t her mal lesi on vs . power for a 20 s sonication at the frequency of 5, 6, 7 MHz. There- fore with 5 MHz and 3 W a plaque of 2 mm is destr o ye d. With 7 MHz a power of 6 W must be used in order to destroy 2 mm. Figure 2 shows the thermal lesion vs. time for a power of 7 W at the frequency of 5, 6, 7 MHz. Therefore with 5 MHz and 20 s a 4 mm plaque is de- stroyed. With 7 MHz and 20 s a plaque of 2 mm is de- st r oye d . The temperature in the artery for both Figure 1 and Figure 2 exceeded the safe level. Figure 3 sho ws the graph of plaque removal vs. power for PRF = 1 Hz, DF = 10% and frequency 5, 6, 7 MHz (total time = 30 mins). Therefore with 5 MHz and 60 W a plaque of 2 mm is removed. With 7 MHz and 60 W a 1 mm plaque is re- mo v e d . The temperature in the artery for the results of Figure 3 never exceeded the safe level. 4. Conclusions The aim of this paper was to conduct a simulation study Figure 1. Thermal lesion vs. power for a 20 s sonication at the frequency of 5, 6 , 7 MHz. Figure 2. Thermal lesion vs. time f or a pow er of 7 W at the frequency of 5, 6, 7 M Hz. 0 ,0 0 ,5 1 ,0 1 ,5 2 ,0 2 ,5 3 ,0 3 ,5 4 ,0 4 ,5 5 ,0 012345678 Power (W) Lession (mm) f-5 MHZ f=6 MHz f=7 MHz 5.0 4.5 4.0 3.5 2.5 2.0 1.5 0.5 0.0 0 .0 1 .0 2 .0 3 .0 4 .0 5 .0 6 .0 7 .0 8 .0 010 20 3040 50 60 70 time (s) Lession (mm) f-5 MHZ f=6 MHz f=7 MHz  C. DAMIANOU ET AL. Copyright © 2013 SciRes. ENG 349 Figure 3. Plaque removal vs. power for PRF = 1 Hz, DF = 10% and frequency 5, 6, 7 MHz (total time = 30 min). of the thermal and mechanical effects of a flat rectangu- lar (3 × 10 mm2) MRI compatible transducer operating at 5 MHz for destroying atherosclerotic plaque. The main goal was to keep the artery temperature at a safe level. The simulation study shows that with the thermal mode the temperature in the artery cannot be kept at a safe level. Using mechanical mode ultrasound yields no se- vere temperature elevation in the arteries. This paper provides useful information regarding the size of the plaque removal as power, time, frequency, duty factor and pulse duration. 5. Acknowledgemen ts This work was supported by the Research Promotion Foundation of Cyprus and the European regional devel- opment structural funds (project number ΕΠΙΧΕΙΡΗΣΕΙΣ/ ΠΡΟΪΟΝ/0311/01). REFERENCES [1] L. Wagenknecht, B. Wasserman, L. Chambless, J. Coresh, A. Folsom, T. Mosley, C. Ballantyne , R. Sh arrett and E. Boerwinkl e, “Correlates of Carotid Plaque Presence and Composition as Measured by Magnetic Resonance Imag- ing: The Atherosclerosis Risk in Communities (Aric) Stud y Wagenknecht , Risk Fact or s & Mri Measu red Car o- tid Plaqu e,” Circulation: Cardiovascular Imaging, Vol. 2, No. 4, 2009, pp. 314-322. http://dx.doi.org/10.1161/CIRCIMAGING.108.823922 [2] L. Wexler, B. Brundage, J. Crouse, R. Detrano, V. Fuster, J. Maddahi, J. Rumberger, W. Stanford, R. White and K. Taubert, “Coronary Artery Calcification: Pathophysiolo- gy, Epidemiology, Imaging Methods, and Clinical Impli- cations,” Circulation, V ol. 94, 1996, pp. 1175-1192. http://dx.doi.org/10.1161/01.CIR.94.5.1175 [3] T. J. Romer, J. F. Brennan, M. Fitzmaurice, M. L. Feld- stein, G. Deinu m, J. L. Myles, J. R. Myles, J. R. Kramer, R. S. Lees and M. S. Feld, “A Rotational Ablation Tool for Calci fied Athero sclerot ic P laque Removal Biomedical Micro devices,” Circulation, Vol. 97, 1998, p. 8. [4] M. Naghavi, P. Libby, E. Falk, S. W. Casscells, S. Li- tovsky and J. Rumberger, “From Vulnerable Plaque to Vulnerable Patient: A Call for New Definitions and Risk Assessment Strategies: Part I,” Circulation, Vol. 108, 2003, pp. 1664-1672. http://dx.doi.org/10.1161/01.CIR.0000087480.94275.97 [5] Y. Nishida, Y. Takahashi, T. Nakayama and S. Asai, “Comparative Effect of Angiotensin II Type I Receptor Blockers and Calcium Channel Blockers on Laboratory Parameters in Hypertensive Patients with Type 2 Di- abetes,” Cardiovascular Diabetology, Vol. 11, No. 3, 2012, p. 53. http://dx.doi.org/10.1186/1475-2840-11-53 [6] H. Q. Li, Y. Li, C. Wang, T. Sun, Z. M. Sun, J. Zhou, L. Ba and Z. Z. Huang, “Study on the Association of Oral Contraceptives, Angiotensin-Converting Enzyme Gene Polymorphisms and Risk of Stroke in Women,” Zhong- hua Liu Xing Bing Xue Za Zhi, Vol. 33, No. 1, 2012, pp. 23-27. [7] H. R. Superko, K. M. M o mary and Y. Li, “Statins Perso- nalized,” Medical Clinics of North America, Vol. 96, No. 1, 2012, pp. 123-139. http://dx.doi.org/10.1016/j.mcna.2011.11.004 [8] Y. Matsui, M. F. O’Rourke, S. Hoshide, J. Ishikawa, K. Shimada and K. Kario, “Combined Effect of Angiotensin II Receptor Blocker and Either a Calcium Channel Blocker or Diuretic on Day-by-Day Variability of Home Blood Pressure: The Japan Combined Treatment With Olmesartan and a Calcium-Channel Blocker Versus Ol- mesartan and Diuretics Randomized Efficacy Study,” Hypertension, Vol. 59, N o. 6, 2012, pp. 1132-1138. http://dx.doi.org/10.1161/HYPERTENSIONAHA.111.18 9217 [9] B. Mc Cu tcheon, D. Weatherford, G. Maxwell, et al., “A Preliminary Investigation of Balloon Angioplasty Versus Surgical Treatment of Thrombosed Dialysis Grafts,” The American Journal of Surgery, Vol. 69, 2003, pp. 663-667. [10] J. Ziv. Haskal, S. Treroto la, B. Dolmatch, E. Schuman, S. Alt man, S. Mietling, S. Berman, G. McLennan, C. Tri m- mer, J. Ross and T. Vesely, “M.D. Stent Graft versus Balloon Angioplasty for Failing Dialysis-Access Grafts N,” The New England Journal of Medicine, Vol. 362, 2010, pp. 494-503. [11] S. Rafajlovski, V. Orozović, A. Ristić-Andelkov and G. Raden, “Percutaneous Transluminal Coronary Angiop- lasty in the Right Ventricle Myocardial Infarction Treat- ment,” Vojnosanit Pregl, Vol. 62, No. 10, 2005, pp. 731- 738. http://dx.doi.org/10.2298/VSP0510731R [12] M. D. Dake, G. M. Ansel, M. R. Jaff, T. Ohki, R. R. Sa- xon, H. B. Smouse, T. Zeller, G. S. Roubin, M. W. Bur- ket, Y. Khatib, S. A. Snyder, A. O. Ragheb, J. K. White and L. S. Machan, “Paclitaxel -Elu ting Stents Show Supe- riority to Balloon Angioplasty and Bare Metal Stents in Femoropopliteal Disease: Twelve-Month Zilver PTX Randomized Study Results,” Circulation: Cardiovascular Interventions, 2011. [13] C. J. Boyle, A. B. Lennon and P. J. Prendergast, “In silico prediction of the mechanobiological response of arterial tissue: application to angioplasty and stenting,” Journal of Biomechanical Engineering, Vol. 133, No. 8, 2011. http://dx.doi.org/10.1115/1.4004492 0 ,0 1 ,0 2 ,0 3 ,0 4 ,0 020 4060 80100 Power (W) Plaque removal(mm) f-5 MHZ f=6 MHz f=7 MHz 4.0 3.0 2.0 1.0 0.0  C. DAMIANOU ET AL. Copyright © 2013 SciRes. ENG 350 [14] T. Abu-Tair, C. Martin and C. Kamp ma n n , “Acute Aortic Dissection after Balloon Angioplasty of a Recoarctation and Treatment by Stenting and Distal Membrane Fene- stration in a Child ,” Heart, Vol. 97, No. 20, 2011, pp. 1699-1700. http://dx.doi.org/10.1136/heartjnl-2011-300709 [15] H. Takebayashi, S. Haruta, H. Kohno, et al., “Immediate and 3-Month Follow-Up Outcome after Cutting balLoon Angioplasty for Bifurcation Lesions,” Journal of Inter- ventional Cardiology, Vol. 17, 2004, pp. 1-7. http://dx.doi.org/10.1111/j.1540-8183.2004.00246.x [16] L. J. Bergers en, S. B. Perry and J. E. Lock, “Effect of Cutting Balloon Angioplasty on Resistant Pulmonary Ar- te ry S tenosis,” Ameri can Journal of Cardiology, Vol. 15, 2003, pp. 185-189. http://dx.doi.org/10.1016/S0002-9149(02)03107-7 [17] J. F. Rhodes, G. K. Lane and C. I. Mesia, “Cutting Bal- loon Angioplasty for Children with Small-Vessel Pulmo- nary Artery Stenoses,” Circulation: Cardiovascular In- terventions, Vol. 55, 2002, pp. 73-77. http://dx.doi.org/10.1002/ccd.10031 [18] G. M. Ansel, N. S. Sample, C. F. Bo tti III Jr, et al ., “Cut- ting Balloon Angioplasty of the Popliteal and Infrapopli- teal Vessels for Symptomatic Limb Isc h e mi a ,” Circula- tion: Cardiovascular Interventions, Vol. 61, 2004, pp. 1-4. http://dx.doi.org/10.1002/ccd.10731 [19] C. Engelke, C. Sandhu, R. A. Morgan, et al., “Using 6-mm Cutting Balloon Angioplasty in Patients with Re- sistant Peripheral Artery Stenosis: Preliminary Results,” AJR, Vol. 179, 2002, pp. 619-623. http://dx.doi.org/10.2214/ajr.179.3.1790619 [20] K. Kasirajan and P. A. Schneider, “Early Outcome of “Cutting” Balloon Angioplasty For Infrainguinal Vein Graft Stenosis,” Journal of Vascular Surgery, Vol. 39, 2004, pp. 702-708. http://dx.doi.org/10.1016/j.jvs.2003.10.046 [21] R. D. Safian, C. L. Gri n e s, M. A. M ay, A. Licht enber g, N. Juran, T. L. Schreiber, G. Pavlides, T. B. Meany, V. Sa- vas and W. W. O’Neill, “Clinical and Angiographic Re- sults of Transluminal Extraction Coronary Atherectomy in Saphenous Vein Bypass Grafts,” Circulation, Vol. 89, 1994, pp . 302-312. http://dx.doi.org/10.1161/01.CIR.89.1.302 [22] F. Mangiacapra, G. R. Heyndrickx, E. Puymirat, A. J. Peace, W. Wijns, B. De Bruyne and E. Bar bato, “Com- parison of drug-Eluting Versus Bare-Metal Stents after Rotational Atherectomy for the Treatment of Calcified Coronary Lesions,” International Journal of Cardiology, Vol. 153, No. 3, 2012, pp. 373-376. http://dx.doi.org/10.1016/j.ijcard.2011.11.048 [23] S. K. Forouzannia, M. H. Abdollahi, S. J. Mirhosseini, H. Hosseini, S. H. Moshtaghion, A. Golzar, N. Naserzadeh, S. M. Ghoraishian and T. Emami Meybodi, “Clinical Outcome and Cost in Patients with Off-Pump vs. On- Pump Coronary Artery Bypass Surgery,” Acta Medica Iranica, Vol. 49, No. 7, 2011, pp. 414-419. [24] E. J. Lee, K. H. Choi, J. S. Ryu, S. B. Jeon, S. W. Lee, S. W. Park, S. J. Park, J. W. Lee, S. J. Choo, C. H. Chung, S. H. Jung, D. W. Kang, J. S. Kim and S. U. Kwon, “Stroke Risk after Coronary Artery Bypass Graft Surgery and Extent of Cerebral Artery Atherosclerosis,” American College of Cardiology Foundation, Vol. 57, No. 18, 2011, pp. 1811-1818. http://dx.doi.org/10.1016/j.jacc.2010.12.026 [25] J. T. McGinn Jr, M. A. Shariff, T. M. Bhat, B. Azab, W. J. Molloy, E. Quat trocchi, M. Farid, A. M. Eichorn, Y. D. Dlugacz and R. A. Silverman , “Prevalence of Dysglyce- mia among Coronary Artery Bypass Surgery Patients with No Previous Diabetic History,” Journal of Cardio- thoraci c Surgery, Vol. 6, 2011, p. 104. http://dx.doi.org/10.1186/1749-8090-6-104 [26] A. Redzek, B. Mihajlović, P. Kovacević, N. C. Adić, K. Pavlović, L. Vel icki, “Patency of internal thoracic artery and vein grafts according to revascularized coronary ar- tery properties,” Med Pregl., Vol. 64, No. 3-4, 2011, pp. 137-142. http://dx.doi.org/10.2298/MPNS1104137R [27] A. Siani, F. Accrocca, L. M. Siani, R. Gabrielli, R. Anto- nelli, G. A. Giordano and G. Marcucci, “Prosthetic Caro- tid Bypass Graft for In-Stent Restenosis Performed for Post-Endarterectomy Recurrent Stenosis: Technical De- tails,” Giornale di Chirurgia, Vol. 33, No. 3, 2012, pp. 95-97. [28] R. J. McDonald, H. J. Cloft and D. F. Kallmes, “Intracra- nial Hemorrhage is Much More Common after Carotid Stenting than after Endart erectomy: Evidence from the National Inpatient Sample,” Stroke, Vol. 42, No. 10, 2011, pp. 2782-7278. http://dx.doi.org/10.1161/STROKEAHA.111.618769 [29] J. E. Soneson and M. R. Myers, “Gaussian rep resentati on of High-Intensity Focused Ultrasound Beams,” Journal of the Acou stical So ciety of America, Vol. 122, No. 5, 2007, pp. 2526 -2531. [30] M. Pennes, “Analysis of Tissue and Arterial Blood Tem- perature in the Resting Human Forearm,” Journal of Ap- plied Physics, Vol. 1, 1948, pp. 93-122. [31] W. Dewey, L. Hopwood, S. Sap ar eto and L. Gerwecki, “Cellular Responses to Combinations of Hyperthermia and Radiation,” Radiology, Vol. 123, 1977, pp. 463-474. [32] S. Sapareto and W. Dewey, “Thermal Dose Determina- tion in Cancer Therapy,” International Journal of Radia- tion Oncology Biology Physics, Vol. 10, 1984, pp. 787- 800. http://dx.doi.org/10.1016/0360-3016(84)90379-1 [33] W. Jansen and J. Haverman, “Histological Changes in the Skin and Subcutaneous Tissues of Mouse Legs after Treatment with Hyperthermia,” Pathology: Research and Practice, Vol. 186, 1983, pp. 247-253. http://dx.doi.org/10.1016/S0344-0338(11)80542-X |