

Paper Menu >>
Journal Menu >>
 Open Journal of Anesthesiology, 2013, 3, 363-366 http://dx.doi.org/10.4236/ojanes.2013.38077 Published Online October 2013 (http://www.scirp.org/journal/ojanes) 363 Thromboelastographic Profile of Patients with Hyperparathyroidism Secondary to Chronic Kidney Failure Submitted to Total Parathyroidectomy —Case Series Walkíria Wingester Vilas Boas, Cristiano Barbosa de Oliveira, Thadeu Alves Máximo, Carlos Alexandre de Freitas Trindade, Alexandre de Andrade Sousa Developed in Hospital das Clínicas da Universidade Federal de Minas Gerais HC-UFMG, Belo Horizonte, Brazil Email: [email protected] Received July 23rd, 2013; revised August 24th, 2013; accepted September 25th, 2013 Copyright © 2013 Walkíria Wingester Vilas Boas et al. This is an open access article distributed under the Creative Commons At- tribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is prop- erly cited. ABSTRACT Coagulopathy in surgical patients can cause perioperative complications, as both bleeding and thromboembolic events increase surgical morbimortality. The recognition of preexisting disorders and the understanding of the dynamic changes in hemostasis during surgery are prerequisites of safe patient management. The perioperative management of patients with chronic kidney failure is a huge challenge due to both the hypercoagulable state and increased risk of bleeding. Classic laboratory exams performed for the evaluation of blood clotting seem insufficient regarding the de- termination of the risk of bleeding and thrombosis in surgical patients. As patients with chronic kidney failure develop secondary hyperparathyroidism, the aim of the present study was to describe a case series and correlate the periopera- tive thromboelastographic profile of patients with chronic kidney failure submitted to parathyroidectomy with their secondary hyperparathyroidism. Keywords: Thromboelastography; Chronic Renal Failure; Hyperparathyroidism; Total Thyroidectomy 1. Background and Objectives Coagulopathy in surgical patients can cause perioperative complications, as both bleeding and thromboembolic events increase surgical morbimortality [1]. The recogni- tion of preexisting disorders and the understanding of the dynamic changes in hemostasis during surgery are prere- quisites of safe patient management. While patients with chronic kidney failure are tradi- tionally considered to be at risk for perioperative bleed- ing due to the platelet dysfunction related to uremia, anemia and frequent dialysis [2,3], clotting disorders that favor a hypercoagulable state have also been demon- strated in such patients [2,4,5]. Therefore, the periopera- tive management of patients with chronic kidney failure is a huge challenge due to both the hypercoagulable state and increased risk of bleeding. This apparent dichotomy has important implications regarding clinical and anes- thesiological management. A blood product reserve, pe- rioperative thromboprophylaxis and thrombosis preven- tion of the arteriovenous fistula are directly related to knowledge regarding the coagulation profile of patients with chronic kidney failure. Classic laboratory exams performed for the evaluation of blood clotting seem insufficient regarding the deter- mination of the risk of bleeding and thrombosis in surgi- cal patients [6]. Thus, different dynamic coagulation monitors have been tested, including the thromboelasto- graph [6,7]. Thromboelastography allows the analysis of different phases of coagulation, the quality of the throm- bus formed and fibrinolysis through the determination of five main indices on the readout. The R index (reaction time) is equivalent to the blood clotting time and has some correlation with other tests of the initial formation of fibrin. The K value (clot formation time) is the time the formed clot takes to reach a fixed degree of viscoe- lasticity. The alpha angle (α) is an indicator of the clot formation rate. Maximum amplitude (MA) is influenced Copyright © 2013 SciRes. OJAnes 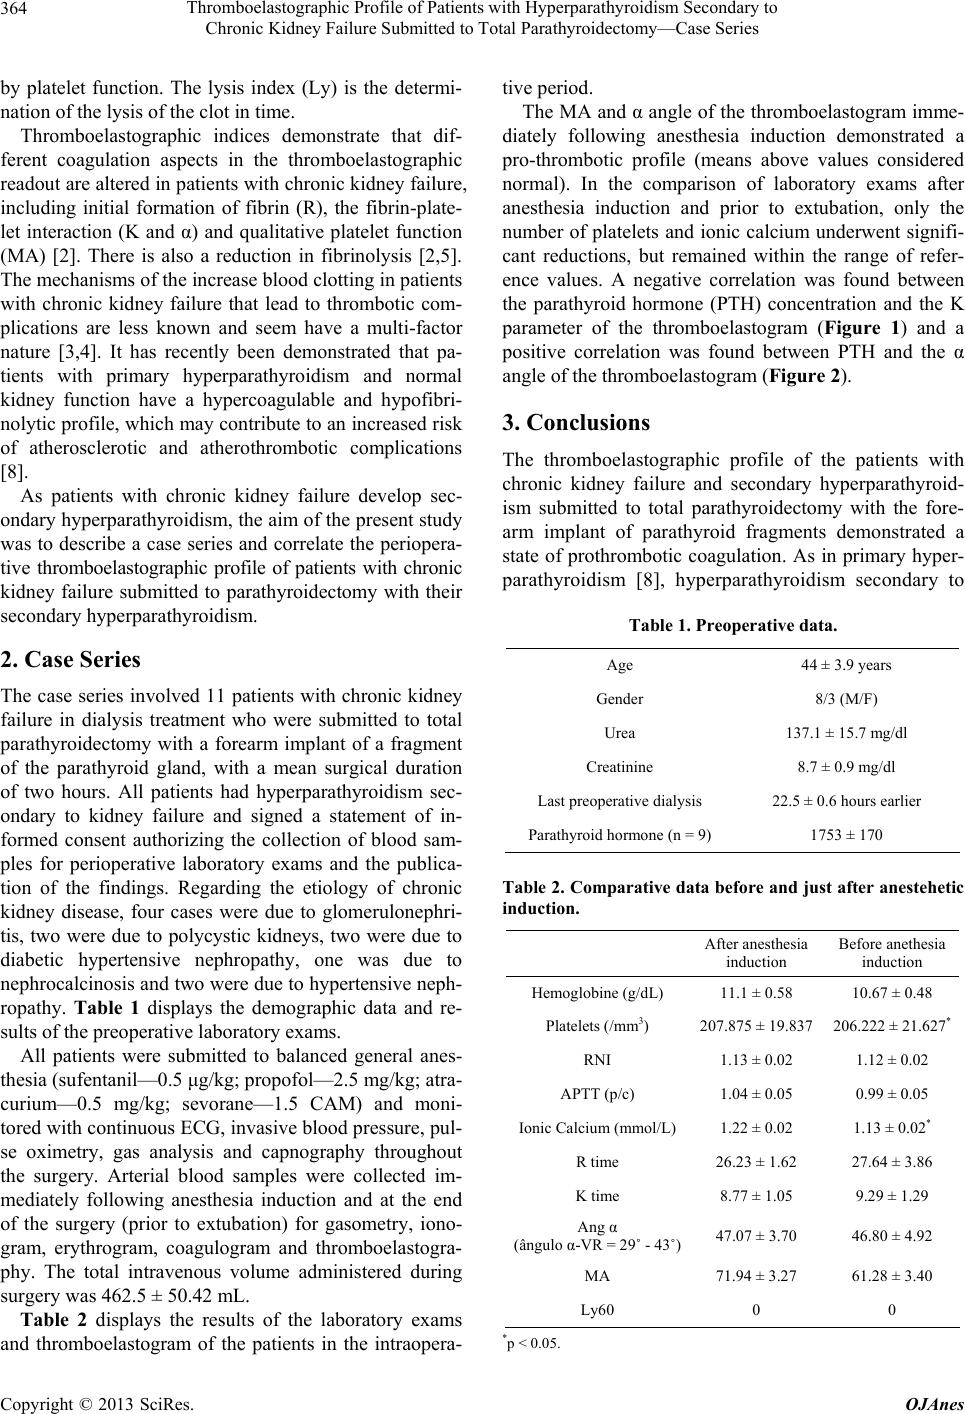 Thromboelastographic Profile of Patients with Hyperparathyroidism Secondary to Chronic Kidney Failure Submitted to Total Parathyroidectomy—Case Series 364 by platelet function. The lysis index (Ly) is the determi- nation of the lysis of the clot in time. Thromboelastographic indices demonstrate that dif- ferent coagulation aspects in the thromboelastographic readout are altered in patients with chronic kidney failure, including initial formation of fibrin (R), the fibrin-plate- let interaction (K and α) and qualitative platelet function (MA) [2]. There is also a reduction in fibrinolysis [2,5]. The mechanisms of the increase blood clotting in patients with chronic kidney failure that lead to thrombotic com- plications are less known and seem have a multi-factor nature [3,4]. It has recently been demonstrated that pa- tients with primary hyperparathyroidism and normal kidney function have a hypercoagulable and hypofibri- nolytic profile, which may contribute to an increased risk of atherosclerotic and atherothrombotic complications [8]. As patients with chronic kidney failure develop sec- ondary hyperparathyroidism, the aim of the present study was to describe a case series and correlate the periopera- tive thromboelastographic profile of patients with chronic kidney failure submitted to parathyroidectomy with their secondary hyperparathyroidism. 2. Case Series The case series involved 11 patients with chronic kidney failure in dialysis treatment who were submitted to total parathyroidectomy with a forearm implant of a fragment of the parathyroid gland, with a mean surgical duration of two hours. All patients had hyperparathyroidism sec- ondary to kidney failure and signed a statement of in- formed consent authorizing the collection of blood sam- ples for perioperative laboratory exams and the publica- tion of the findings. Regarding the etiology of chronic kidney disease, four cases were due to glomerulonephri- tis, two were due to polycystic kidneys, two were due to diabetic hypertensive nephropathy, one was due to nephrocalcinosis and two were due to hypertensive neph- ropathy. Table 1 displays the demographic data and re- sults of the preoperative laboratory exams. All patients were submitted to balanced general anes- thesia (sufentanil—0.5 μg/kg; propofol—2.5 mg/kg; atra- curium—0.5 mg/kg; sevorane—1.5 CAM) and moni- tored with continuous ECG, invasive blood pressure, pul- se oximetry, gas analysis and capnography throughout the surgery. Arterial blood samples were collected im- mediately following anesthesia induction and at the end of the surgery (prior to extubation) for gasometry, iono- gram, erythrogram, coagulogram and thromboelastogra- phy. The total intravenous volume administered during surgery was 462.5 ± 50.42 mL. Table 2 displays the results of the laboratory exams and thromboelastogram of the patients in the intraopera- tive period. The MA and α angle of the thromboelastogram imme- diately following anesthesia induction demonstrated a pro-thrombotic profile (means above values considered normal). In the comparison of laboratory exams after anesthesia induction and prior to extubation, only the number of platelets and ionic calcium underwent signifi- cant reductions, but remained within the range of refer- ence values. A negative correlation was found between the parathyroid hormone (PTH) concentration and the K parameter of the thromboelastogram (Figure 1) and a positive correlation was found between PTH and the α angle of the thromboelastogram (Figure 2). 3. Conclusions The thromboelastographic profile of the patients with chronic kidney failure and secondary hyperparathyroid- ism submitted to total parathyroidectomy with the fore- arm implant of parathyroid fragments demonstrated a state of prothrombotic coagulation. As in primary hyper- parathyroidism [8], hyperparathyroidism secondary to Table 1. Preoperative data. Age 44 ± 3.9 years Gender 8/3 (M/F) Urea 137.1 ± 15.7 mg/dl Creatinine 8.7 ± 0.9 mg/dl Last preoperative dialysis 22.5 ± 0.6 hours earlier Parathyroid hormone (n = 9) 1753 ± 170 Table 2. Comparative data before and just after anestehetic induction. After anesthesia induction Before anethesia induction Hemoglobine (g/dL) 11.1 ± 0.58 10.67 ± 0.48 Platelets (/mm3) 207.875 ± 19.837 206.222 ± 21.627* RNI 1.13 ± 0.02 1.12 ± 0.02 APTT (p/c) 1.04 ± 0.05 0.99 ± 0.05 Ionic Calcium (mmol/L)1.22 ± 0.02 1.13 ± 0.02* R time 26.23 ± 1.62 27.64 ± 3.86 K time 8.77 ± 1.05 9.29 ± 1.29 Ang α (ângulo α-VR = 29˚ - 43˚)47.07 ± 3.70 46.80 ± 4.92 MA 71.94 ± 3.27 61.28 ± 3.40 Ly60 0 0 *p < 0.05. Copyright © 2013 SciRes. OJAnes 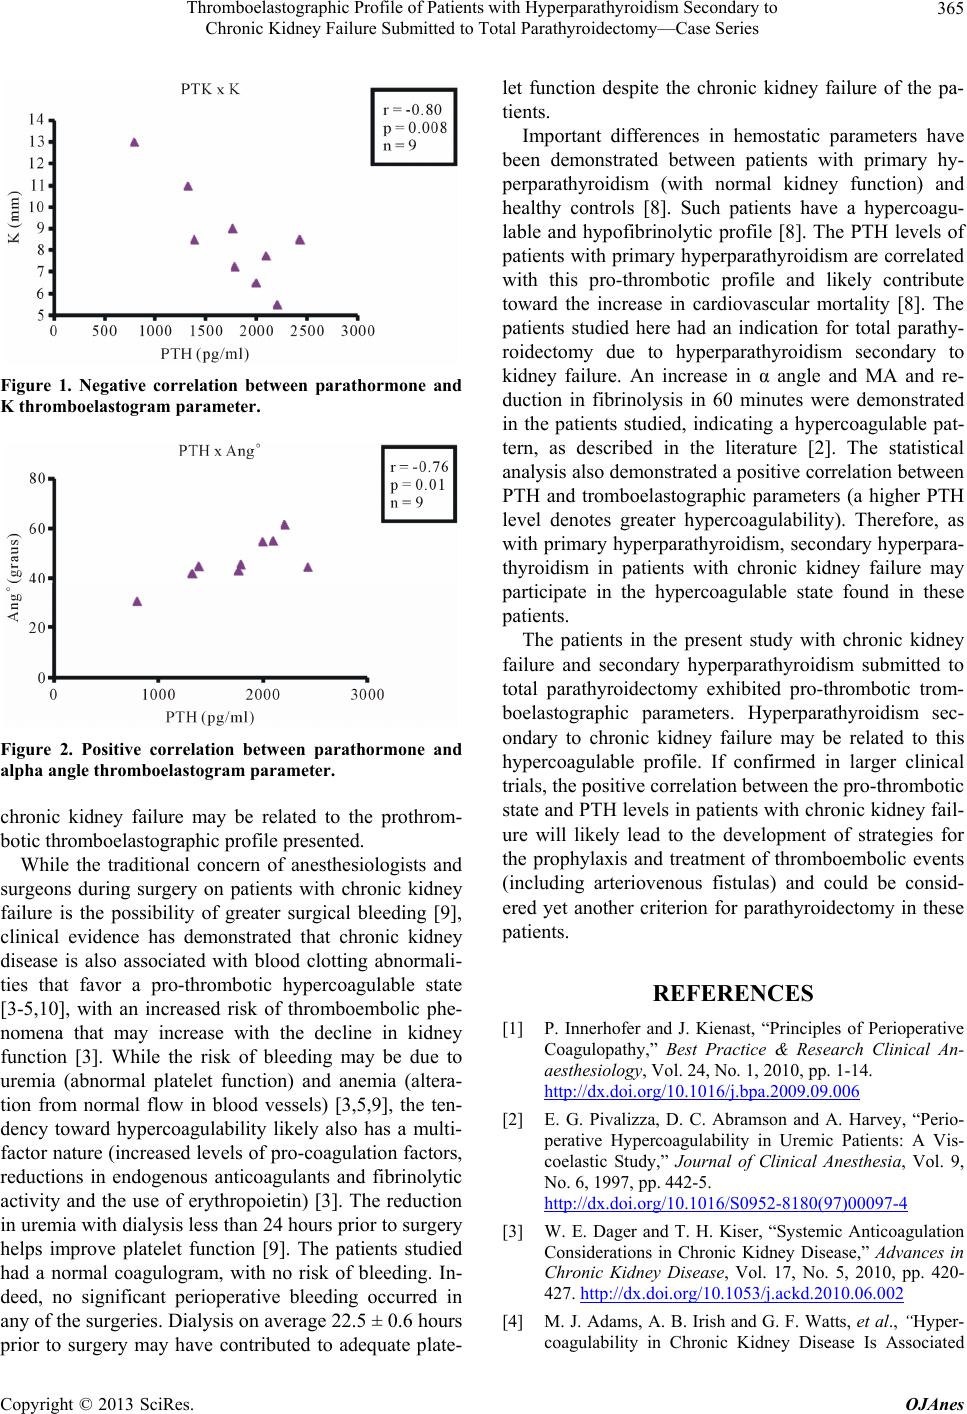 Thromboelastographic Profile of Patients with Hyperparathyroidism Secondary to Chronic Kidney Failure Submitted to Total Parathyroidectomy—Case Series 365 Figure 1. Negative correlation between parathormone and K thromboelastogram parameter. Figure 2. Positive correlation between parathormone and alpha angle thromboelastogram parameter. chronic kidney failure may be related to the prothrom- botic thromboelastographic profile presented. While the traditional concern of anesthesiologists and surgeons during surgery on patients with chronic kidney failure is the possibility of greater surgical bleeding [9], clinical evidence has demonstrated that chronic kidney disease is also associated with blood clotting abnormali- ties that favor a pro-thrombotic hypercoagulable state [3-5,10], with an increased risk of thromboembolic phe- nomena that may increase with the decline in kidney function [3]. While the risk of bleeding may be due to uremia (abnormal platelet function) and anemia (altera- tion from normal flow in blood vessels) [3,5,9], the ten- dency toward hypercoagulability likely also has a multi- factor nature (increased levels of pro-coagulation factors, reductions in endogenous anticoagulants and fibrinolytic activity and the use of erythropoietin) [3]. The reduction in uremia with dialysis less than 24 hours prior to surgery helps improve platelet function [9]. The patients studied had a normal coagulogram, with no risk of bleeding. In- deed, no significant perioperative bleeding occurred in any of the surgeries. Dialysis on average 22.5 ± 0.6 hours prior to surgery may have contributed to adequate plate- let function despite the chronic kidney failure of the pa- tients. Important differences in hemostatic parameters have been demonstrated between patients with primary hy- perparathyroidism (with normal kidney function) and healthy controls [8]. Such patients have a hypercoagu- lable and hypofibrinolytic profile [8]. The PTH levels of patients with primary hyperparathyroidism are correlated with this pro-thrombotic profile and likely contribute toward the increase in cardiovascular mortality [8]. The patients studied here had an indication for total parathy- roidectomy due to hyperparathyroidism secondary to kidney failure. An increase in α angle and MA and re- duction in fibrinolysis in 60 minutes were demonstrated in the patients studied, indicating a hypercoagulable pat- tern, as described in the literature [2]. The statistical analysis also demonstrated a positive correlation between PTH and tromboelastographic parameters (a higher PTH level denotes greater hypercoagulability). Therefore, as with primary hyperparathyroidism, secondary hyperpara- thyroidism in patients with chronic kidney failure may participate in the hypercoagulable state found in these patients. The patients in the present study with chronic kidney failure and secondary hyperparathyroidism submitted to total parathyroidectomy exhibited pro-thrombotic trom- boelastographic parameters. Hyperparathyroidism sec- ondary to chronic kidney failure may be related to this hypercoagulable profile. If confirmed in larger clinical trials, the positive correlation between the pro-thrombotic state and PTH levels in patients with chronic kidney fail- ure will likely lead to the development of strategies for the prophylaxis and treatment of thromboembolic events (including arteriovenous fistulas) and could be consid- ered yet another criterion for parathyroidectomy in these patients. REFERENCES [1] P. Innerhofer and J. Kienast, “Principles of Perioperative Coagulopathy,” Best Practice & Research Clinical An- aesthesiology, Vol. 24, No. 1, 2010, pp. 1-14. http://dx.doi.org/10.1016/j.bpa.2009.09.006 [2] E. G. Pivalizza, D. C. Abramson and A. Harvey, “Perio- perative Hypercoagulability in Uremic Patients: A Vis- coelastic Study,” Journal of Clinical Anesthesia, Vol. 9, No. 6, 1997, pp. 442-5. http://dx.doi.org/10.1016/S0952-8180(97)00097-4 [3] W. E. Dager and T. H. Kiser, “Systemic Anticoagulation Considerations in Chronic Kidney Disease,” Advances in Chronic Kidney Disease, Vol. 17, No. 5, 2010, pp. 420- 427. http://dx.doi.org/10.1053/j.ackd.2010.06.002 [4] M. J. Adams, A. B. Irish and G. F. Watts, et al ., “Hyper- coagulability in Chronic Kidney Disease Is Associated Copyright © 2013 SciRes. OJAnes  Thromboelastographic Profile of Patients with Hyperparathyroidism Secondary to Chronic Kidney Failure Submitted to Total Parathyroidectomy—Case Series Copyright © 2013 SciRes. OJAnes 366 with Coagulation Activation But Not Endothelial Func- tion,” Thrombosis Research, Vol. 123, No. 2, 2008, pp. 374-380. http://dx.doi.org/10.1016/j.thromres.2008.03.024 [5] R. G. Craig and J. M. Hunter, “Recent Developments in the Perioperative Management of Adult Patients with Chronic Kidney Disease,” British Journal of Anaesthesia, Vol. 101, No. 3, 2008, pp. 296-310. http://dx.doi.org/10.1093/bja/aen203 [6] D. Bischof, S. Dalbert, A. Zollinger, et al., “Thrombelas- tography in the Surgical Patient,” Minerva Anestesiolo- gica, Vol. 76, No. 2, 2010, pp. 131-137. [7] J. L. Kashuk, E. E. Moore, A. Sabel, et al., “Rapid Thrombelastography (r-TEG) Identifies Hypercoagula- bility and Predicts Thromboembolic Events in Surgical Patients,” Surgery, Vol. 146, No. 4, 2009, pp. 764-772. http://dx.doi.org/10.1016/j.surg.2009.06.054 [8] C. Erem, M. Kocak, I. Nuhoglu, et al., “Increased Plas- minogen Activator Inhibitor-1, Decreased Tissue Factor Pathway Inhibitor, and Unchanged Thrombin-Activatable Fibrinolysis Inhibitor Levels in Patients with Primary Hyperparathyroidism,” European Journal of Endocri- nology, Vol. 160, No. 5, 2009, pp. 863-868. http://dx.doi.org/10.1530/EJE-09-0069 [9] D. Trainor, E. Borthwick and A. Ferguson, “Perioperative Management of the Hemodialysis Patient,” Seminars in Dialysis, Vol. 24, No. 3, 2011, pp. 314-326. http://dx.doi.org/10.1111/j.1525-139X.2011.00856.x [10] K. Wattanakit, M. Cushman, C. Stehman-Breen, et al., “Chronic Kidney Disease Increases Risk for Venous Thromboembolism,” Journal of the American Society of Nephrology, Vol. 19, No. 1, 2008, pp. 135-140. http://dx.doi.org/10.1681/ASN.2007030308 |