

Paper Menu >>
Journal Menu >>
 Vol.2, No.7, 399-401 (2013) Case Reports in Clinical Medicine http://dx.doi.org/10.4236/crcm.2013.27106 Copyright © 2013 SciRes. OPEN ACCESS An experience of hyperbaric oxygen and transurethral coagulation combination therapy for abnormal vessels and intractable macrohematuria due to pelvic arteriovenous malformations Seiya Inoue1,2, Masashi Honda2*, Shinji Hirano2, Noriya Yamaguchi2, Bunya Kawamoto2, Tsounapi Panagiota2, Katsuya Hikita2, Kuniyasu Muraoka2, Takehiro Sejima2, Chihiro Takahashi1, At sushi Takenaka2 1Department of Urology, National Hospital Organization, Yonago Medical Center, Yonago, Japan; 2Department of Urology, Tottori University School of Medicine, Yonago, Japan; *Corresponding Author: [email protected] Received 6 August 2013; revised 5 September 2013; accepted 16 September 2013 Copyright © 2013 Seiya Inoue et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT A 78-year-old man was admitted to our hospital with a chief complaint of gross hematuria. The patient was diagnosed with pelvic arteriovenous malformations and repeated arterial emboliza- tion. A cystoscopy demonstrated that bladder trigone was covered by many clots. At the same time, bleeding mucosa at the right side of the bladder dome was confirmed. We administered hyperbaric oxygen therapy 7 days after admis- sion. Macrohematuria recovered gradually and we then performed transurethral coagulation at the dome with failed mucosa 14 days after ad- mission. Macrohematuria recovered completely and there was no recurrence during hospitaliza- tion. Thirty days after admission, we performed cystoscopy and found clear mucosa in the tri- gone. The patient was discharged 32 days after admission. Keywords: Hyperbari c O xy g en T h erapy; Macrohematuria; Pelvic Arteriovenous Malformations; Tra nsurethral C oagulation 1. INTRODUCTION Pelvic arteriovenous malformations (P-AVM) are rare, especially in males. Angiograph y is effective not only for the diagnosis, but also for embolization therapy of AVM in the pelvis; howeve r, we sometimes have to repeat em- bolization many times because of continuous symptoms or insufficient efficacies. In this report, we attempted hy- perbaric oxygen therapy (HBO) and transurethral coagula- tion (TUC) for abnormal vessels and persistent macrohe- maturia from P-AVM and showed good ef ficacies. 2. CASE REPORT A 78-year-old man was admitted to our hospital with a chief complaint of gross hematuria. It started 2 weeks before his admission. He was diagnosed with P-AVM 7 years before his admission and bilateral iliac artery em- bolization was performed a few times in another hospital. He used gabapentin for the continuous supurapubic dull pain that had continued for 20 years. There was no his- tory of previous trauma or abdominal surgery. His phy- sical examination was unremarkable. Laboratory data showed urinalysis with many red blood cells per high power field. Prothrombin time, partial thromboplastin time, and platelet count were normal. Ultrasonography demonstrated a hypoechoic region over the urinary blad- der. An abdominal-pelvic computed tomography (CT) scan demonstrated a large mass consisting of dilated- tortuous abnormal vessels in the pelvis th at was adherent to the anterior wall of the bladder and extended to the bottom of bladder. An enhanced CT scan was performed and we observed abnormal vessel invasion near the tri- gone (Figure 1). Cystoscopy revealed bleeding mucosa at the dome of the bladder wall (Figure 2). In addition, the bladder trigone was covered by many clots where the enhanced CT scan revealed abnormal vessel invasion. We diagnosed macrohematuria from the dome of the urinary bladder and abnormal vessels in the trigone due 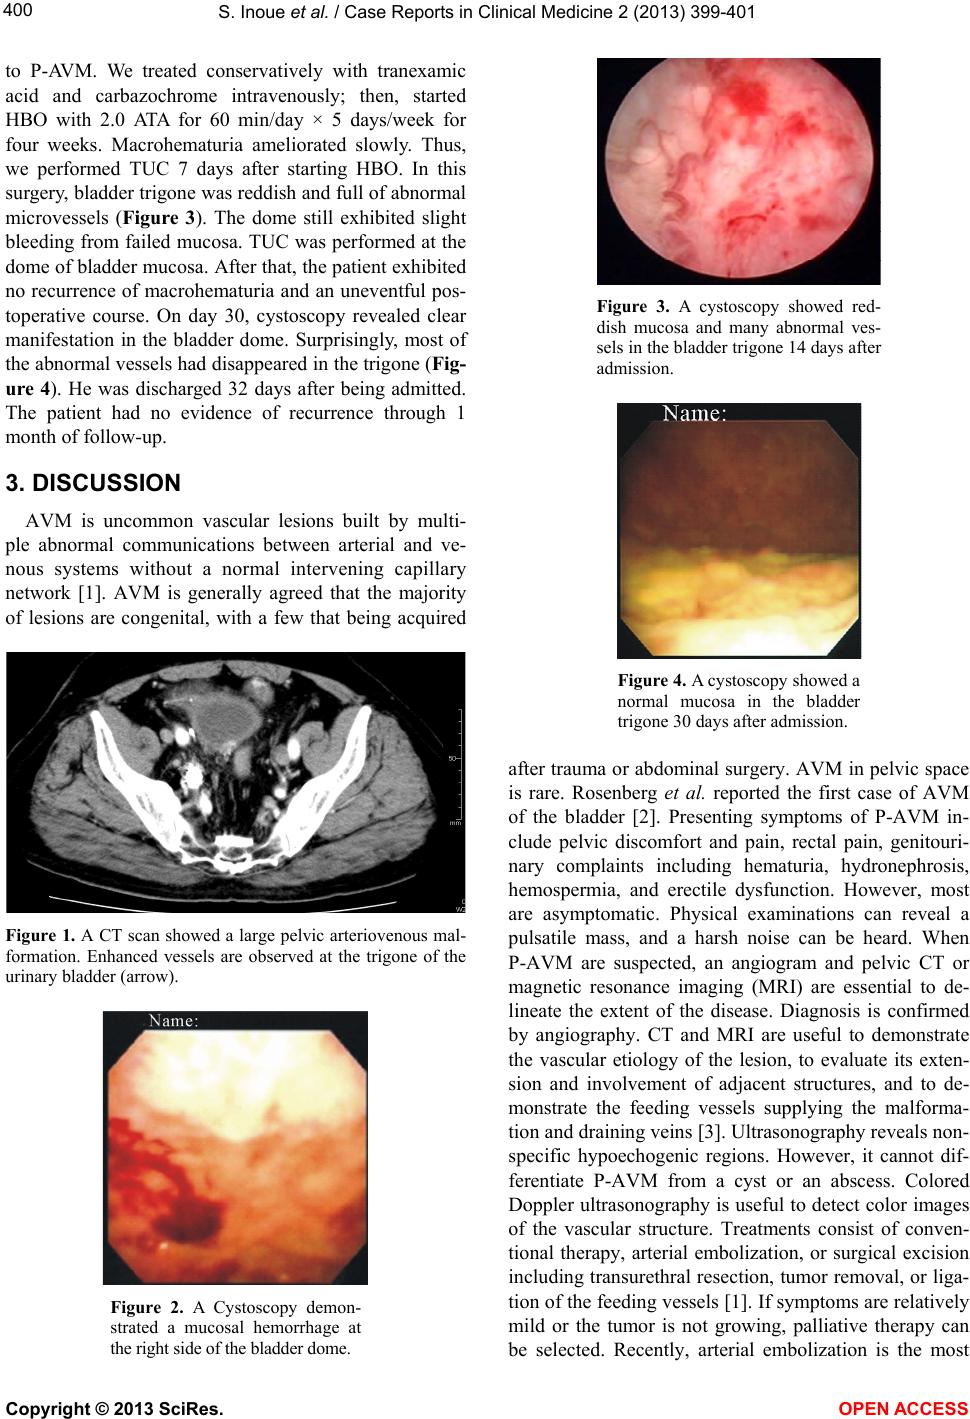 S. Inoue et al. / Case Reports in Clinical Medicine 2 (201 3) 399-401 Copyright © 2013 SciRes. OPEN ACCESS 400 to P-AVM. We treated conservatively with tranexamic acid and carbazochrome intravenously; then, started HBO with 2.0 ATA for 60 min/day × 5 days/week for four weeks. Macrohematuria ameliorated slowly. Thus, we performed TUC 7 days after starting HBO. In this surgery, bladder trigone was reddish and full of abnormal microvessels (Figure 3). The dome still exhibited slight bleeding from failed mucosa. TUC was performed at the dome of bladder mucosa. After that, the patient exhibited no recurrence of macrohematuria and an uneventful pos- toperative course. On day 30, cystoscopy revealed clear manifestation in the bladder dome. Surprisingly, most of the abnormal vessels had disapp eared in the trigon e (Fig- ure 4). He was discharged 32 days after being admitted. The patient had no evidence of recurrence through 1 month of follow-up. 3. DISCUSSION AVM is uncommon vascular lesions built by multi- ple abnormal communications between arterial and ve- nous systems without a normal intervening capillary network [1]. AVM is generally agreed that the majority of lesions are congenital, with a few that being acquired Figure 1. A CT scan showed a large pelvic arteriovenous mal- formation. Enhanced vessels are observed at the trigone of the urinary bladder (arrow). Figure 2. A Cystoscopy demon- strated a mucosal hemorrhage at the right side of the bladder dome. Figure 3. A cystoscopy showed red- dish mucosa and many abnormal ves- sels in the bladder trigone 14 days after admission. Figure 4. A cy stoscopy showed a normal mucosa in the bladder trigone 30 days after admission. after trauma or abdominal surgery. AVM in pelvic space is rare. Rosenberg et al. reported the first case of AVM of the bladder [2]. Presenting symptoms of P-AVM in- clude pelvic discomfort and pain, rectal pain, genitouri- nary complaints including hematuria, hydronephrosis, hemospermia, and erectile dysfunction. However, most are asymptomatic. Physical examinations can reveal a pulsatile mass, and a harsh noise can be heard. When P-AVM are suspected, an angiogram and pelvic CT or magnetic resonance imaging (MRI) are essential to de- lineate the extent of the disease. Diagnosis is confirmed by angiography. CT and MRI are useful to demonstrate the vascular etiology of the lesion, to evaluate its exten- sion and involvement of adjacent structures, and to de- monstrate the feeding vessels supplying the malforma- tion and draining veins [3]. Ultrasonography reveals non- specific hypoechogenic regions. However, it cannot dif- ferentiate P-AVM from a cyst or an abscess. Colored Doppler ultr asonography is useful to detect color images of the vascular structure. Treatments consist of conven- tional therapy, arterial embolization, or surgical excision including transurethral resection, tumor removal, or liga- tion of the feeding vessels [1]. If sympto ms are relatively mild or the tumor is not growing, palliative therapy can be selected. Recently, arterial embolization is the most  S. Inoue et al. / Case Reports in Clinical Medicine 2 (201 3) 399-401 Copyright © 2013 SciRes. OPEN ACCESS 401 common method used as the first line of treatment; however, it often fails. The most suitable indication of surgical treatment is still controversial; however, a lower number of collaterals or a small tu mor volume is easy to resolve with surgical treatment. HBO therapy is indi- cated for patients with hemorrhagic cystitis caused by radiation, intractable interstitial cystitis, or cyclophos- phamide-induced hemorrhagic cystitis. Nakada et al. demonstrated that essential macrohematuria patients treated with HBO (2.0 ATA for 30 days) had a signifi- cantly superior recovery than those without any treat- ment. Moreover, the time period of recovery is shorter than that of non-treated patients [4]. It has been demon- strated that HBO is associated with vasoconstriction in the systemic circulation and to a lesser extent in the coronary vasculature [5]. Activation of plasma kinins results in vasodilation, edema formation, or hypotension. Animals treated in the hyperbaric chamber at a pressure of 2.5 ATA saturated with 100% oxygen showed low levels of plasma kinins [6]. Such treatment presumably results in vasoconstriction and contributes to decrease in hematuria. The biological mechanism of HBO originated from hypersaturating oxygen dissolved in the plasma due to the treatment. Subsequently, HBO treatment stimu- lates leukocyte function characterized by phagocytosis, producing growth factors that enhance angiogenesis [7]. HBO therapy is well tolerated, and adverse effects of HBO are unusual, as visual disturbances, eustachian tube dysfunction, and claustrophobia are rare [8]. To our knowledge, there have been no reports about the use of HBO and TUC combination therapy for P-AVM. The present case showed the difficulties in treating macro- hematuria in spite of repeated arterial embolization. We performed HBO and TUC combination therapy for per- sistent macrohematuria, and confirmed a recovery of macrohematuria and reduction of abnormal vessels at the trigone. During HBO therapy, the patient felt ear fulln ess that resolved itself automatically. We supposed that un- der a high pressure of oxygen, angiogenesis progressed and abnormal vessels and damaged mucosa recovered. As this is a case report of only one patient, our data pro- vide the possibility of another treatment option for in- tractable macrohematuria and abnormal vessels patients who do not respond to conventional therapies. Careful observations are required. REFERENCES [1] Game, X., Berlizot , P., Hassan, T., Joffre, F., Chokairi, S., Houlgatte, A. and Rischmann, P. (2002) Congenital pelvic arteriovenous malformation in male patients: A rare case of urological symptoms and role of embolization. Euro- pean Urology, 42, 407-412. http://dx.doi.org/10.1016/S0302-2838(02)00355-X [2] Rosenberg, J., Golimbu, M., Suarez, J. and Morales, P. (1973) Congenital arteriovenous malformation of the bladder. Journal of Urology, 109, 605-608. [3] Jacobowitz, G.R., Rosen, R.J., Rockman, C.B., Nalban- dian, M., Hofstee, D.J., Fioole, B., Adelman, M.A., Lamparello, P.J., Gagne, P. and Riles, T.S. (2001) Tran- scatherter embolization of complex pelvic vascular mal- formations: Results and long-term follow-up. Journal of Vascular Surgery, 33, 51-55. [4] Nakada, T., Sasagawa, I., Koike, H., Furuta, T., Katayama, K., Ota, K., Chikenji, M., Matsushita, T. and Saito, H. (1989) Effect of hyperbaric oxygen therapy on essential haematuria. International Urology and Nephrology, 21, 3-8. [5] Mogelson, S., Davidson, J., Sobel, B.E. and Roberts, R. (1981) The effect of hyperbaric oxygen on infarct size in the conscious animal. European Journal of Cardiology, 12, 135-146. [6] Sumida, S. and Yagi, H. (1981) Experimental study on the inhibition of kinin release in endotoxin shock by glu- tathione, proteinase inhibitors, hydrocortisone and hy- perbaric oxygen. Japanese Circulation Journal, 45, 1364- 1368. [7] Hader, J.E., Marzella, L., Myers, R.A., Jacobs, S.C. and Naslund, M.J. (1993) Hyperbaric oxygen treatment for experimental cyclophosphamide-induced hemorrhagic cys- titis. Journal of Urology, 149, 1617-1621. [8] Capelli-Schellpferffer, M. and Gerber, G.S. (1999) The use of hyperbaric oxygen in urology. Journal of Urology, 162, 647-654. |