

Paper Menu >>
Journal Menu >>
 Open Journal of Anesthesiology, 2013, 3, 345-348 http://dx.doi.org/10.4236/ojanes.2013.38073 Published Online October 2013 (http://www.scirp.org/journal/ojanes) 345 Pneumothorax Complicating Port-a-Cath and Groshong Catheter Positioning in Children: Our Experience before Routine Ultrasound-Guided Puncture* Silvia Guenzani1,2#, Paola Previtali2, Federico Piccioni2, Maria Chiara Allemano2, Serena Catania3, Martin Langer1,2 1Department of Pathophysiology and Transplantation, University of Milan, Milan, Italy; 2Department of Anesthesia, Intensive Care and Palliative Care, Fondazione IRCCS Istituto Nazionale dei Tumori, Milan, Italy; 3Pediatric Oncology Unit, Fondazione IRCCS Istituto Nazionale dei Tumori, Milan, Italy. Email: #[email protected] Received June 18th, 2013; revised July 20th, 2013; accepted August 19th, 2013 Copyright © 2013 Silvia Guenzani et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT Objective: To study incidence and management of long term central venous catheter (CVC) placement related pneu- mothorax (PNX) in children. Aim: To construct a baseline value before the introduction of systematic use of ultrasound guidance, which requires specific training and equipment. Background: Anesthesia Service and Pediatric Oncology of the Italian National Cancer Center; patients were children (age ≤ 18 years) with solid tumors, needing long-term central venous catheters (Groshong or Port-a-Cath). Materials/Methods: Catheter placement was performed, mostly under general anesthesia, utilizing a micropuncture 5 - 7 Fr needle and fluoroscopy. In the study period ultrasound was used only in case of previously failed attempts. Relevant data were collected retrospectively. Results: From August 2008 to December 2011, 452 catheters were implanted to our patients. The prevalent approach was from subclavian vein (left 85.7%, right 9.7%); in few cases internal jugular vein was chosen (right 2.4%, left 2.2%). Pneumothorax occurred in 14 patients (3.1%; 95%CI 1.9 - 5.1). In 4/14 children the PNX was considered minimal and not treated. In 10 patients the PNX was drained. In 7 cases a traditional, surgical thoracostomy was performed, while in 3 children a 14-Ga polyure- thane catheter (Arrow International®) was inserted over a wire guide in the pleural space by anaesthetists. Conclusions: In our centre rates of PNX are the same as those described in literature and are expected to lower when ultrasound guid- ance of the puncture will be routinely applied. Percutaneous drainage of PNX seems as effective as surgically placed thoracostomy catheter, but less invasive. Keywords: Pneumothorax; Central Venous Catheter; Groshong; Port-a-Cath; Children; Drainage 1. Introduction Long term venous access through totally implantable venous access devices (TIVAD), partially implantable tunneled cuffed catheters, or more recently peripherically inserted central venous catheters (PICC) are essential for administering chemotherapy also to young oncologic patients. Positioning of these catheters is reported as a relatively safe procedure with little associated morbidity and nearly no mortality, where this risk is outweighed by the benefit obtained [1]. An implanted port is preferred when its use is inter- mittent (the skin protects the device from infections and rupture) and can remain in situ for years, while an exter- nal catheter is commonly used for continuous infusion during a shorter period of time. Percutaneous positioning of catheters can be achieved by various central accesses: through the subclavian vein (SCV), the internal jugular vein (IJV), or, in special cases, the femoral vein, while the brachial vein is preferred for PICC insertion. Pneumothorax (PNX) is a typical early, mechanical complication of the puncture of the subclavian vein. The SCV approach is more frequently used than the IJV ac- cess in small children because the exit site is placed at proper distance from the mouth, it is easy to protect and *Important Note: Main results of this study have been presented as oral communication at SMART CONFERENCE on May 2012, this is why you can find a similar abstract at this link: http://www.altrimedia.biz/smart-cd2012/Comunicazioni_Libere/10_TE RAPIA_INTENSIVA_PEDIATRICA/54_Guenzani.pdf. #Corresponding author. Copyright © 2013 SciRes. OJAnes  Pneumothorax Complicating Port-a-Cath and Groshong Catheter Positioning in Children: Our Experience before Routine Ultrasound-Guided Puncture 346 tunneling of the catheter is rather simple and linear. The infraclavicular, landmark based insertion for long term central venous catheters (CVCs) in children is a widely used approach, but ultrasound (US) guidance is difficult. Also in our center catheter placement in pediatric patients under sonographic guidance is still uncommon, and anes- thetists usually perform a landmark based puncture of the SCV, with the approach through the IJV as second choice. In this retrospective study we try to assess the risk of PNX in our experience compared to the literature, in or- der to discuss/revise our catheter placement policy in children. 2. Materials and Methods Two options for elective long term venous accesses are available at our Hospital: Port-a-Cath (Titanium Low- Profile Implantable Port-Bard Access Systems or others), a totally implantable venous access device (TIVAD), and Groshong catheter (Bard Access Systems), a tunneled external silicon-rubber device with a three-position pres- sure-sensitive valve near the distal tip. Long term CVC placement in pediatric patients is proposed by pediatric oncologists to the anesthesia ser- vice. The preoperative evaluation includes medical his- tory, body examination to evaluate their physical habitus and anatomic pitfalls (obesity, chest tumors or adeno- pathies of the mediastinum), laboratory exams (com- plete blood and platelet count, coagulation screening) and a chest X-ray. Cannulation is performed percutane- ously in an operating room where anesthesia facilities and C-arm X-ray machine are available. Left infraclavicular SCV cannulation is the access of first choice. If more then one attempt fails, other sites (IJV) are tried. A micropuncture set (Micropuncture In- troducer Set 5.0 - 7.0 Fr-Cook) is used for the puncture of the vein and catheters are inserted under fluoroscopic control. In nearly all pediatric patients the procedure is performed under general, total intravenous anesthesia, mechanical ventilation and standard monitoring. There is no dedicated catheter-team and all staff anesthetists and many residents are actively involved. A chest X-ray is performed 6 - 12 hrs after catheter placement to document the location of catheter tip and to rule out mechanical complications like PNX, and hemo- or hydrothorax. In case of evidence of PNX the need for drainage is discussed with a thoracic surgeon and/or a staff-anesthe- tist, taking into account the clinical symptoms, size and progression of the pneumothorax. Drainage of PNX is performed by the thoracic surgeon with a 16Ch chest tube drainage, or by the anesthetist with a single-lumen 14Ga venous catheter (Arrow® International-central ve- nous catheterization set) over a wire guide, after percu- taneous puncture of the pleural space. The choice be- tween chest tube drainage or percutaneous catheter is not standardized yet, but we are getting used to utilize in- creasingly the less invasive option. Data analysis was performed using IBM SPSS Statis- tics v19. Chi-quare test was adopted to compare discrete variables. Normality distribution of continuous variables was verified with Shapiro-Wilk test. T-test for inde- pendent groups was used to compare parametric data. A p value of less than 0.05 was considered as statistically significant. 3. Results From August 2008 to December 2011, 452 long term vascular access devices were implanted in pediatric pa- tients (median age 8 years, range 3 months - 18 years) at our Institute. In 159 (35.2%) children a Groshong catheter was cho- sen and in 293 (64.8%) a TIVAD. Infraclavicular SCV cannulation was in all cases the access of first choice, followed by puncture of IJV when more than one attempt failed. The procedure was performed in 93% of cases under general anesthesia, and in 7% of cases with local anesthesia. The final catheterization site was primarly the subclavian vein (left SCV 85.7%, right SCV 9.7%, right IJV 2.4%, left IJV 2.2%). Anatomic landmark oriented puncture was the first choice technique in all patients, US guidance after initial failed attempts was performed in 2% of the procedures. PNX was diagnosed at the control chest X-ray in 14 cases (3.1%; 95%CI 1.9 - 5.1) always after several failed punctures of the SCV. See Table 1 for patients’ demo- graphic data. Ten of these patients underwent PNX drai- nage, in 4 cases the PNX was minimal, not requiring any treatment. Seven patients underwent a 16Ch tube thora- costomy, while in 3 cases the pleural air was drained by a single-lumen 14Ga venous catheter (Arrow® Interna- tional-central venous catheterization set). In the latter approach air was aspired by a syringe once or twice a day with the catheter locked during the intervals. Chest tubes and “chest catheters” remained in situ for a variable pe- riod between 2 and 12 days (average: catheters for 4.3 days, chest tubes for 5.6 days; p = 0.633). No other early complications or long term consequences were recorded. 4. Discussion In our study the rate of pneumothorax (3.1%; 95%CI 1.9 - 5.1) after a central venous catheter insertion by punc- ture of the SCV (infraclavicular approach) was in the higher range, compared to the pooled data (Table 2 and Figure 1) from 7 pertinent studies in 2839 children (1.7%; 95%CI 1.3 - 2.3) [28]. The 1.4% difference is - Copyright © 2013 SciRes. OJAnes 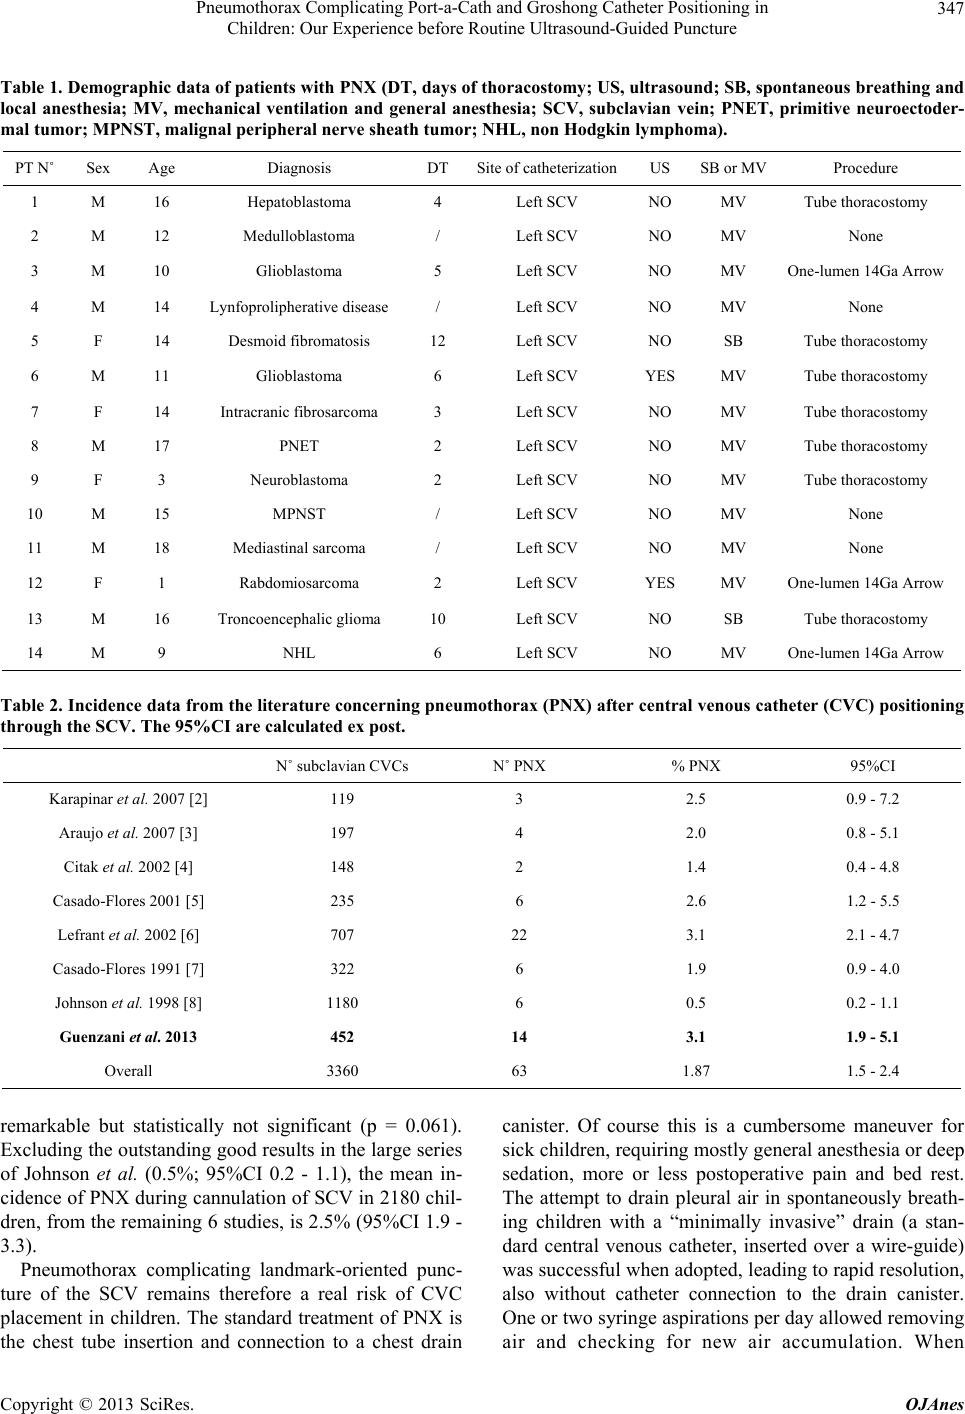 Pneumothorax Complicating Port-a-Cath and Groshong Catheter Positioning in Children: Our Experience before Routine Ultrasound-Guided Puncture Copyright © 2013 SciRes. OJAnes 347 Table 1. Demographic data of patients with PNX (DT, days of thoracostomy; US, ultrasound; SB, spontaneous breathing and local anesthesia; MV, mechanical ventilation and general anesthesia; SCV, subclavian vein; PNET, primitive neuroectoder- mal tumor; MPNST, malignal peripheral nerve sheath tumor; NHL, non Hodgkin lymphoma). PT N˚ Sex Age Diagnosis DT Site of catheterizationUS SB or MV Procedure 1 M 16 Hepatoblastoma 4 Left SCV NO MV Tube thoracostomy 2 M 12 Medulloblastoma / Left SCV NO MV None 3 M 10 Glioblastoma 5 Left SCV NO MV One-lumen 14Ga Arrow 4 M 14 Lynfoprolipherative disease / Left SCV NO MV None 5 F 14 Desmoid fibromatosis 12 Left SCV NO SB Tube thoracostomy 6 M 11 Glioblastoma 6 Left SCV YES MV Tube thoracostomy 7 F 14 Intracranic fibrosarcoma 3 Left SCV NO MV Tube thoracostomy 8 M 17 PNET 2 Left SCV NO MV Tube thoracostomy 9 F 3 Neuroblastoma 2 Left SCV NO MV Tube thoracostomy 10 M 15 MPNST / Left SCV NO MV None 11 M 18 Mediastinal sarcoma / Left SCV NO MV None 12 F 1 Rabdomiosarcoma 2 Left SCV YES MV One-lumen 14Ga Arrow 13 M 16 Troncoencephalic glioma 10 Left SCV NO SB Tube thoracostomy 14 M 9 NHL 6 Left SCV NO MV One-lumen 14Ga Arrow Table 2. Incidence data from the literature concerning pneumothorax (PNX) after central venous catheter (CVC) positioning through the SCV. The 95%CI are calculated ex post. N˚ subclavian CVCs N˚ PNX % PNX 95%CI Karapinar et al. 2007 [2] 119 3 2.5 0.9 - 7.2 Araujo et al. 2007 [3] 197 4 2.0 0.8 - 5.1 Citak et al. 2002 [4] 148 2 1.4 0.4 - 4.8 Casado-Flores 2001 [5] 235 6 2.6 1.2 - 5.5 Lefrant et al. 2002 [6] 707 22 3.1 2.1 - 4.7 Casado-Flores 1991 [7] 322 6 1.9 0.9 - 4.0 Johnson et al. 1998 [8] 1180 6 0.5 0.2 - 1.1 Guenzani et al. 2013 452 14 3.1 1.9 - 5.1 Overall 3360 63 1.87 1.5 - 2.4 remarkable but statistically not significant (p = 0.061). Excluding the outstanding good results in the large series of Johnson et al. (0.5%; 95%CI 0.2 - 1.1), the mean in- cidence of PNX during cannulation of SCV in 2180 chil- dren, from the remaining 6 studies, is 2.5% (95%CI 1.9 - 3.3). Pneumothorax complicating landmark-oriented punc- ture of the SCV remains therefore a real risk of CVC placement in children. The standard treatment of PNX is the chest tube insertion and connection to a chest drain canister. Of course this is a cumbersome maneuver for sick children, requiring mostly general anesthesia or deep sedation, more or less postoperative pain and bed rest. The attempt to drain pleural air in spontaneously breath- ing children with a “minimally invasive” drain (a stan- dard central venous catheter, inserted over a wire-guide) was successful when adopted, leading to rapid resolution, also without catheter connection to the drain canister. One or two syringe aspirations per day allowed removing air and checking for new air accumulation. When  Pneumothorax Complicating Port-a-Cath and Groshong Catheter Positioning in Children: Our Experience before Routine Ultrasound-Guided Puncture 348 Figure 1. Incidence data from the literature concerning pneumothorax (PNX) after central venous catheter (CVC) positioning through the SCV. The 95%CI are calculated ex post. no more air was aspired for 24 hrs the catheter was re- moved. The advantage of this approach in children with “non-tension” pneumothorax after accidental pleural puncture is the minimal invasiveness of the procedure and the limited discomfort for the patient. To achieve the “zero complication” option of CVC in- sertion, however, a change in our CVC placement policy will be necessary. US guidance techniques have become the gold standard for catheterization of IJV in children. However, IJV catheterization is a difficult procedure in infants, because of anatomy of the region. The SCV ap- proach is preferred in this population. Compared to the classical landmark technique, the US infraclavicular guided cannulation permits puncturing more laterally, reducing not only PNX but also costoclavicular pinch-off complication [9]. Lateral approach is, however, difficult in small children, because of the thinness of the thorax. An ideal alternative, in infants, can be the US supra- cla- vicular approach [10], with a supraclavicular catheter tunnellization, which offers a good view of the needle and the vein, without any US shadow of the clavicle, and avoids catheter pinch. 5. Acknowledgements The authors and their colleges are grateful to Mariolina Bonalumi, MD who started the long term central venous catheter program for children in our Institute and tutored most of us. This study is supported by the “5‰ donations” to the Fondazione IRCCS, Istituto Nazionale dei Tumori, Mi- lano. REFERENCES [1] A. Zaghal, M. Khalife, D. Mukherji, et al., “Update on Totally Implantable Venous Access Devices,” Surgical Oncology, Vol. 21, No. 3, 2012, pp. 207-215. http://dx.doi.org/10.1016/j.suronc.2012.02.003 [2] B. Karapinar and A. Cura, “Complications of Central Venous Catheterization in Critically Ill Children,” Pedi- atrics International, Vol. 49, No. 5, 2007, pp. 593-599. http://dx.doi.org/10.1111/j.1442-200X.2007.02407.x [3] C. C. Araujo, M. C. Lima and G. H. Falbo, “Percutaneous Subclavian Central Venous Catheterization in Children and Adolescents: Success, Complications and Related Factors,” Jornal de Pediatria, Vol. 83, No. 1, 2007, pp. 64-70. http://dx.doi.org/10.1111/j.1442-200X.2007.02407.x [4] A. Citak, M. Karabocuoglu, R. Ucsel and N. Uzel, “Cen- tral Venous Catheters in Pediatric Patients—Subclavian Venous Approach as the First Choice,” Pediatrics Inter- national, Vol. 44, No. 1, 2002, pp. 83-86. http://dx.doi.org/10.1046/j.1442-200X.2002.01509.x [5] J. Casado-Flores, J. Barja, R. Martino, A. Serrano and Valdivielso, “A Complications of Central Venous Cathe- terization in Critically Ill Children,” Pediatric Critical Care Medicine, Vol. 2, No. 1, 2001, pp. 57-62. http://dx.doi.org/10.1097/00130478-200101000-00012 [6] J. Y. Lefrant, L. Muller, J. E. De La Coussaye, M. Prud- homme, J. Ripart, C. Gouzes, P. Peray, G. Saissi and J. J. Elrdjam, “Risk Factors of Failure and Immediate Com- plication of SCV Catheterization in Critically Ill Pa- tients,” Intensive Care Medicine, Vol. 28, No. 8, 2002, pp. 1036-1041. http://dx.doi.org/10.1007/s00134-002-1364-9 [7] J. Casado-Flores, A. Valdivielso-Serna, L. Perez-Jurado, J. Pozo-Roman, M. Monleon-Luque, J. Garcia-Perez, A. Ruiz-Beltran and M. A. Garcia-Teresa, “SCV Catheteri- zation in Critically Ill Children: Analysis of 322 Cannula- tions,” Intensive Care Medicine, Vol. 17, No. 6, 1991, pp. 350-354. [8] E. M. Johnson, D. A. Saltzman, G. Suh, R. A. Dahms and A. S. Leonard, “Complications and Risks of Central Ve- nous Catheter Placement in Children,” Surgery, Vol. 124, No. 5, 1998, pp. 911-916. http://dx.doi.org/10.1016/S0039-6060(98)70016-9 [9] T. Pirotte and F. Veyckemans, “Ultrasound-Guided Sub- clavian Vein Cannulation in Infants and Children: A Novel Approach,” British Journal of Anaesthesia, Vol. 98, No. 4, 2007, pp. 509-514. http://dx.doi.org/10.1093/bja/aem041 [10] O. Rhondali, R. Attof, S. Combet, D. Chassard and M. de Queiroz Siqueira, “Ultrasound-Guided SCV Cannulation in Infants: Supraclavicular Approach,” Pediatric Anesthe- sia, Vol. 21, No. 11, 2011, pp. 1136-1141. http://dx.doi.org/10.1111/j.1460-9592.2011.03614.x Copyright © 2013 SciRes. OJAnes |