

Paper Menu >>
Journal Menu >>
 Journal of Cosmetics, Dermatological Sciences and Applications, 2013, 3, 228-233 http://dx.doi.org/10.4236/jcdsa.2013.33035 Published Online September 2013 (http://www.scirp.org/journal/jcdsa) Evaluat io n o f th e E ff ec ts of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis Carol Courderot-Masuyer1, Sophie Robin1, Hélène Tauzin1, Sylvain Harbon2, Sophie Mac-Mary3, Alexandre Guichard4, Patrice Muret5, Philippe Humbert6* 1Bioexigence SARL, Espace Lafayette, 8 rue Alfred de Vigny, Besançon, France; 2Plastic Surgery, 9 rue Klein, Saint Vincent Clinic, Besançon, France; 3Skinexigence SAS, immeuble Bioparc, 2 rue du Dr Paul Milleret, Besançon, France; 4Research and Clinicl Cen- ter on the Tegument (CERT); Clinical Investigation Center (CIC BT506), Department of Dermatology, Besançon University Hospi- tal, Besançon, France; 5Laboratory of Clinical and Toxicology Pharmacology, Jean Minjoz University Hospital, Besancon, France; 6University of Franche-Comté, Inserm U1098, SFR FED 4234 IBCT, Besançon, France. Email: *[email protected] Received August 2nd, 2013; revised August 27th, 2013; accepted September 2nd, 2013 Copyright © 2013 Carol Courderot-Masuyer et al. This is an open access article distributed under the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT The purpose of the study was to evaluate the effects of corticosteroids on histamine release and to compare their po- tency with the MacKenzie classification based on their vasoconstrictor effects. Thank s to ex vivo cutaneous microdialy- sis, we studied histamine-induced release over a period of time on excised abdominal skin from women. Eight corticos- teroids were topically applied with occlusiv e dressing onto the skin, above prob es, before anti-IgE injection. Histamine levels were assessed by an EIA method. In order to compare the different corticosteroids, AUC was calculated allowing an estimation of the amount of released histamine for 60 min of ex vivo cutaneous microdialysis. Diflucortolone 0.1% and micronized betamethasone dipropionate 0.05% are considered as corticosteroids with high potency in MacKenzie classification. Betamethasone dipropionate associated with propylene glycol 0.05%, belongs to a stronger class in Mackenzie classification. Our results showed that the decrease in histamine release was more important with difluocor- tolone than with both of these corticosteroids. Therefore there was no correlation between the vasoconstrictor potency of topical corticosteroids and their ability to inhib it histamine release. Keywords: MacKenzie Test; Corticosteroids; ex Vivo Cutaneous Microdialysis; Histamine 1. Introduction The McKenzie’s classification of topical corticosteroids is based on the ability to produce the blanching of the skin when they are in contact with them [1,2]. The inten- sity of skin blanching has been correlated with drug po- tency and the degree of drug deliv ery th rough th e stratum corneum. The vasoconstrictor assay has also been used to measure the bioavibility and bioequivalence of topical corticosteroids formulations and was adopted in 1995 for bioequivalence determination by the US Food and Drug Administration (FDA) [3,4]. The technique consisted of the application of corticosteroid solutions on the skin covered with plastic occlusive bandages. The results were evaluated 16 hours after application. This technique described a quantitative comparison of the vasoconstric- tor effect of topically applied corticosteroids in healthy human skin. However, there is no direct proof that the vasoconstrictor and anti-inflammatory activities are correlated. Amongst potentially suitable surro gates for in vivo clinical tests, there are in vitro dermatopharmaco- kinetic methods such as the Franz cells system [5,6] and ex vivo cutaneous microdialysis, in which the rate and extent of permeation through ex vivo skin is measured. In Franz cells, the subcutaneous fat was removed, not in ex vivo cutaneous microdialysis allowing a model closer to the in vivo co nditions. Even thoug h the blood flow is not present, we can compare the cutaneous permeation of different formulations of corticosteroids. The microdialy- sis (MD) principle can be compared to an artificial blood vessel. MD sampling is performed by placing a tubular MD membrane into the dermis, parallel to the skin’s sur- face. The probe, which is permeable to water and small molecules, is continuously perfused with a physiological buffer solution at a low flow rate. Unbound substances *Corresponding author. Copyright © 2013 SciRes. JCDSA  Evaluation of the Effects of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis 229 present in the skin can cross the membrane and enter the lumen probe in proportion to a concentration gradient [7]. Leveque et al. compared Franz cells and microdialysis for the skin absorption of salicylic acid and showed that the permeation profiles of salicylic acid determined by the both methods were similar [8]. MD can follow the evolution of dermis concentrations of endogenous com- ponents as well as exogenous components over a period of time. Topical corticosteroids are commonly used in the treatment of immuno-allergic conditions. We decided to carry out an experiment in order to measure directly the ability of topical corticosteroids to inhibit histamine release in an original ex-vitro model using cutaneous microdialysis because the integrity of skin barrier func- tion is maintained. We compared the McKenzie classi- fication of corticosteroids to this new classification ac- cording their effect on histamine release. Indeed mast cells are well known to play a central role in the forma- tion of allergic inflammation and con tribute to the patho- genesis of allergic diseases, including atopic dermatitis and psoriasis. So histamine plays a pivotal role in the pathogenesis of allergic inflammation. It is known that the dermis of psoriatic plaques contains an increased number of mast cells [9]. Krogstad et al. reported that histamine concentration and release are increased in le- sional skin of psoriatic patients [10]. Indeed mast cells reside in all vascularized tissues and particularly high mast cell numbers can be found at the interfaces of host and environment, such as the skin. Release of histamine and “slow reacting substance of anaphylaxis” from mast cells following crosslinking of cell-bound IgE by aller- gen was demonstrated in 1985 by Ishizaka et al. [11]. Our study is based on experiments performed by Peter- sen et al. who induced histamine release from resident dermal mast cells of excised female abdominal skin with an intradermal injection of a solution of anti-IgE with a maximum peak around 15 minutes of microdialysis [12]. Thus it is possible to calculate the area under the curve for the release of histamine and to use this data to clas- sify the corticosteroids in accordance with their effects on histamine release. 2. Materials and Methods Products Eight corticosteroids creams were obtained from phar- macy: micronized betamethasone dipropionate 0.05% (Dip- rosone®) (0.0 5 % mBD) betamethasone dipropionate 0.05% with propylene glycol (Diprolene®) (BdD + PG 0.05%) desonide 0.05% (Tridesonit®) (DES 0.05%) desoni de 0.1% (Locap r ed ®) (DES 0.1%) betam e thasone valerate 0.1% ( B e t n eva l®) (BV 0.1%) diflucortolone val e rate 0.1% (N eri sone®) (DF 0.1%) hydrocortisone butyrate 0.1% (Locoid®) (HB 0.1%) clobetasol propionat e 0.05% (Dermoval®). (CP 0.05%) Anti-IgE solution was purchased from Dako (France). Histamine EIA kits were obtained from Beckman Coulter (Paris, France). Skin speci m en s For these experiments, 16 excised abdominal skin (operative wastes) were obtained from surgery procedure and were used as soon as possible after their excision (mean age of women: 41.0 ± 2.3 years). The allergic status of the donors was not known. Informed consent was obtained from each subject before surgery. Skin fragments were cut and placed immediately in phosphate buffer (PBS, PAA laboratories, France) and the tem- perature of 37˚C of phosphate buffer was maintained during the experiments. The cutting of skin fragments makes it possible to repeat the measurements of hista- mine release twelve times for each corticosteroid after the application of the cream. Microdia lysis Experi m ent The microdialysis system consisted of a CMA/100® syringe pump (Phymed, Paris, France) and CMA/140 microfraction collector, which collected samples. The microdialysis probes (CMA/20®) had a 20-kD cutoff with a polycarbonate membrane (length 10 mm. For each corticosteroid, a total of 12 microdialysis probes were used to determine their potency on the inhibition of his- tamine release after anti-IgE antibody injection. So each skin fragment was cut into several parts. Histamine re- lease was induced after 1 hour of stabilization following the cutting of the skin and the insertion of microdialysis probes. Microdialysis samples were collected 5 minutes before the induction of histamine liberation (T0) and the micro- dialysis lasted 1 hour with sampling of extracellular der- mal fluid every 5 minutes. Probes were used in order to determine basal histamine release after anti-IgE inject- tion. The corticosteroids tested were topically applied with occlusive dressing (TegadermTM, 3M, France) on the skin above each probe, four hours before anti-IgE injection. Microdialysis started 5 minutes before the histamine re- leased and lasted 1 hour with sampling every 5 minutes (Figure 1). Determination of histamine in dialysates The concentration of histamine in the dialysate was determined by EIA using a commercially available ana- lytic kit for histamine. In order to compare the different corticosteroids, AUC (area under the curve) was calcu- lated allowing an estimation of the amount of released histamine during the period of 60 min of microdialysis on excised skins. For each skin fragment, the kinetic Copyright © 2013 SciRes. JCDSA 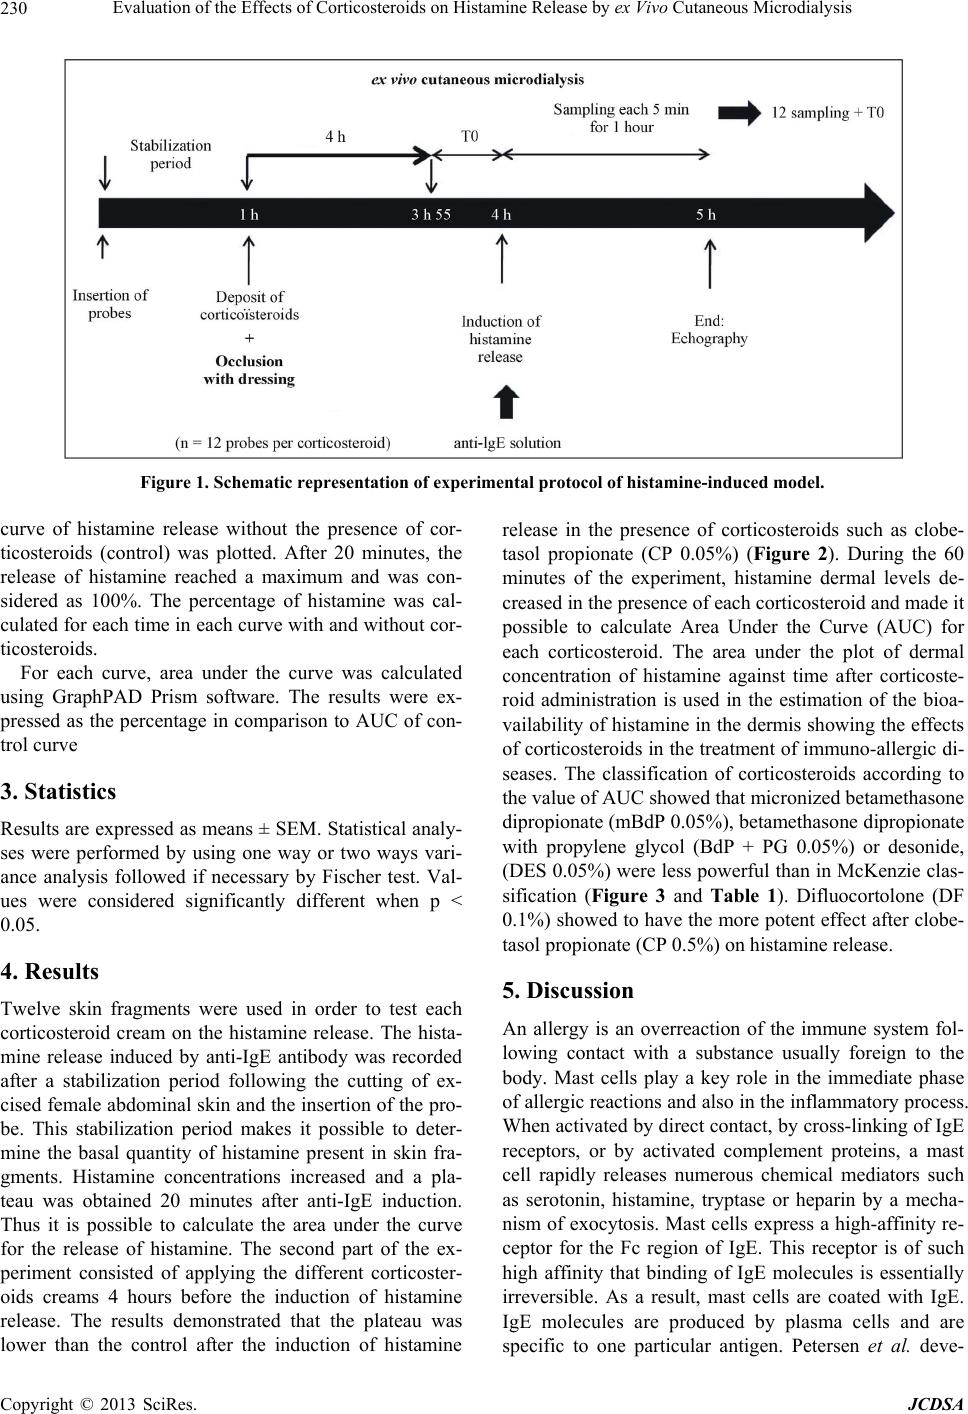 Evaluation of the Effects of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis Copyright © 2013 SciRes. JCDSA 230 Figure 1. Schematic representation of experimental protocol of histamine-induced model. curve of histamine release without the presence of cor- ticosteroids (control) was plotted. After 20 minutes, the release of histamine reached a maximum and was con- sidered as 100%. The percentage of histamine was cal- culated for each time in each curve with an d without cor- ticosteroids. release in the presence of corticosteroids such as clobe- tasol propionate (CP 0.05%) (Figure 2). During the 60 minutes of the experiment, histamine dermal levels de- creased in the presence of each corticosteroid and made it possible to calculate Area Under the Curve (AUC) for each corticosteroid. The area under the plot of dermal concentration of histamine against time after corticoste- roid administration is used in the estimation of the bioa- vailability of histamine in th e dermis showing the effects of corticosteroids in the treatment of immuno-allergic d i- seases. The classification of corticosteroids according to the value of AUC showed that micronized betamethasone dipropionate (mBdP 0.05%), betamethasone dipropionate with propylene glycol (BdP + PG 0.05%) or desonide, (DES 0.05%) were less powerful than in McKenzie clas- sification (Figure 3 and Table 1). Difluocortolone (DF 0.1%) showed to have the more potent effect after clobe- tasol propionate (CP 0.5%) on histamine release. For each curve, area under the curve was calculated using GraphPAD Prism software. The results were ex- pressed as the percentage in comparison to AUC of con- trol curve 3. Statistics Results are expressed as means ± SEM. Statistical analy- ses were performed by using one way or two ways vari- ance analysis followed if necessary by Fischer test. Val- ues were considered significantly different when p < 0.05. 4. Results 5. Discussion Twelve skin fragments were used in order to test each corticosteroid cream on the histamine release. The hista- mine release induced by anti-IgE antibody was recorded after a stabilization period following the cutting of ex- cised female abdominal skin and the insertion of the pro- be. This stabilization period makes it possible to deter- mine the basal quantity of histamine present in skin fra- gments. Histamine concentrations increased and a pla- teau was obtained 20 minutes after anti-IgE induction. Thus it is possible to calculate the area under the curve for the release of histamine. The second part of the ex- periment consisted of applying the different corticoster- oids creams 4 hours before the induction of histamine release. The results demonstrated that the plateau was lower than the control after the induction of histamine An allergy is an overreaction of the immune system fol- lowing contact with a substance usually foreign to the body. Mast cells play a key role in the immediate phase of allergic reaction s and also in th e inflammatory pro cess. When activated by direct contact, by cross-linking of IgE receptors, or by activated complement proteins, a mast cell rapidly releases numerous chemical mediators such as serotonin, histamine, tryptase or heparin by a mecha- nism of exocytosis. Mast cells express a high-affinity re- ceptor for the Fc region of IgE. This receptor is of such high affinity that binding of IgE molecules is essentially irreversible. As a result, mast cells are coated with IgE. IgE molecules are produced by plasma cells and are specific to one particular antigen. Petersen et al. deve- 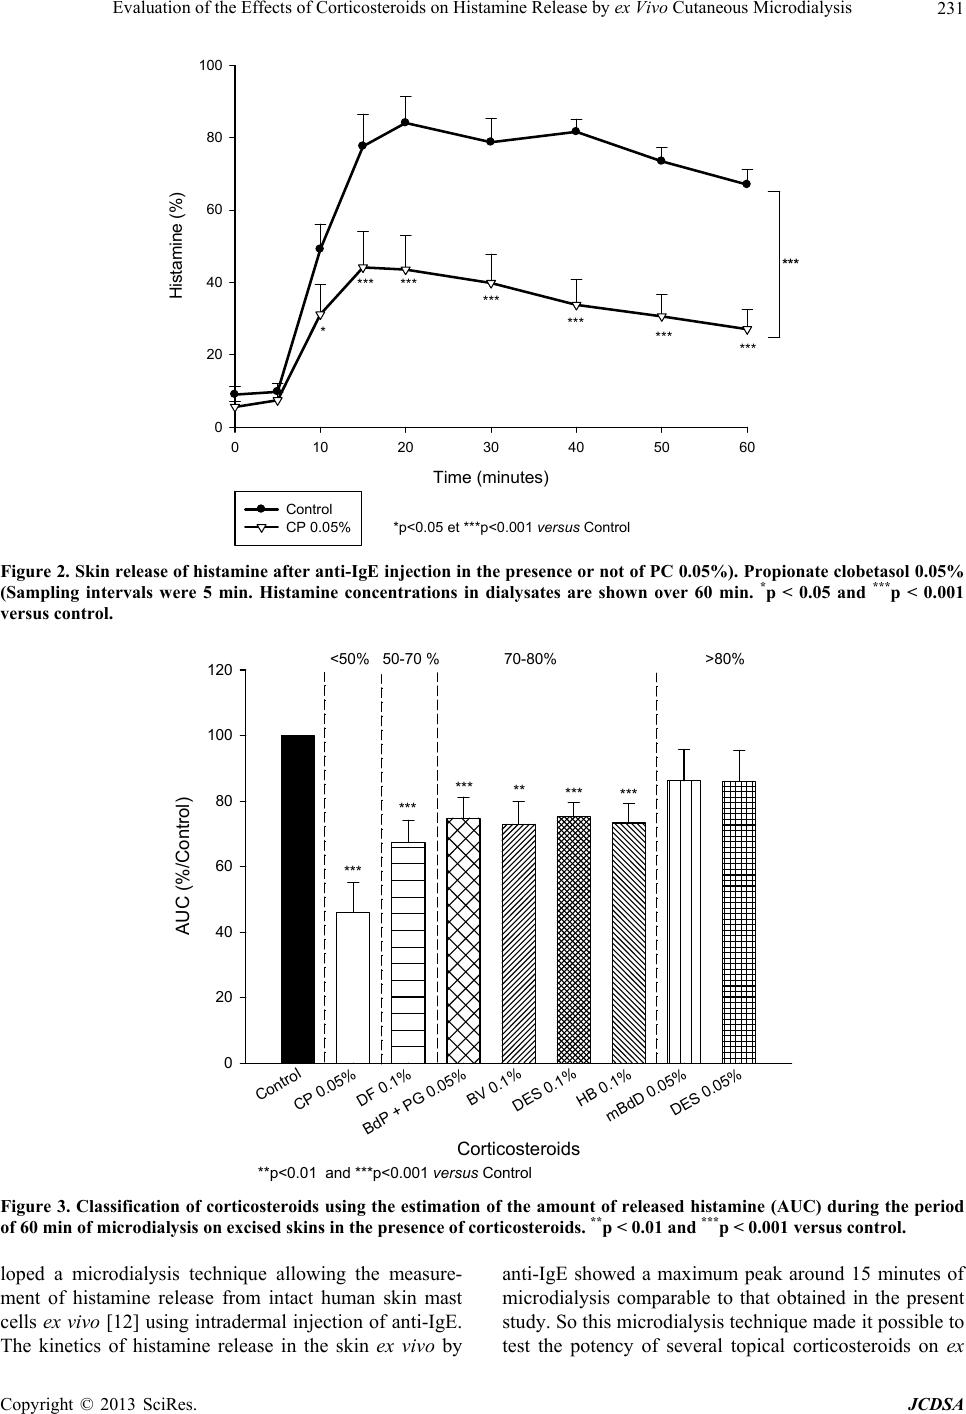 Evaluation of the Effects of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis 231 Time (minutes) 0 102030405060 Histamine (%) 0 20 40 60 80 100 Control CP 0.05% * *** *** *** *** *** *p<0.05 et ***p<0.001 versus Control *** *** Figure 2. Skin release of histamine after anti-IgE injection in the presence or not of PC 0.05%). Propionate clobetasol 0.05% (Sampling intervals were 5 min. Histamine concentrations in dialysates are shown over 60 min. *p < 0.05 and ***p < 0.001 versus control. Corticosteroids **p<0.01 and ***p<0.001 versus Control Control CP 0.05% DF 0.1% BdP + PG 0.05% BV 0.1% DES 0.1% HB 0.1% mBdD 0.05% DES 0.05% AUC (%/Control) 0 20 40 60 80 100 120 <50%50-70 %70-80%>80% *** *** *** *** *** ** Figure 3. Classification of corticosteroids using the estimation of the amount of released histamine (AUC) during the period of 60 min of microdialysis on excised skins in the presence of corticosteroids. **p < 0.01 and ***p < 0.001 versus control. loped a microdialysis technique allowing the measure- ment of histamine release from intact human skin mast cells ex vivo [12] using intradermal injection of anti-IgE. The kinetics of histamine release in the skin ex vivo by anti-IgE showed a maximum peak around 15 minutes of microdialysis comparable to that obtained in the present study. So this microdialysis technique made it possible to test the potency of several topical corticosteroids on ex Copyright © 2013 SciRes. JCDSA 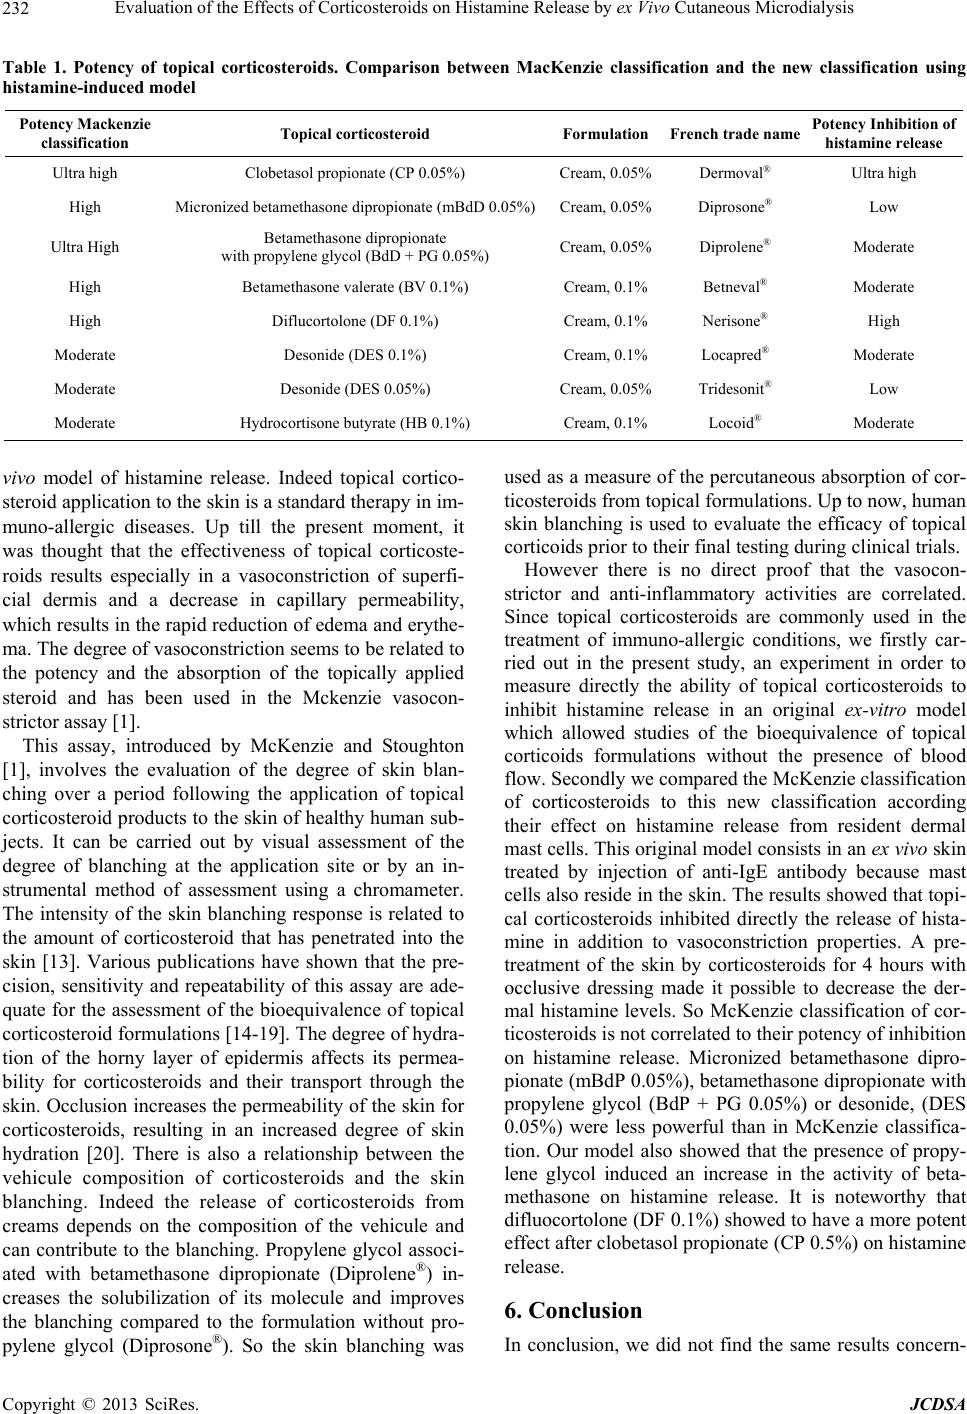 Evaluation of the Effects of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis 232 Table 1. Potency of topical corticosteroids. Comparison between MacKenzie classification and the new classification using histamine-induced model Potency Mackenzie classification Topical corticosteroid Formulation French trade name Potency Inhibition of histamine release Ultra high Clobetasol propionate (C P 0.05%) Cream, 0.05%Dermoval® Ultra high High Micronized betamethasone dipropionate (mBdD 0.05%)Cream, 0.05%Diprosone® Low Ultra High Betamethasone d ipropionate with propylene glycol (BdD + PG 0.05%) Cream, 0.05%Diprolene® Moderate High Betamethasone v alerate (BV 0.1%) Cream, 0.1% Betneval® Moderate High Diflucortolone (D F 0.1%) Cream, 0.1% Neris one® High Moderate Desonide (DES 0.1%) Cream, 0.1% Locapred® Moderate Moderate Desonide (DES 0.05%) Cream, 0.05%Tridesonit® Low Moderate Hydrocortisone butyrate (HB 0.1%) Cream, 0.1% Locoid® Moderate vivo model of histamine release. Indeed topical cortico- ster o id ap p li cat io n to the sk in i s a s ta nd ar d th er ap y in im- muno-allergic diseases. Up till the present moment, it was thought that the effectiveness of topical corticoste- roids results especially in a vasoconstriction of superfi- cial dermis and a decrease in capillary permeability, which results in the rapid reduction of edema and erythe- ma. The degree of vasoconstriction seems to be related to the potency and the absorption of the topically applied steroid and has been used in the Mckenzie vasocon- strictor assay [1]. This assay, introduced by McKenzie and Stoughton [1], involves the evaluation of the degree of skin blan- ching over a period following the application of topical corticosteroid prod ucts to the skin of healthy human sub- jects. It can be carried out by visual assessment of the degree of blanching at the application site or by an in- strumental method of assessment using a chromameter. The intensity of the skin blanching response is related to the amount of corticosteroid that has penetrated into the skin [13]. Various publications have shown that the pre- cision, sensitivity and repeatability of this assay are ade- quate for the assessment of the bioequivalence of topical corticosteroid formulations [14-19]. The degree of hydra- tion of the horny layer of epidermis affects its permea- bility for corticosteroids and their transport through the skin. Occlusion increases the permeability of th e skin for corticosteroids, resulting in an increased degree of skin hydration [20]. There is also a relationship between the vehicule composition of corticosteroids and the skin blanching. Indeed the release of corticosteroids from creams depends on the composition of the vehicule and can contribute to the blanching. Propylene glycol associ- ated with betamethasone dipropionate (Diprolene®) in- creases the solubilization of its molecule and improves the blanching compared to the formulation without pro- pylene glycol (Diprosone®). So the skin blanching was used a s a measur e of the per cutaneous abso rption of cor- ticosteroids from topical formulations. Up to now, human skin blanching is used to evaluate the efficacy of topical corticoids prior to their final testing during clinical trials. However there is no direct proof that the vasocon- strictor and anti-inflammatory activities are correlated. Since topical corticosteroids are commonly used in the treatment of immuno-allergic conditions, we firstly car- ried out in the present study, an experiment in order to measure directly the ability of topical corticosteroids to inhibit histamine release in an original ex-vitro model which allowed studies of the bioequivalence of topical corticoids formulations without the presence of blood flow. Secondly we compared the McKenzie classification of corticosteroids to this new classification according their effect on histamine release from resident dermal mast cells. This original model consists in an ex vivo skin treated by injection of anti-IgE antibody because mast cells also reside in the skin. Th e results showed that topi- cal corticosteroids inhibited directly the release of hista- mine in addition to vasoconstriction properties. A pre- treatment of the skin by corticosteroids for 4 hours with occlusive dressing made it possible to decrease the der- mal histamine levels. So McKenzie classification of cor- ticosteroids is not correlated to their potency of inhibition on histamine release. Micronized betamethasone dipro- pionate (mBdP 0.05%), betamethasone dipropionate with propylene glycol (BdP + PG 0.05%) or desonide, (DES 0.05%) were less powerful than in McKenzie classifica- tion. Our model also showed that the presence of propy- lene glycol induced an increase in the activity of beta- methasone on histamine release. It is noteworthy that difluocortolone (DF 0.1%) showed to have a more potent effect after clobetasol propionate (CP 0.5%) on histamine release. 6. Conclusion In conclusion, we did not find the same results concern- Copyright © 2013 SciRes. JCDSA  Evaluation of the Effects of Corticosteroids on Histamine Release by ex Vivo Cutaneous Microdialysis 233 ing the potency of corticosteroids according to MacKen- zie classification and the inhibition of histamine release. These results show us that a new classification of the po- tency of corticosteroids should be established to treat correctly the patients according to the origin of the ob- served disturbances. These results invite us to consider the power of topical corticosteroids differently depending on their target action (anti-allergic, anti-inflammatory...). New ex vivo models should be developed in order to ob- serve the direct effects of corticosteroids on the release of inflammatory mediators. The method, which we have de- veloped, should lead to the study of clinical disease mo- dels for immuno-allergic clinical validation. REFERENCES [1] A. W. MacKenzie and R. B. Stoughton, “A Method for Comparing Percutaneous Absorption of Steroids,” Archi- ves of Dermatology, Vol. 86, No. 11, 1962, pp. 608-610. doi:10.1001/archderm.1962.01590110044005 [2] A. W. McKenzie, “Percutaneous Absorption of Steroids,” Archives of Dermatology, Vol. 86, No. 11, 1962, pp. 611- 614. doi:10.1001/archderm.1962.01590110047006 [3] S. Wiedersberg, C. S. Leopold and R. H. Guy, “Bioavai- lability and Bioequivalence of Topical Glucocorticoids,” European Journal of Pharmaceutics and Biopharmaceu- tics, Vol. 68, No. 3, 2008, pp. 453-466. doi:10.1016/j.ejpb.2007.08.007 [4] Y. Narkar, “Bioequivalence for Topical Products—An Update,” Pharmaceutical Research, Vol. 27, No. 12, 2010, pp. 2590-2601. doi:10.1007/s11095-010-0250-3 [5] Organisation for Economic Co-operation and Develop- ment (OECD), “Test Guideline 427: In Vitro Method,” Paris, 2004. [6] T. J. Franz, P. A. Lehman and S. G. Raney, “Use of Ex- cised Human Skin to Assess the Bioequivalence of To- pical Products,” Skin Pharmacology and Physiology, Vol. 22, No. 5, 2009, pp. 276-286. doi:10.1159/000235828 [7] A. Le Quellec, S. Dupin, P. Genissel, S. Saivin, B. Marc- hand and J. P. M. Houin, “Microdialysis Probes Calibra- tion: Gradient and Tissue Dependent Changes in No Flux and Reverse Dialysis Methods,” Journal of Pharmaco- ogical and Toxicological Methods, Vol. 33, No. 1, 1995, pp. 11-16. doi:10.1016/1056-8719(94)00049-A [8] N. Leveque, S. Makki, J. Hadgraft and P. Humbert, “Comparison of Franz Cells and Microdialysis for As- sessing Salicylic Penetration through Human Skin,” Inter- national Journal of Pharmaceutics, Vol. 269, No. 2, 2004, pp. 323-328. doi:10.1016/j.ijpharm.2003.09.012 [9] I. Brody, “Mast Cell Degranulation in the Evolution of Acute Eruptive Guttate Psoriasis Vulgaris,” Journal of In- vestigative Dermatology, Vol. 82, No. 5, 1984, pp. 460- 464. doi:10.1111/1523-1747.ep12260955 [10] A. L. Krogstad, G. Lonnroth, B. F. G. Larson and B. G. Wallin, “Nerve-Induced Histamine Release Is of Little Importance in Psoriatic Skin,” British Journal of Dermat- ology, Vol. 139, No. 5, 1998, pp. 403-409. doi:10.1046/j.1365-2133.1998.02402.x [11] T. Ishizaka, D. H. Conrad, T. F. Huff, D. D. Metcalfe, R. L. Stevens and R. A. Lewis, “Unique Features of Human Basophilic Granulocytes Developed in in Vitro Culture,” International Archives of Allergy and Applied Immun- ology, Vol. 77, No. 1-2, 1985, pp. 137-143. doi:10.1159/000233768 [12] L. J. Petersen, K. Brasso, M. Pryds and P. S. Skov, “His- tamine Release in Intact Human Skin by Monocyte Che- moattractant Factor-1, RANTES, Macrophage Inflamma- tory Protein-1 Alpha, Stem Cell Factor, Anti-IgE, and Co- deine as Determined by an ex Vivo Skin Microdialysis Technique,” Journal of Allergy and Clinical Immunology, Vol. 98, No. 4, 1996, pp. 790-796. doi:10.1016/S0091-6749(96)70128-8 [13] L. K. Pershing, B. S. Silver, G. G. Krueger, V. P. Shah and J. P. Skelly, “Feasibility of Measuring the Bioavai- lability of Topical Betamethasone Dipropionate in Com- mercial Formulations Using Drug Content in Skin and a Blanching Bioassay,” Pharmaceutical Research, Vol. 9, No. 1, 1992, pp. 45-51. doi:10.1023/A:1018975626210 [14] B. W. Barry and R. Woodford, “Activity and Bioavai- lability of Topical Corticosteroids: In Vivo/In Vitro Cor- relations for the Vasoconstrictor Test,” Journal of Clini- cal Pharmacol ogy, Vol. 3, No. 1, 1978, pp. 43-65. [15] K. H. Burdick, “Corticosteroid Bioavailability Assays: Correlation with a Clinical Study,” Acta Dermato-Vene- reologica: Supplement (Stockholm), Vol. 52, No. 67, 197 1, pp. 19-23. [16] B. W. Barry, “Bioavailability of Topical Steroids,” Der- matologica, Vol. 152, Suppl. 1, 1976, pp. 47-65. doi:10.1159/000257866 [17] G. L. Coleman, I. Kanfer and J. M. Haigh, “Comparative Blanching Activities of Proprietary Diflucortolone Vale- rate Topical Prepa rations,” Dermatologica, Vol. 156, No. 4, 1978, pp. 224-230. doi:10.1159/000250920 [18] E. Meyer, A. D. Magnus, J. M. Haigh and I. Kanfer, “Comparison of the Blanching Activities of Dermovate, Betnovate and Eumovate Creams and Ointments,” Inter- national Journal of Pharmaceutics, Vol. 41, No. 1, 1988, pp. 63-66. doi:10.1016/0378-5173(88)90136-6 [19] E. W. Smith, E. Meyer, J. M. Haigh and H. I. Maibach, “The Human Skin Blanching Assay as an Indicator of To- pical Corticosteroid Bioavailability and Potency: An Up- date,” In: R. L. Bronaugh and H. I. Maibach, Eds., Per- cutaneous Absorption: Mechanisms, Methodology and Drug Delivery, 2nd Edition, Marcel Dekker, Inc., New York, 1989, pp. 443-460. [20] J. M. Haigh and L. Kanfer, “Assessment of Topical Cor- ticosteroid Preparations: The Human Skin Blanching As- say,” International Journal of Pharmaceutics, Vol. 19, No. 3, 1984, pp. 245-262. doi:10.1016/0378-5173(84)90055-3 Copyright © 2013 SciRes. JCDSA |