

Paper Menu >>
Journal Menu >>
 World Journal of Cardiovascular Diseases, 2013, 3, 377-379 WJCD http://dx.doi.org/10.4236/wjcd.2013.35058 Published Online August 2013 (http://www.scirp.org/journal/wjcd/) Unusual treatment of postoperative bleeding after cardiac surgery José Rubio-Alvarez1*, Juan Sierra-Quiroga1, Belén Adrio-Nazar1, Laura Reija López1, Ángela Granda Bauza1, Carola Rubio Taboada2, Jose Manuel Martinez-Cereijo1 1Department of Cardiac Surgery, Universitary Hospital Santiago de Compostela, Santiago, Spain 2Department of Vascular Surgery, Universitary Hospital of Elche, Alicante, Spain Email: *[email protected] Received 15 June 2013; revised 20 July 2013; accepted 1 August 2013 Copyright © 2013 José Rubio-Alvarez et al. This is an open access article distributed under the Creative Commons Attribution Li- cense, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT A young patient was presented to the emergency de- partment with chest pain and palpitations. A tran- sthoracic echocardiogram showed a right atrial mass. Coronary angiography showed a right coronary ar- tery with collateral circulation to a large mass. The tumor could only be partially resected and the patient experienced persistent postoperative bleeding. We performed a new right coronary artery angiography which showed an important free extravasation of contrast into the pericardium through the collateral circulation. Using covered stents, the bleeding was controlled. The pathological examination performed later revealed a primary cardiac angiosarcoma. After asympto m-free survival of 14 month s the patien t pre- sented bone metastases. Keywords: Angiosarcoma; Coronary Stenting; Postoperative Bleeding 1. INTRODUCTION Primary cardiac malignant tumors are very uncommon and about 75% are sarcomas [1]. Although rare, angio- sarcomas are the most common primary malignant neo- plasms of the heart and are very aggressive and locally invasive. These tumors are highly vascularized and are often are actively bleeding into the pericardium. Since the introduction of percutaneous coronary inter- vention (PCI) in 197 7, it is increasingly used not only in simple coronary lesions, but also in complex coronary anatomies. Coronary perforation is a rare but serious complication of PCI with the occurrence of important bleeding into the pericardium. However, this complica- tion can be tackled successfully with covered stents [2]. We describe the case of a 50-year-old man with non- metastatic primary right atrial (RA) angiosarcoma, who underwent surgical excision of the tumor and recon- struction of the RA with a bovine pericardial patch. The tumour could only be partially resected and the patient experienced persistent postoperative bleeding through the collateral circulation from the right coronary artery, which was controlled using covered stents. After a sym- ptom-free survival of 12 months, the patient presented bone metastases. 2. CASE REPORT A 50-year-old previously healthy male visited emergency service because of palpitations and left chest pain. A chest X-ray showed enlargement of the RA border an d an electrocardiogram showed normal sinus rhythm with a heart rate of 87 beats per minute. A transthoracic echo- cardiogram was performed and detected a RA mass (50 × 45 mm) that had infiltrated the free wall of and protruded into the RA (Figure 1(A)). Left ventricular function was normal and there were no valvular abnormalities. For further evaluation of the RA mass magnetic resonance imaging was performed (Figure 1(B)). This exploration also showed a large eccentric tumor (64 × 54 × 53 mm) in the RA free wall, protruding into the right atrium. The tumor extended into the right atrioventricular groove, but did not involve the right ventricle, or the annulus of the tricuspid valve. Coronary angiography showed a right coronary artery with collateral circulation to a large mass. Surgery was performed under standard extracorporeal circulation with selective cannulation of both cava veins and the ascending aorta. The RA was excised (Figure 2), but the tumor could only be partially resected because it extended into the free wall of the right ventricle and tri- cuspid valve annulus. The RA was reconstructed using bovine pericardium. After declamping massive bleeding was present from the arterial sinuses of the cut edge of *Corresponding a uthor. OPEN ACCESS 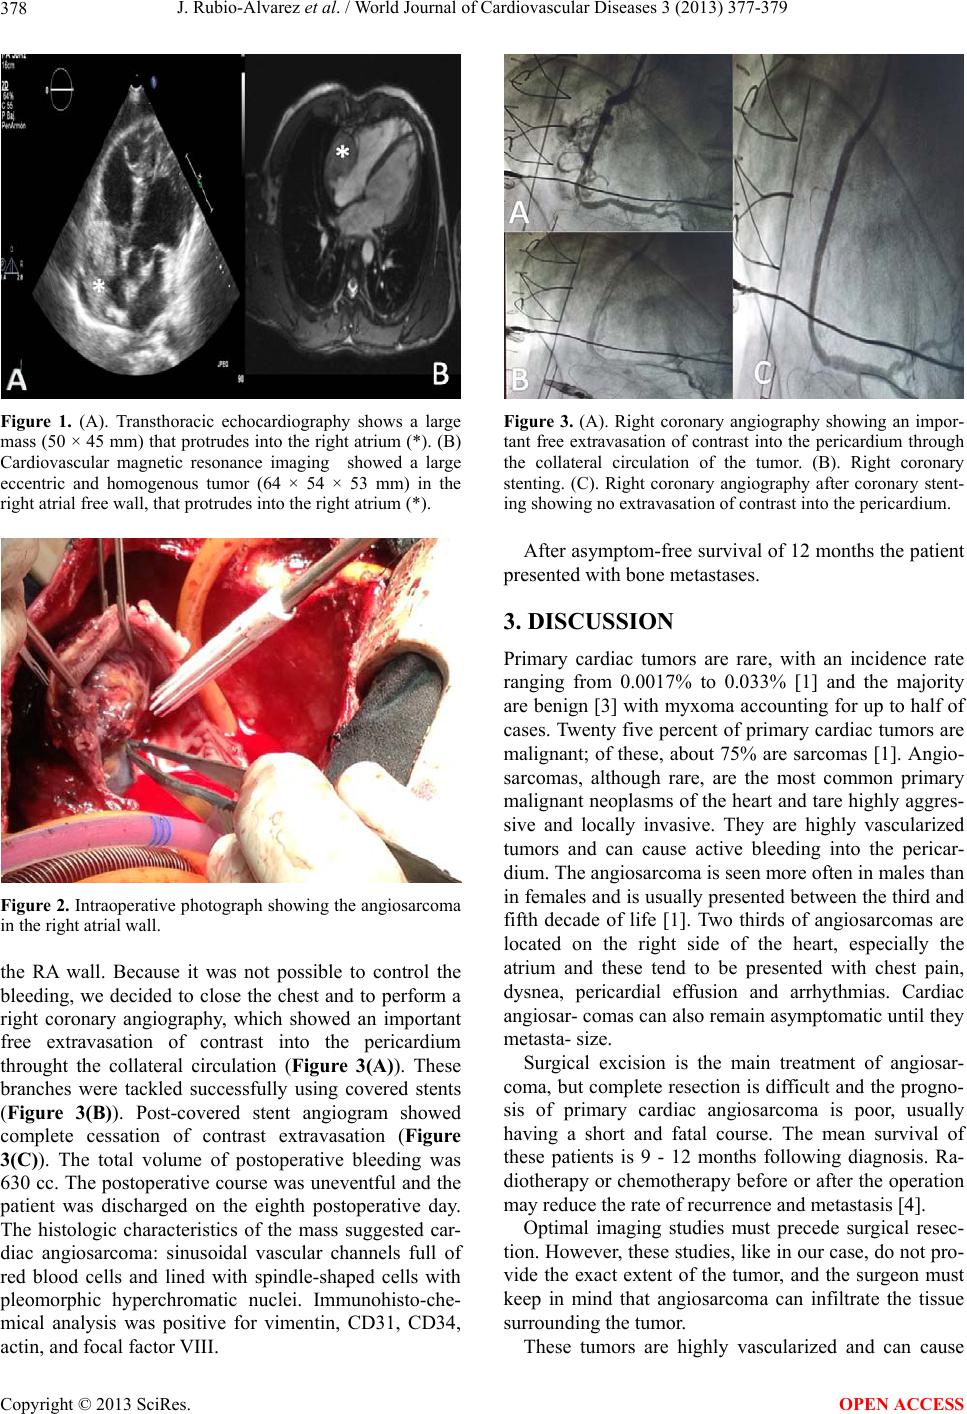 J. Rubio-Alvarez et al. / World Journal of Cardiovascular Diseases 3 (2013) 377-379 378 Figure 1. (A). Transthoracic echocardiography shows a large mass (50 × 45 mm) that protrudes into the right atrium (*). (B) Cardiovascular magnetic resonance imaging showed a large eccentric and homogenous tumor (64 × 54 × 53 mm) in the right atrial free wall, that protrudes into the right atrium (*). Figure 2. Intraoperative photograph showing the angiosarcoma in the right atrial wall. the RA wall. Because it was not possible to control the bleeding, we decided to close the chest and to perform a right coronary angiography, which showed an important free extravasation of contrast into the pericardium throught the collateral circulation (Figure 3(A)). These branches were tackled successfully using covered stents (Figure 3(B)). Post-covered stent angiogram showed complete cessation of contrast extravasation (Figure 3(C)). The total volume of postoperative bleeding was 630 cc. The postoperative course was uneventful and the patient was discharged on the eighth postoperative day. The histologic characteristics of the mass suggested car- diac angiosarcoma: sinusoidal vascular channels full of red blood cells and lined with spindle-shaped cells with pleomorphic hyperchromatic nuclei. Immunohisto-che- mical analysis was positive for vimentin, CD31, CD34, actin, and focal factor VIII. Figure 3. (A). Right coronary angiography showing an impor- tant free extravasation of contrast into the pericardium through the collateral circulation of the tumor. (B). Right coronary stenting. (C). Right coronary angiography after coronary stent- ing showing no extravasation of contrast into the pericardium. After asymptom-free survival of 12 months the patient presented with bone metastases. 3. DISCUSSION Primary cardiac tumors are rare, with an incidence rate ranging from 0.0017% to 0.033% [1] and the majority are benign [3] with myxoma accounting for up to half of cases. Twenty five percent of primary cardiac tumors are malignant; of these, about 75% are sarcomas [1]. Angio- sarcomas, although rare, are the most common primary malignant neoplasms of the heart and tare highly aggres- sive and locally invasive. They are highly vascularized tumors and can cause active bleeding into the pericar- dium. The angiosarcoma is seen more often in males than in females and is usually presented between the third and fifth decade of life [1]. Two thirds of angiosarcomas are located on the right side of the heart, especially the atrium and these tend to be presented with chest pain, dysnea, pericardial effusion and arrhythmias. Cardiac angiosar- comas can also remain asymptomatic until they metasta- size. Surgical excision is the main treatment of angiosar- coma, but complete resection is difficult and the progno- sis of primary cardiac angiosarcoma is poor, usually having a short and fatal course. The mean survival of these patients is 9 - 12 months following diagnosis. Ra- diotherapy or chemotherapy before or after the operation may reduce the rate of recurrence and metastasis [4]. Optimal imaging studies must precede surgical resec- tion. However, these studies, like in our case, do not pro- vide the exact extent of the tumor, and the surgeon must keep in mind that angiosarcoma can infiltrate the tissue surrounding the tumor. These tumors are highly vascularized and can cause Copyright © 2013 SciRes. OPEN ACCESS  J. Rubio-Alvarez et al. / World Journal of Cardiovascular Diseases 3 (2013) 377-379 Copyright © 2013 SciRes. OPEN ACCESS 379 active bleeding into the pericardium. In our case, the pre- operative coronary angiography showed an atrial mass with a vascular supply from the right coronary artery. When we removed the clamp, massive bleeding was presented from the arterial sinuses of the cut edge of the RA wall. Because it was not possible to control the bleeding, we decided to close the chest and perform a right coronary angiography which revealed an important free extravasation of contrast into the pericardium through the collateral circulation. These branches were tackled successfully with covered stents. The post-cove- red stent angiogram showed complete cessation of con- trast extravasation. PCI is widely utilized in the treatment of symptomatic coronary artery disease. Coronary perforation is a rare complication of PCI, but covered stents effectively seal coronary perforations when this occurs, especially when the perforation involv es the proximal or mid-seg ments of the artery where delivery of these devices is relatively easy. Briguori, et al. [5] reported a 91% successful rate of closure of Types I and II perforations with PTFE-cov- ered stents and a significantly lower incidence of cardiac tamponade or need for emergency surgery. In our case, the use of covered stents was the solution for postopera- tive bleeding. REFERENCES [1] Reardon, M.J. and Smythe, W.R. (2003) Cardiac Neo- plasms. In: Cohn, L.H. and Edmunds, Jr. L.H., Eds., Car- diac Surgery in the Adult, McGraw-Hill, New York, 1373-1400. [2] Rogers, J.H. and Lasala, J.M. (2004) Coronary artery dissection and perforation complicating percutaneous co- ronary intervention. Journal of Invasive Cardiology, 16, 493-499. [3] McAllister, H.A. and Fenoglio, J.J. (1978) Tumors of the cardiovascular system. In: Hartmann, W.H. Ed., Atlas of Tumor Pathology, 2nd Series, Fascicle 15, Armed Forces Institute of Pathology, Washington DC, 81. [4] Young, R.J., Brown, N.J., Reed, M.W., Hughes, D. and Woll, P.J. (2010) Angiosarcoma. The Lancet Oncology, 11, 983-991. doi:10.1016/S1470-2045(10)70023-1 [5] Briguori, C., Nishida, T., Anzuini, A., Di Mario, C., Grube, E. and Colombo, A. (2000) Emergency polytetra- fluoethylene-covered stent implantation to treat coronary ruptures. Circulation, 102, 3028-3031. doi:10.1161/01.CIR.102.25.3028 |