

Paper Menu >>
Journal Menu >>
 Vol.2, No.3, 208-210 (2013) Case Reports in Clinical Medicine http://dx.doi.org/10.4236/crcm.2013.23056 Tietze’s Syndrome in the emergency department: A rare etiology of atraumatic chest pain Lee Grodin1*, Gino Farina2 1Department of Emergency Medicine, State University of New York, Downstate Medica l Center, New York, USA; *Corresponding Author: [email protected] 2Department of Emergency Medicine, Long Island Jewish Medical Center, New York, USA Received 29 March 2013; revised 30 April 2013; accepted 15 May 2013 Copyright © 2013 Lee Grodin, Gino Farina. This is an open access article distributed under the Creative Commons Attribution Li- cense, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. ABSTRACT Tietze’s Syndrome is an uncommon disorder that presents with painful, tender, non-suppura- tive swelling of the anterior chest wall. We report a case of a female patient who presented to the emergency department with a chief complaint of atraumatic chest pain and swelling of the ante- rior chest wall. After a thorough history and physical examination, as well as basic labora- tory tests and chest radiography, she was di- agnosed with Tietze’s Syndrome. The expedient accurate diagnosis of Tietze’s Syndrome is im- portant for the physical and emotional well-be- ing of a patient, and avoids overlooking more dangerous pathologies. T ietze’s Syndrome needs to be considered in the differential diagnosis of a patient presenting with spontaneous swelling of the anterior ches t. Keywords: Tietze’s Syndrome; Atraumatic Chest Pain 1. INTRODUCTION Chest pain is a frequent chief complaint in emergency departments, and the underlying pathology ranges from completely benign to imminently life-threatening. Among the myriad possible etiologies are the confounding mus- culoskeletal disorders, which account for 50% of benign causes [1]. While frequently discussed and included in differential diagnoses, they are often inappropriately con- solidated and misunderstood. Tietze’s Syndrome (which has also been referred to as Costosternal Syndrome, An- terior Chest Wall Syndrome, Parasternal Chondrodynia, Thoracochondalg ia, Chondrop athia Tubero se, and Costo- chondral Junction Syndrome) is an uncommon muscu- loskeletal pathology, which was first described in 1921 by Alexander Tietze [2-4]. The National Institutes of Health lists it as a rare disease, indicating the limited available information about the syndrome as well as its possible rari t y [5]. While it is a benign, self-limited, chronic pain condi- tion characterized by a localized swelling involving usu- ally the second or third ribs, unrecognized it can mimic malignancies, acute coronary syndrome, pneumonia, or trauma [6,7]. The emotional and physical relief of an accurate diagnosis is then delayed and the patient can undergo an emotionally stressful and costly evaluation for more serious disease [7,8]. The pain can be tremen- dous. We present a young female patient with a classic case of Tietze’s Syndrome. The diagnostic difficulty lies in part to the absence of confirmatory laboratory or im- aging tests, thus leaving the clinician reliant on the pa- tient’s history and presentation. 2. CASE PRESENTATION A 29 years old otherwise healthy woman presented with localized right sided chest pain for approximately three days and focal swelling over the same area for one to two days. She described the pain as “aching,” local- ized to the right side of her anterior chest, and radiating to her back ipsilaterally. It was pleuritic and associated with subjective shortness of breath, which she attributed to her pain. It was minimally responsive to ibuprofen. The swelling was very firm, tender, and had appeared spontaneously. She denied trauma, recent travel, or illnesses. She de- nied fever, chills, malaise, or weight loss. She works as a visual merchandiser but has had no change in her level of physical activity. One year ago, the patient reported she was diagnosed with Lyme Disease after presenting with malaise and Bell’s Palsy. After confirmatory serological testing, she completed a course of antibiotics. At that time she also Copyright © 2013 SciRes. OPEN ACCESS 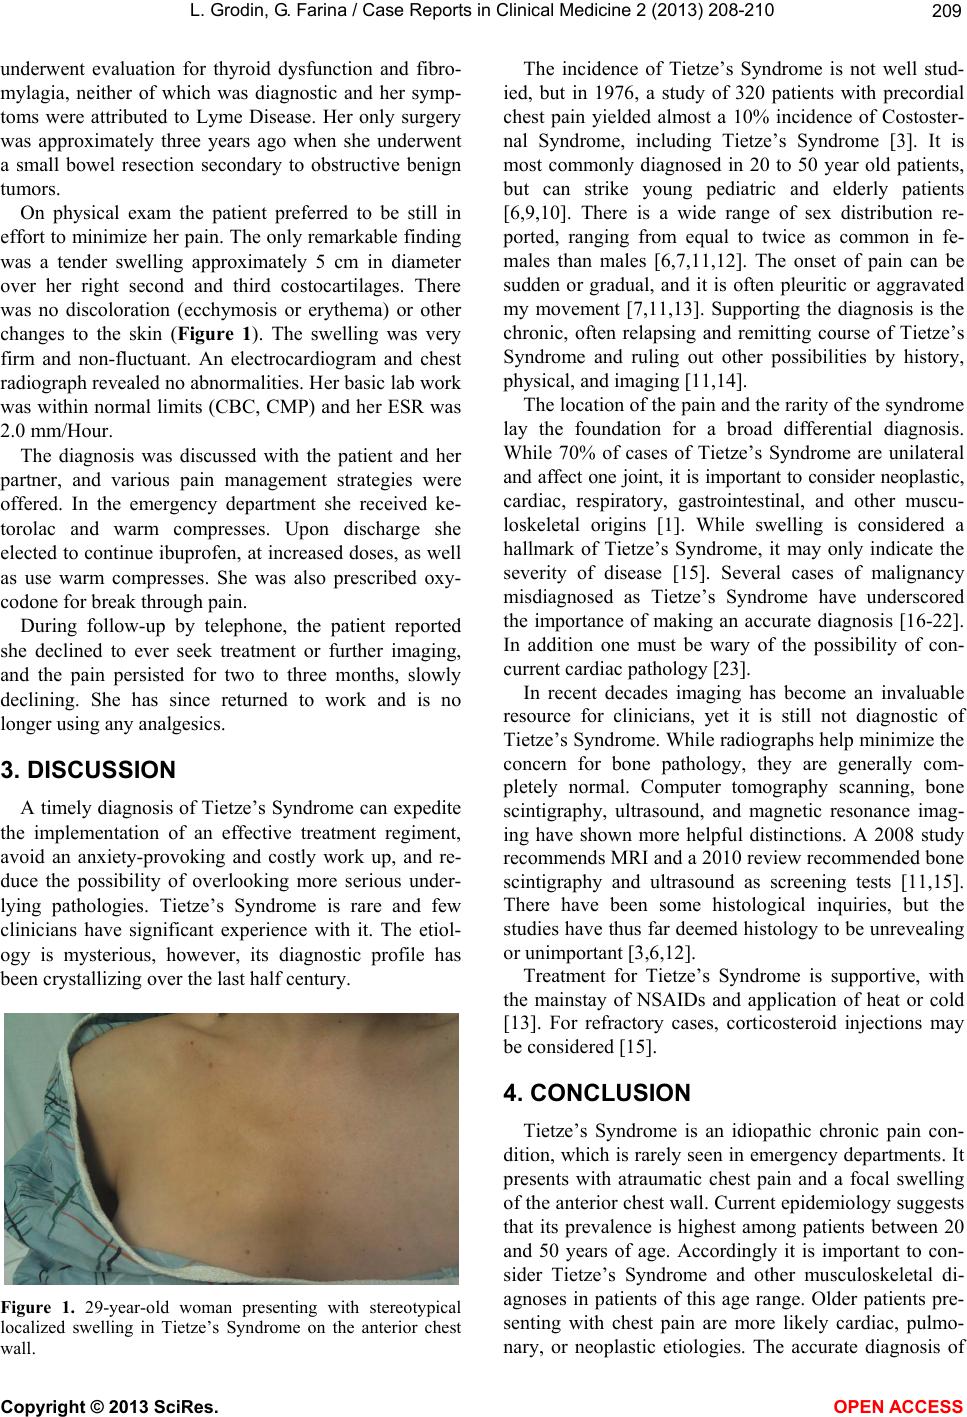 L. Grodin, G. Farina / Case Reports in Clinical Medicin e 2 (2013) 208-210 209 underwent evaluation for thyroid dysfunction and fibro- mylagia, neither of which was diagnostic and her symp- toms were attributed to Lyme Disease. Her only surgery was approximately three years ago when she underwent a small bowel resection secondary to obstructive benign tumors. On physical exam the patient preferred to be still in effort to minimize her pain. The only remarkable finding was a tender swelling approximately 5 cm in diameter over her right second and third costocartilages. There was no discoloration (ecchymosis or erythema) or other changes to the skin (Figure 1). The swelling was very firm and non-fluctuant. An electrocardiogram and chest radiograph revealed no abno rmali ties. H er basic lab wo rk was within normal limits (CBC, CMP) and her ESR was 2.0 mm/Hour. The diagnosis was discussed with the patient and her partner, and various pain management strategies were offered. In the emergency department she received ke- torolac and warm compresses. Upon discharge she elected to continue ibuprofen, at increased doses, as well as use warm compresses. She was also prescribed oxy- codone for break through pain. During follow-up by telephone, the patient reported she declined to ever seek treatment or further imaging, and the pain persisted for two to three months, slowly declining. She has since returned to work and is no longer using any analgesics. 3. DISCUSSION A timely diagnosis of Tietze’s Synd rome can expedite the implementation of an effective treatment regiment, avoid an anxiety-provoking and costly work up, and re- duce the possibility of overlooking more serious under- lying pathologies. Tietze’s Syndrome is rare and few clinicians have significant experience with it. The etiol- ogy is mysterious, however, its diagnostic profile has been crystallizing over the last h alf century. Figure 1. 29-year-old woman presenting with stereotypical localized swelling in Tietze’s Syndrome on the anterior chest wall. The incidence of Tietze’s Syndrome is not well stud- ied, but in 1976, a study of 320 patients with precordial chest pain yielded almost a 10% incidence of Costoster- nal Syndrome, including Tietze’s Syndrome [3]. It is most commonly diagnosed in 20 to 50 year old patients, but can strike young pediatric and elderly patients [6,9,10]. There is a wide range of sex distribution re- ported, ranging from equal to twice as common in fe- males than males [6,7,11,12]. The onset of pain can be sudden or gradual, and it is often pleuritic or aggravated my movement [7,11,13]. Supporting the diagnosis is the chronic, often relapsing and remitting course of Tietze’s Syndrome and ruling out other possibilities by history, physical, and imaging [11,14]. The location of the pain and the rarity of the syndro me lay the foundation for a broad differential diagnosis. While 70% of cases of Tietze’s Syndrome are unilateral and affect one joint, it is important to consider neoplastic, cardiac, respiratory, gastrointestinal, and other muscu- loskeletal origins [1]. While swelling is considered a hallmark of Tietze’s Syndrome, it may only indicate the severity of disease [15]. Several cases of malignancy misdiagnosed as Tietze’s Syndrome have underscored the importance of making an accurate diagnosis [16-22]. In addition one must be wary of the possibility of con- current cardiac pathology [23]. In recent decades imaging has become an invaluable resource for clinicians, yet it is still not diagnostic of Tietze’s Syndrome. While radiographs help minimize the concern for bone pathology, they are generally com- pletely normal. Computer tomography scanning, bone scintigraphy, ultrasound, and magnetic resonance imag- ing have shown more helpful distinctions. A 2008 study recommends MRI and a 2010 r ev iew recommen d ed bo ne scintigraphy and ultrasound as screening tests [11,15]. There have been some histological inquiries, but the studies have thus far deemed histology to be unrevealing or unimportant [3,6,12]. Treatment for Tietze’s Syndrome is supportive, with the mainstay of NSAIDs and application of heat or cold [13]. For refractory cases, corticosteroid injections may be considered [15]. 4. CONCLUSION Tietze’s Syndrome is an idiopathic chronic pain con- dition, which is rarely seen in emergency departments. It presents with atraumatic chest pain and a focal swelling of the anterior chest wall. Current epidemiology suggests that its prevalence is highest among patients between 20 and 50 years of age. Accordingly it is important to con- sider Tietze’s Syndrome and other musculoskeletal di- agnoses in patients of this age range. Older patients pre- senting with chest pain are more likely cardiac, pulmo- nary, or neoplastic etiologies. The accurate diagnosis of Copyright © 2013 SciRes. OPEN ACCESS  L. Grodin, G. Farina / Case Reports in Clinical Medicin e 2 (2013) 208-210 Copyright © 2013 SciRes. OPEN ACCESS 210 [11] Volterrani, L., et al. (2008) Magnetic resonance imagine in Tietze’s Syndrome. Clinical and Experimental Rheu- matology, 26, 848-853. Tietze’s Syndrome provides the best platform for pain management, reducing the time and cost of an unneces- sary work up for other conditions while not overlooking malignancies. It provides the patient with physical and emotional comfort. While a thorough history and physic- cal are essential for diagnosis, follow up is helpful to ensure the disease course is consistent with Tietze’s Syndrom e an d not suggestive of another pathology . [12] Landon, J. and Malpas, J.S. (1959) Tietze’s Syndrome. Annals of Rheumatic Disease, 18, 249-254. doi:10.1136/ard.18.3.249 [13] Semble, E.L. and Wise, C.M. (1988) Chest pain: A rheu- matologist’s perspective. Southern Medical Journal, 81, 64-68. doi:10.1097/00007611-198801000-00014 [14] Langford, C.A. and Mandell, B.F. (2012) Chapter 336. Arthritis associated with systemic disease, and other ar- thritides. In: Longo, D.L., et al., Harrison’s Principles of Internal Medicine, The MacGraw-Hill Companies, Inc., New York, 2858 -2859. REFERENCES [1] Gijsbers, E. and Knaap, S.F. (2011) Clinical presentation and chiropractic treatment of Tietze Syndrome: A 34-year-old female with left-sided chest pain. Journal of Chiropractic Medicine, 10, 60-63. doi:10.1016/j.jcm.2010.10.002 [15] Stochkendahl, M.J. and Christensen, H.W. (2010) Chest pain in focal musculoskeletal disorders. Medical Clinics of North America, 94, 259-273. doi:10.1016/j.mcna.2010.01.007 [2] Hiramuro-Shoji, F., Wirth, M.A. and Rockwood Jr., C. (2003) Atraumatic conditions of the sternoclavicular joint. Journal of Shoulder and Elbow Surgery, 12, 78-88. doi:10.1067/mse.2003.128566 [16] Fioravanti, A., Tofi, C., Volterrani, L. and Marcolongo, R. (2002) Malignant Lymphoma Presenting as Tietze’s Syn- drome. Arthritis and Rheumatism, 47, 229-230. doi:10.1002/art.10401 [3] Wolf, E. and Stern, S. (1976) Costosternal Syndrome: Its frequency and importance in differential diagnosis of coronary heart disease. Archives of Internal Medicine, 136, 189-191. doi:10.1001/archinte.1976.03630020043010 [17] Koren, W. and Shahar, A. (1998) Xiphodynia masking acute myocardial infarction: A diagnostic cul-de-sac. Jour- nal of Emergency Medicine, 16, 177-178. [18] Mathew, A.S., El-Haddad, G., Lilien, D.L. and Takalkar, A.M. (2008) Costosternal chondrodynia simulating re- current breast cancer unveiled by FDG PET. Clinical Nu- clear Medicine, 33, 330-332. doi:10.1097/RLU.0b013e31816a7a38 [4] Tietze, A. (1921) Über eine eigenartige häufung von fällen mit dystrophie der rippenknorpel. Berliner Kli- nische Woch enschrift, 58, 829-831. [5] Rare Diseases and Related Terms, National Institutes of Health (2013). http://rarediseases.info.nih.gov/RareDiseaseList.aspx?Pag eID=1. [19] Cocco, R., Galieni, P., Bellan, C. and Fioravanti, A. (1999) Ly mphomas presenting as Tietze’s Syndrome: A report of 4 clinical cases. Annali Italiani di Medicina Interna, 14, 118-123. [6] Aeschlimann, A. and Kahn, M.F. (1990) Tietze’s Syndro- me: A critical review. Clinical and Experimental Rheu- matology, 8, 407-412. [20] Jeon, I.H., Jeong, W.J., Yi, J.H., Kim, H.J. and Park, I.H. (2010) Non-Hodgkin’s lymphoma at the medial clavicular head mimicking Tietze’s Syndrome. Rheumatology In- ternational, 32, 2531-2534. doi:10.1007/s00296-010-1397-2 [7] Jelenko, C. and Cowan, G. (1977) Perichondritis (Tietze’s Syndrome) at the xiphisternal joint: A mimic of severe disease. Journal of the American College of Emergency Physicians, 6, 536-542. doi:10.1016/S0361-1124(77)80424-3 [21] De Filippo, M. et al. (2007) MRI findings of Tietze’s syndrome mimicking mediastinal malignancy on MDCT. European Journal of Radiology Extra, 65, 33-35. doi:10.1016/j.ejrex.2007.10.006 [8] Epstein, S.E., Gerber, L.H. and Borer, J.S. (1979) Chest wall syndrome: A common cause of unexplained cardiac pain. The Journal of the American Medical Association, 26, 2793-2797. doi:10.1001/jama.1979.03290520017017 [22] Krohn-Gimberghe, B., Kurzeja, R., Wagner, J. and Kaiser, H.E. (1999) Pleomorphic T-cell lymphoma with chon- dropathia tuberose; A case report and review. Anticancer Research, 19, 2221-2228. [9] Mukamel, M., Kornreich L., Horev, G., Zebria, A. and Mimouni, M. (1997) Tietze’s Syndrome in children and infants. Journal of Pediatrics, 131, 774-775. doi:10.1016/S0022-3476(97)70114-8 [23] Epstein, S.E., Gerber, L.H. and Borer, J.S. (1979) Chest wall syndrome: A common cause of unexplained cardiac pain. The Journal of the American Medical Association, 26, 2793-2797. doi:10.1001/jama.1979.03290520017017 [10] Pikning, J.M., De Boeck, H. Desprechins, B. and Ernst, C. (2003) Tietze’s Syndrome in a 2-year-old boy. Neder- lands Tijdschrift Geneeskunde, 43, 2134-2136. |