

Paper Menu >>
Journal Menu >>
 Advances in Computed Tomography, 2012, 1, 21-22 http://dx.doi.org/10.4236/act.2012.13005 Published Online December 2012 (http://www.SciRP.org/journal/act) Re-Sheathing the Scimitar Syndrome Michael Michail, Kaleab N. Asrress, Abhishek Joshi, John A. Giles, Muhammed Z. Khawaja, Eric T. McWilliams Department of Cardiology, Conquest Hospital, Hastings, UK Email: [email protected] Received November 10, 2012; revised December 12, 2012; accep te d Decemb er 20, 2012 ABSTRACT Scimitar Syndrome is a congenital condition resulting in anomalous pulmonary venous drainage from the lung into the inferior vena cava. It is often associated with cardiac and pu lmonary abnormalities, both which are determinan ts in the severity and timing of presentation . True incidence of this condition is un known and likely to be significantly underes- timated as many patients remain asymptomatic through adult life. The increase in availability and use of medical imag- ing suggests that more asymptomatic and subacute cases will be detected. The management in those with the delayed presentation of this co ndition is debated, however the mainstay of therapy remains medical. Keywords: Adult-Onset Scimitar Syndrome; Multidetector Computed Tomography 1. Case Report A fifty-year-old lady presented with progressive exer- tional dyspnoea in absence of significant past medical history. Clinical examination was normal. Twelve lead electrocardiograms showed non-specific changes. Bio- markers including full blood count, cardiac troponin-T, and D-dimers were normal. Plain chest radiograph showed abnormal vascular markings in the right lower zone suspicious of a scimitar vein (SV) (Figure 1(A)). 64-slice multidetector computed tomography showed partial anomalous pulmonary venous drainage of the en- tire right lung to the inferior vena cava (IVC) below the right atrial-IVC junction (Figures 1(B)-(D)), confirming scimitar syndrome (SS). Cardiac catheterisation con- firmed the presence of the SV, and found a left-to-right shunt with Qp:Qs of 2.1:1. 2. Scimitar Syndrome SS is a rare congenital abnormality, characterised by ano- malous pulmonary venous drainage of the right, or less frequently, the left lung, into the inferior vena cava. The true incidence is unknown. The syndrome is named after the Turkish sword “scimitar” describing the radiogra- phic appearance of the anomalous vein. SS has two distinct presentations. The “infant” form is associated with other congenital abnormalities and great- er mortality. Clinical features may include failure to thrive, tachypnoea, cardiac failure, recurrent chest infec- tions and cyanosis [1]. Medical therapy is used to allevi- ate symptoms in infants, however the presence of pul- monary hypertension warrants prompt surgical correc- tion. The second form presents in children and adults. Car- diac and pulmonary abnormalities are associated, the former more accountable for the severity of symptoms. Cardiac abnormalities include dextrocardia, atrial and ventricular septal defects, patent ductus arteriosus and pulmonary vein stenosis. Pulmonary abnormalities vary but commonly include right lung hypoplasia and pulmo- nary sequestration. In two thirds of patients, the SV pro- vides drainage for the entire right lung. Delayed presentation in the adult group is the result of fewer cardiopulmonary anomalies. Patients present with exertional dyspnoea and recurrent chest infections, more commonly involving the right lung. Electrocardiogram may find atrial fibrillation, right ventricular hypertrophy or right bundle branch block. Pulmonary function tests demonstrate mild deficits in vital capacity [2]. Co mputed tomography is increasingly used to provide 3D images to guide further treatment [3]. 3. Treatment The conventional indications for corrective surgery in adults with SS are a shunt of greater than 50% (a ratio of 2:1), or pulmonary sequestration with recurrent pulmo- nary infection. These indications arose from a small, sin- gle centre study (n = 6) [4]. Corrective surgery attempts to reduce left-to-right shunt by diverting the flow of SV into systemic circula- tion. Two main approaches have been used: First, re-im- pla n t a t io n of th e S V into the le ft atrium or, second, to use a baffle to redirect flow across the right atrium through C opyright © 2012 SciRes. ACT 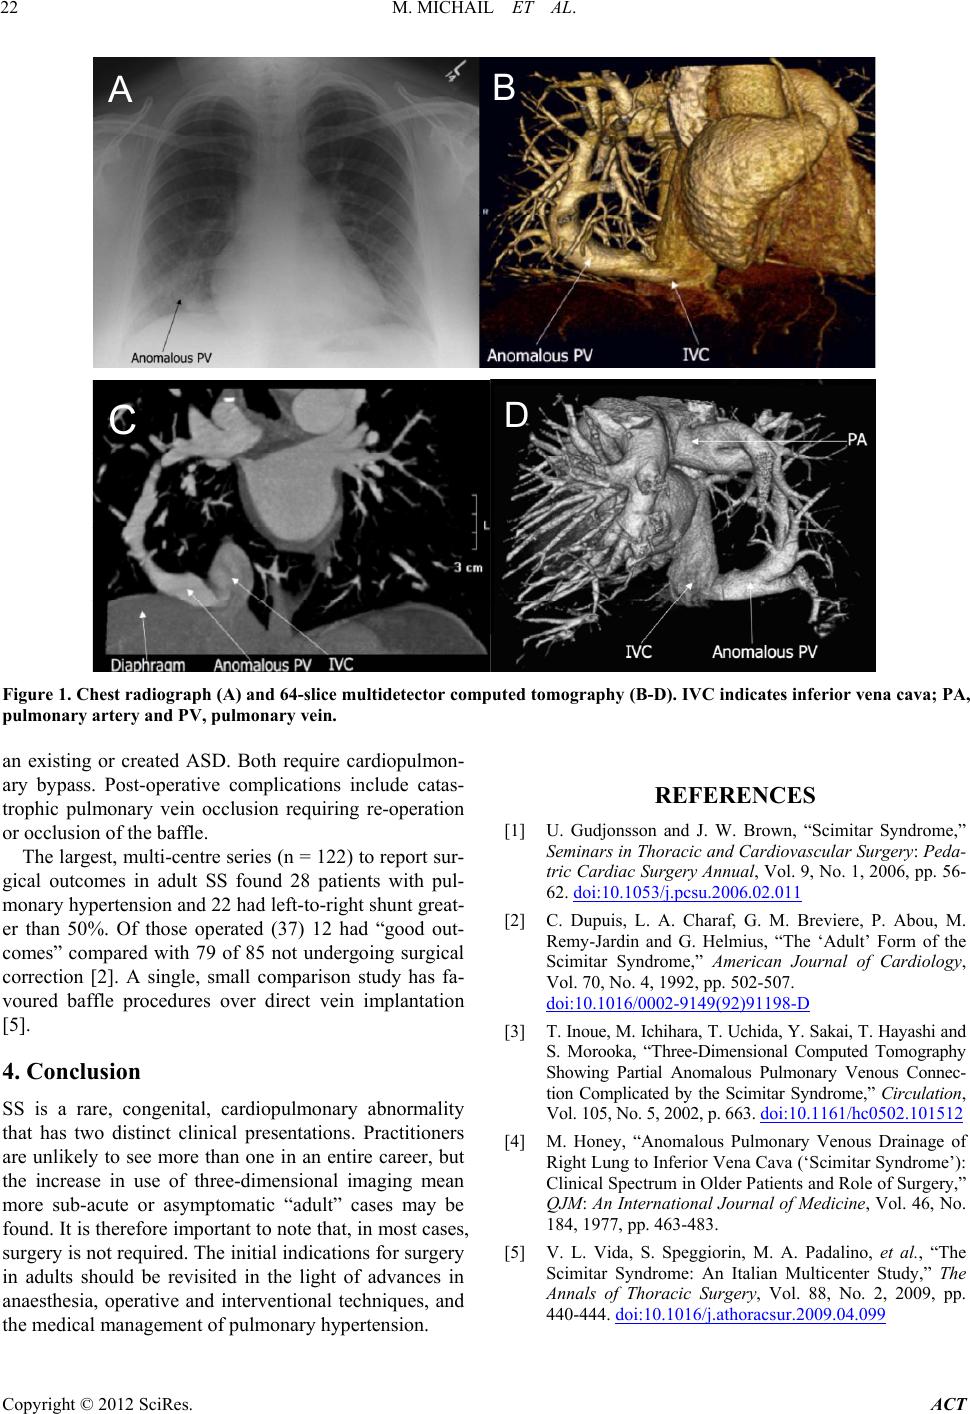 M. MICHAIL ET AL. 22 AB C D Figure 1. Chest radiograph (A) and 64-slice multidetector computed tomography (B-D). IVC indicates inferior vena cava; PA, pulmonary artery and PV, pulmonary ve in. an existing or created ASD. Both require cardiopulmon- ary bypass. Post-operative complications include catas- trophic pulmonary vein occlusion requiring re-operation or occlusion of the baffle. The largest, multi-centre series (n = 122) to report sur- gical outcomes in adult SS found 28 patients with pul- monary hypertension and 22 had left-to-right shunt great- er than 50%. Of those operated (37) 12 had “good out- comes” compared with 79 of 85 not undergoing surgical correction [2]. A single, small comparison study has fa- voured baffle procedures over direct vein implantation [5]. 4. Conclusion SS is a rare, congenital, cardiopulmonary abnormality that has two distinct clinical presentations. Practitioners are unlikely to see more than one in an entire career, but the increase in use of three-dimensional imaging mean more sub-acute or asymptomatic “adult” cases may be found. It is therefore importan t to note that, in most cases, surgery is not req uired. The initial in dications fo r surgery in adults should be revisited in the light of advances in anaesthesia, operative and interventional techniques, and he medical management of pulmonary hypertension. t REFERENCES [1] U. Gudjonsson and J. W. Brown, “Scimitar Syndrome,” Seminars in Thoracic and Cardiovascular Surgery: Peda- tric Cardiac Surgery Annual, Vol. 9, No. 1, 2006, pp. 56- 62. doi:10.1053/j.pcsu.2006.02.011 [2] C. Dupuis, L. A. Charaf, G. M. Breviere, P. Abou, M. Remy-Jardin and G. Helmius, “The ‘Adult’ Form of the Scimitar Syndrome,” American Journal of Cardiology, Vol. 70, No. 4, 1992, pp. 502-507. doi:10.1016/0002-9149(92)91198-D [3] T. Inoue, M. Ichihara, T. Uchida, Y. Sakai, T. Hayashi and S. Morooka, “Three-Dimensional Computed Tomography Showing Partial Anomalous Pulmonary Venous Connec- tion Complicated by the Scimitar Syndrome,” Circulation, Vol. 105, No. 5, 2002, p. 663. doi:10.1161/hc0502.101512 [4] M. Honey, “Anomalous Pulmonary Venous Drainage of Right Lung to Inferior Vena Cava (‘Scimitar Syndrome’): Clinical Spectrum in Older Patients and Role of Surgery,” QJM: An International Journal of Medicine, Vol. 46, No. 184, 1977, pp. 463-483. [5] V. L. Vida, S. Speggiorin, M. A. Padalino, et al., “The Scimitar Syndrome: An Italian Multicenter Study,” The Annals of Thoracic Surgery, Vol. 88, No. 2, 2009, pp. 440-444. doi:10.1016/j.athoracsur.2009.04.099 Copyright © 2012 SciRes. ACT |