

Paper Menu >>
Journal Menu >>
 Open Journal of Pathology, 2012, 2, 155-158 Published Online October 2012 (http://www.SciRP.org/journal/ojpathology) http://dx.doi.org/10.4236/ojpathology.2012.24029 Copyright © 2012 SciRes. OJPathology 1 Rapid Disappearance of Testicular Plasmacytoma after Treatment with Lenalidomide plus Dexamethasone Masao Hagihara1*, Morihiro Inoue1, Jian Hua1, Nobuyasu Iwaki1, Kosuke Yoshioka2, Takeshi Kobayashi2 1Department of Hematology, Eiju General Ho sp ital, Tokyo, Japan; 2Hematology Division, Tokyo Metropolitan Cancer and Infectious Diseases Center, Komagome Hospital, Tokyo, Japan. Email: *[email protected] Received June 2nd, 2012; revised July 6th, 2012; accepted July 18th, 2012 ABSTRACT We describe a rare case of testicular plasmacytoma first manifesting as a relapse. The patient was initially diagnosed with IgG-λ-type multiple myeloma and treated with melphalan and prednisolon e plus bortezomib, achieving a complete remission. Four months later, his left scrotum began to swell and pathological investig ation of a need le biopsy sp ecimen revealed proliferation of plasma cells expressing IgG-λ, confirming myeloma recurrence. However, bone marrow aspi- ration samples showed no significant increase in myeloma cells and there was no skewed deviation of the ratio on flow-cytometric analysis. The extramedullary tumors disappeared completely soon after treatment with lenalidomide plus dexamethasone, and the patient was judged to be in very good partial remission based on negative M-protein re- sults by serum immunoelectrophoresis. This is the first report, to our knowledge, describing complete disappearance of a testicular plasmacytoma after treatment with lenalidomide as the key-drug. Keywords: Plasmacytoma; Testis; Lenalidomide 1. Introduction Extramedullary plasmacytoma (EMP) is a plasma cell neoplasm that occurs as a solitary lesion or develops si- multaneously or secondarily to multip le myeloma (MM). EMP can involve a wide variety of anatomical sites, but approximately 85% of all cases have disease in the head and neck region [1]. Testicular plasmacytoma is ex- tremely uncommon and estimated to account for 0.03% - 0.1% of all testicular malignancies or around 2% of all plasma cell neoplasms [2-5]. In previous reports, the majority of testicular plasmacytoma cases had been diag- nosed based on local manifestation of sy st emi c pl asma cell disorders rather than as having a solitary EMP [2,6-9]. Herein, we present a rare case in which testicular in- volvement without bone marrow invasion was observed 4 months after the first complete remission of MM had been achieved using a regimen that included bortezomib. Furthermore, the extramedullary tumor disappeared com- pletely after treatment with another novel anti-myeloma reagent, lenalido mide. 2. Case Report A 78-year-old man was admitted to our hospital in March 2011. Two years before (in 2009), the patient had com- plained of pain in multiple b ones, which led to a diagno- sis of IgG-λ-type MM, Durie-Salmon stage II, with mul- tiple bone fractures (ribs, thoracic and lumbar vertebrae), elevated serum IgG (6075 mg/dL) and proliferation of plasma cells (18% of whole nucleated cells) in bone marrow. After receiving 10 cycles of melphalan and prednisolone plus bortezomib (MPV) treatment, he had achieved a complete remission in October 2010. In Feb- ruary 2011, swelling in his left scrotum manifested. Al- though there were no significant changes in laboratory data, his serum IgG level was slightly increased (1872 mg/dL) and a monoclonal band of IgG-λ was identified by immunoelectrophoresis. At that time, a needle biopsy of the left scrotum was performed, and the proliferation of plasma cells was revealed by pathological investiga- tion. As shown in Figure 1, the plasma cells expressed the IgG-λ light chain and CD138 when examined immu- nohistochemically, confirming the tumor to be a mye- loma recurrence. On admission, magnetic resonance imaging (MRI) showed an enlarged mass in the left scrotum and chest computed tomography (CT) demonstrated a tumor in the right thoracic pleura (Figures 2(a) and (c)). However, bone marrow aspiration samples showed no significant *Corresponding a uthor. 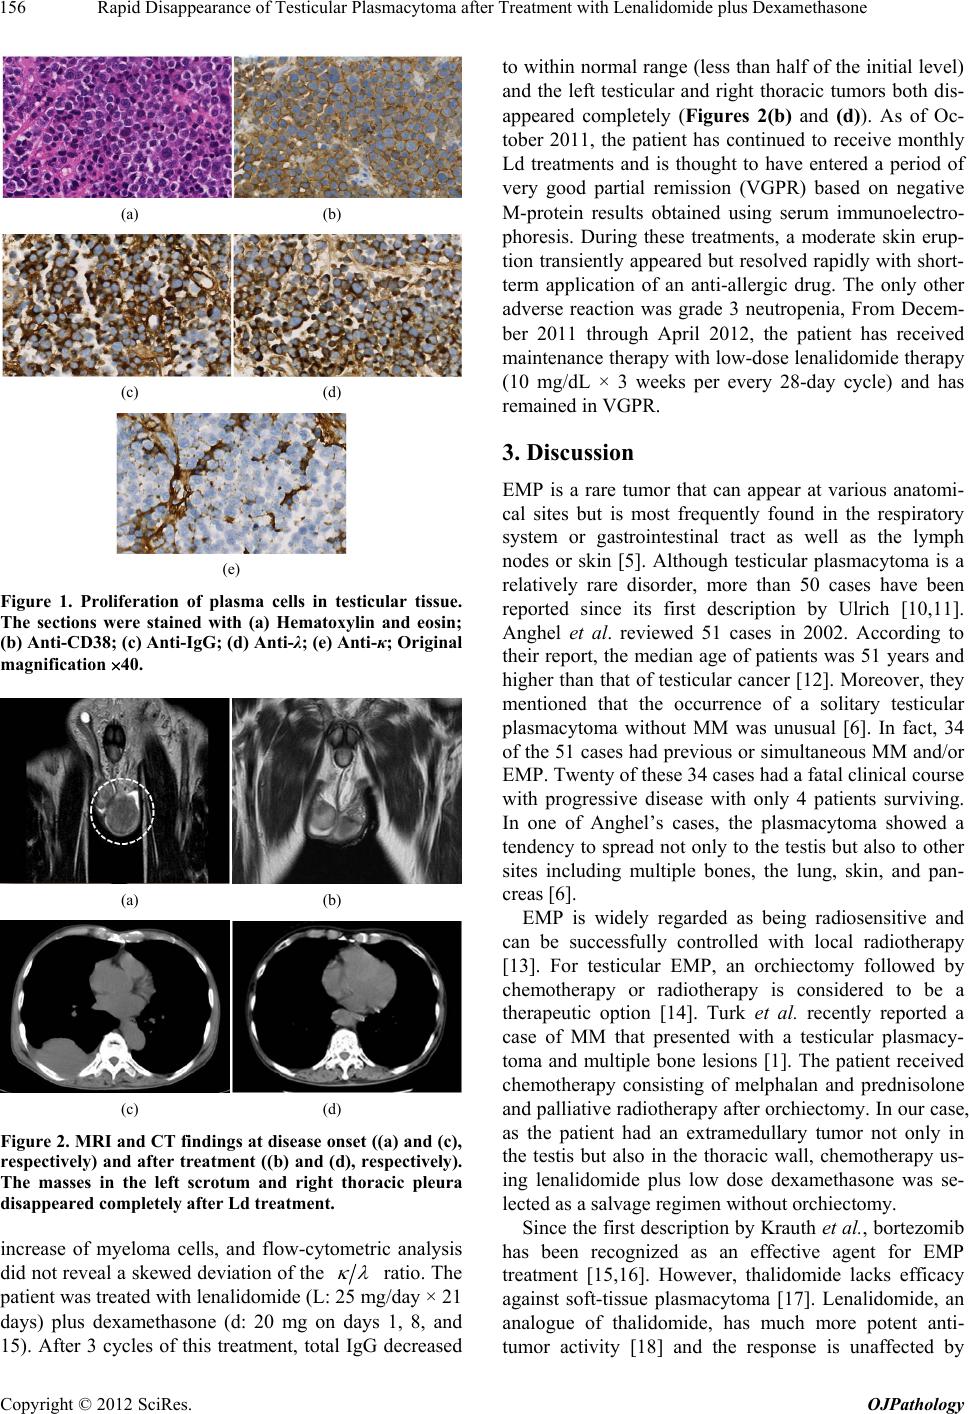 Rapid Disappearance of Testicular Plasmacytoma after Treatment with Lenalidomide plus Dexamethasone 156 (a) (b) (c) (d) (e) Figure 1. Proliferation of plasma cells in testicular tissue. The sections were stained with (a) Hematoxylin and eosin; (b) Anti-CD38; (c) Anti-IgG; (d) Anti-λ; (e) Anti-κ; Original magnification 40. (a) (b) (c) (d) Figure 2. MRI and CT findings at disease onset ((a) and (c ), respectively) and after treatment ((b) and (d), respectively). The masses in the left scrotum and right thoracic pleura disappeared completely after Ld treatment. increase of myeloma cells, and flow-cytometric analysis did not reveal a skewed deviation of the ratio. The patient was treated with len alidomide (L: 25 mg/day × 21 days) plus dexamethasone (d: 20 mg on days 1, 8, and 15). After 3 cycles of this treatment, total IgG decreased to within normal range (less than half of the initial level) and the left testicular and right thoracic tumors both dis- appeared completely (Figures 2(b) and (d)). As of Oc- tober 2011, the patient has continued to receive monthly Ld treatments and is thought to have entered a period of very good partial remission (VGPR) based on negative M-protein results obtained using serum immunoelectro- phoresis. During these treatments, a moderate skin erup- tion transiently ap peared but resolved rapidly with shor t- term application of an anti-allergic drug. The only other adverse reaction was grade 3 neutropenia, From Decem- ber 2011 through April 2012, the patient has received maintenance therapy with low-do se lenalidomide therapy (10 mg/dL × 3 weeks per every 28-day cycle) and has remained in VGPR. 3. Discussion EMP is a rare tumor that can appear at various anatomi- cal sites but is most frequently found in the respiratory system or gastrointestinal tract as well as the lymph nodes or skin [5]. Although testicular plasmacytoma is a relatively rare disorder, more than 50 cases have been reported since its first description by Ulrich [10,11]. Anghel et al. reviewed 51 cases in 2002. According to their report, the median age of patients was 51 years and higher than th at of testicular cancer [12]. Moreover, they mentioned that the occurrence of a solitary testicular plasmacytoma without MM was unusual [6]. In fact, 34 of the 51 cases had previous or simultaneous MM and/or EMP. Twenty of these 34 cases had a fatal clinical course with progressive disease with only 4 patients surviving. In one of Anghel’s cases, the plasmacytoma showed a tendency to spread not only to the testis but also to other sites including multiple bones, the lung, skin, and pan- creas [6]. EMP is widely regarded as being radiosensitive and can be successfully controlled with local radiotherapy [13]. For testicular EMP, an orchiectomy followed by chemotherapy or radiotherapy is considered to be a therapeutic option [14]. Turk et al. recently reported a case of MM that presented with a testicular plasmacy- toma and multiple bone lesions [1]. The patient received chemotherapy consisting of melphalan and prednisolone and palliative radiotherapy after orchiecto my. In our case, as the patient had an extramedullary tumor not only in the testis but also in the thoracic wall, chemotherapy us- ing lenalidomide plus low dose dexamethasone was se- lected as a salvage regimen without orchiectomy. Since the first d escription by Krauth et al., bortezomib has been recognized as an effective agent for EMP treatment [15,16]. However, thalidomide lacks efficacy against soft-tissue plasmacytoma [17]. Lenalidomide, an analogue of thalidomide, has much more potent anti- tumor activity [18] and the response is unaffected by Copyright © 2012 SciRes. OJPathology  Rapid Disappearance of Testicular Plasmacytoma after Treatment with Lenalidomide plus Dexamethasone 157 previous bortezomib treatment [19,20]. Rosenberg et al. presented a case of testicular plasmacytoma with previ- ous MM in which regression of the mass was achieved using a combination of bortezomib and lenalidomide [21]. Furthermore, Carovo-Villas et al. recently reported that lenalidomide in combination with dexamethasone was effective against extramedullary plasmacytoma in pa- tients with relapsed or refractory MM [22]. For their 18 reported cases, the overall response was 61%, including a complete disappearance in 44% of these cases. It was assumed that lenalidomide could have direct anti-prolif- erative mechanisms on myeloma cells irrespective of its existence in the bone marrow stroma or other tissue mi- croenvironments [23]. Angiogenesis is promoted in plas- macytoma tissue, such that lenalidomide might exhibit anti-tumor activity especially through its anti-angiogenic effects [24]. Adams et al. reported that bortezomib did not penetrate into testicular tissue [25]. It might be the reason why plasmacytoma appeared especially in testis. Our experience might indicate that lenalidomide could possibly be distributed in testis. Carovo-Villas et al. noted that 3 of 11 patients re- lapsed and new strategies were thus necessary to over- come treatment resistance of the disease [22]. Recently, abundant encouraging data have been accumulated re- garding the clinical significance of maintenance therapy using lenalidomid e [26]. Therefore, we are still now giv- ing this patient low-dose lenalidomide alone, as mainte- nance therapy, even though attained VGPR. In conclusion, we demonstrated an excellent clinical effect of lenalidomide on a rare type of testicular plas- macytoma in a patient with relapse after administration of bortezomib, the widely accepted first choice for the EMP treatment. REFERENCES [1] H. M. Turk, S. Komurcu, A. Ozet, O. Kuzhan and O. Gunhan, “An Unusual Presentation of Extramedullary Plasmacytoma in Testis and Review of the Literature,” Medical Oncology, Vol. 27, No. 4, 2010, pp. 1378-1380. doi:10.1007/s12032-009-9390-x [2] H. S. Levin and F. K. Mostofi, “Symptomatic Plasmacy- toma of the Testis,” Cancer, Vol. 25, No. 5, 1970, pp. 1193-1203. doi:10.1002/1097-0142(197005)25:5<1193::AID-CNCR2 820250527>3.0.CO;2-6 [3] G. Chica, D. E. Johnson and A. G. Ayala, “Plasmacytoma of Testis Presenting as Primary Testicular Tumor,” Urol- ogy, Vol. 11, No. 1, 1978, pp. 90-92. doi:10.1016/0090-4295(78)90213-3 [4] N. F. Gowing, “Malignant Lymphoma of the Testis,” British Journal of Urology, Vol. 36, 1964, pp. 85-94. [5] D. W. Hayes, W. A. Bennett and F. J. Heck, “Extrame- dullary Lesions in Multiple Myeloma: Review of Litera- ture and Pathologic Studies,” AMA Archives of Pathology, Vol. 53, No. 3, 1952, pp. 262-272. [6] G. Anghel, N. Petti, D. Remotti, C. Ruscio, F. Blandino and I. Majolino, “Testicular Plasmacytoma: Report of a Case and Review of the Literature,” American Journal of Hematology, Vol. 71, No. 2, 2002, pp. 98-104. doi:10.1002/ajh.10174 [7] A. M. Avitable, T. S. Gansler, J. E. Tomaszewski, P. Hanno and M. I. Goldwein, “Testicular Plasmacytoma,” Urology, Vol. 34, No. 1, 1989, pp. 51-54. doi:10.1016/0090-4295(89)90159-3 [8] P. I. Oppenheim, S. Cohen and K. H. Anders, “Testicular Plasmacytoma. A Case Report with Immunohistochemi- cal Studies and Literature Review,” Archives of Pathol- ogy & Laboratory Medicine, Vol. 115, No. 6, 1991, pp. 629-632. [9] M. Castagna, P. Gaeta, M. Cecchi, G. L. Pagni and R. Pingitore, “Bilateral Synchronous Testicular Involvement in Multiple Myeloma. Case Report and Review of the Lit- erature,” Tumori, Vol. 83, No. 4, 1997, pp. 768-771. [10] J. A. Ferry, R. H. Young and R. E. Scully, “Testicular and Epididymal Plasmacytoma: A Report of 7 Cases, Include- ing Three That Were the Initial Manifestation of Plasma Cell Myeloma,” The American Journal of Surgical Pa- thology, Vol. 21, No. 5, 1997, pp. 590-598. doi:10.1097/00000478-199705000-00013 [11] H. Ulrich, “Multiple Myeloma,” Archives of Internal Medicine, Vol. 64, No. 5, 1939, pp. 994-1016. doi:10.1001/archinte.1939.00190050100008 [12] S. D. Fossa, M. Cvancarova, L. Chen, A. L. Allan, J. Oldenburg, D. R. Peterson and L. B. Travis, “Adverse Prognostic Factors for Testicular Cancer-Specific Sur- vival: A Population-Based Study of 27,948 Patients,” Journal of Clinical Oncology, Vol. 26, No. 6, 2011, pp. 963-970. doi:10.1200/JCO.2010.32.3204 [13] N. A. Mayr, B. C. Wen, D. H. Hussey, C. P. Burns, J. J. Staples, J. F. Doornbos and A. P. Vigliotti, “The Role of Radiation Therapy in the Treatment of Solitary Plas- macytoma s,” Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncol- ogy, Vol. 17, No. 4, 1990, pp. 293-303. doi:10.1016/0167-8140(90)90003-F [14] M. Alvarez-Mugica, A. J. Monzon, V. B. Vazquez, C. A. Andrea, J. M. F. Gomez, R. C. G. Alvarez and F. J. R. Sejas, “Secondary Testicular Plasmocytoma,” Archivos Espanoles de Urologia, Vol. 60, No. 1, 2007, pp. 99-102. [15] M. T. Krauth, A. Bankier, P. Valent, P. Kalhs and J. Drach, “Sustained Remission Including Marked Regres- sion of a Paravertebral Plasmacytoma in a Patient with Heavily Pretreated, Relapsed Multiple Myeloma after Treatment with Bortezomib,” Leukemia Research, Vol. 29, No. 12, 2005, pp. 1473-1477. doi:10.1016/j.leukres.2005.05.003 [16] R. Laura, M. T. Cibeira, C. Uriburu, S. Yantorno, O. Salamero, J. Blade and E. Montserrat, “Bortezomib: An Effective Agent in Extramedullary Disease in Multiple Myeloma,” European Journal of Haematology, Vol. 76, No. 5, 2006, pp. 405-408. doi:10.1111/j.0902-4441.2005.t01-1-EJH2462.x [17] G. Damaj, M. Mohty, N. Vey , E. Dincan, R. Bouabdallah, Copyright © 2012 SciRes. OJPathology  Rapid Disappearance of Testicular Plasmacytoma after Treatment with Lenalidomide plus Dexamethasone Copyright © 2012 SciRes. OJPathology 158 C. Faucher, A. M. Stoppa and J. A. Gastaut, “Features of Extramedullary and Extraosseous Multiple Myeloma: A Report of 19 Patients from a Single Center,” European Journal of Haematology, Vol. 73, No. 6, 2004, pp. 402- 406. doi:10.1111/j.1600-0609.2004.00331.x [18] M. Dimopoulos, A. Spencer, M. Attal, H. M. Prince, J. L. Harousseau, A. Dmoszynska, J. San Miguel, A. Hellmann, T. Facon, R. Foa, A. Corso, Z. Masliak, M. Olesnyckyj, Z. Yu, J. Patin, J. B. Zeldis and R. D. Knight, “Lenalido- mide plus Dexamethasone for Relapsed or Refractory Multiple Myeloma,” The New England Journal of Medi- cine, Vol. 357, No. 21, 2007, pp. 2123-2132. doi:10.1056/NEJMoa070594 [19] M. A. Dimopoulos, E. Kastritis, D. Christoulas, M. Mig- kou, M. Gavriatopoulou, M. Gkotzamanidou, M. Ia kovaki, C. Matsouka, D. Mparmparoussi, M. Roussou, E. Ef- stathiou and E. Terpos, “Treatment of Patients with Re- lapsed/Refractory Multiple Myeloma with Lenalidomide And Dexamethasone with or without Bortezomib: Pro- spective Evaluation of the Impact of Cytogenetic Abnor- malities and of Previous Therapies,” Leukemia: Official Journal of the Leukemia Society of America, Vol. 24, No. 10, 2010, pp. 1769-1778. doi:10.1038/leu.2010.175 [20] E. Kneppers, H. M. Lokhorst, C. M. Eeltink, G. Huls, M. J. Kersten, J. Koedam, M. C. Minnema, M. H. van Oers, R. A. Raymakers, M. R. Schaafsma, E. Vellenga, P. W. Wijermans, S. Wittebol, P. Sonneveld and S. Zweegman, “Analysis of Efficacy and Prognostic Factors of Le- nalidomide Treatment as Part of a Dutch Compassionate Use Program,” Clinical lymphoma, Myeloma & Leukemia, Vol. 10, No. 2, 2010, pp. 138-143. doi:10.3816/CLML.2010.n.020 [21] S. Rosenberg, N. Shapur, O. Gofrit and R. Or, “Plas- macytoma of the Testis in a Patient with Previous Multi- ple Myeloma: Is the Testis a Sanctuary Site?” Journal of Clinical Oncology: Official Journal of the American So- ciety of Clinical Oncology, Vol. 28, No. 27, 2010, pp. e456-e458. [22] J. M. Calvo-Villas, A. Alegre, C. Calle, M. T. Hernandez, R. Garcia-Sanchez and G. Ramirez, “Lenalidomide Is Ef- fective for Extramedullary Disease in Relapsed or Re- fractory Multiple Myeloma,” European Journal of Hae- matology, Vol. 87, No. 3, 2011, pp. 281-284. doi:10.1111/j.1600-0609.2011.01644.x [23] T. Fukushima, T. Nakamura, H. Iwao and H. Umehara, “Rapid Response of Plasmacytomas to Lenalidomide plus Low-Dose Dexamethasone Therapy in a Patient with Re- lapsed Multiple Myeloma,” American Journal of Hema- tology, Vol. 86, No. 10, 2011, p. 893. doi:10.1002/ajh.22110 [24] S. Kumar, R. Fonseca, A. Dispenzieri, M. Q. Lacy, J. A. Lust, L. Wellik, T. E. Witzig, M. A. Gertz, R. A. Kyle, P. R. Greipp and S. V. Rajkumar, “Prognostic Value of An- giogenesis in Solitary Bone Plasmacytoma,” Blood, Vol. 101, No. 5, 2003, pp. 1715-1717. doi:10.1182/blood-2002-08-2441 [25] J. Adams, V. J. Palombella, E. A. Sausville, J. Johnson, A. Destree, D. D. Lazarus, J. Maas, C. S. Pien, S. Prakash and P. J. Ellott, “Proteasome Inhibitors: A Novel Class of Potent and Effective Antitumor Agents,” Cancer Re- search, Vol. 59, No. 11, 1999, pp. 2615-2622. [26] A. Palumbo, F. Gay, P. Fa lco, C. Crippa, V. Montefusco, F. Patriarca, F. Rossini, S. Caltagirone, G. Benevolo, N. Pescosta, T. Guglielmelli, S. Bringhen, M. Offidani, N. Giuliani, M. T. Petrucci, P. Musto, A. M. Liberati, G. Rossi, P. Corradini and M. Boccadoro, “Bortezomib as Induction before Autologous Transplantation, Followed by Lenalidomide as Consolidation-Maintenance in Un- treated Multiple Myeloma Patients,” Journal of Clinical Oncology, Vol. 28, No. 5, 2010, pp. 800-807. doi:10.1200/JCO.2009.22.7561 |