

Paper Menu >>
Journal Menu >>
 Modern Plastic Surgery, 2012, 2, 83-86 http://dx.doi.org/10.4236/mps.2012.24020 Published Online October 2012 (http://www.SciRP.org/journal/mps) 83 Assessing Injection Techniques in the Treatment of Trigger Finger John R. Fowler1, Lauren Ogrich2, Perry Evangelista3, Alyssa A. Schaffer1 1Temple University Hospital, Department of Orthopaedics, Philadelphia, USA; 2Temple University School of Medicine, Philadelphia, USA; 3University of Pennyslvania School of Medicine, Philadelphia, USA. Email: [email protected] Received June 7th, 2012; revised July 8th, 2012; accepted August 6th, 2012 ABSTRACT Background: Trigger finger is characterized by the inability to smoothly flex and extend the digit. Corticosteroids are an accepted non-surgical treatment option and can be delivered via two techniques. While the palmar approach is more commonly used, some have suggested that the mid-axial approach may be less painful for patients and yield higher in- trasheath injection rates. The purpose of this study is to compare the accuracy of the palmar and midaxial approaches for delivery of corticosteroids into the flexor tendon sheath using radio-opaque dye in a cadaver model. Methods: A total of 50 injections were performed, 25 via midaxial technique and 25 via palmar technique. A one inch, 25-gauge needle was used to inject 1 mL of Isovue contrast dye into the flexor tendon sheath under live fluoroscopy. The fluoro- scopic images were examined after injection to determine intrasheath versus extrasheath delivery of the dye, with visu- alization of contrast filling the sheath defining a successful injection. Results: The midaxial approach had a success rate of 52% compared to the conventional palmar approach success rate of 36%, p = 0.5. The ring finger is the most com- mon location of trigger finger and the rates of success were equal between groups for this digit (80%). Conclusions: Based on our findings, there is no statistical difference in the accuracy of intrasheath injection between the midaxial technique and palmar technique. The midaxial technique can be considered as an alternative to the palmar technique for trigger finger injection. Keywords: Trigger Finger; Injection; Corticosteroids; Palmar and Midaxial Approaches 1. Introduction Trigger finger, also known as stenosing tenosynovitis or stenosing tendovaginitis, is a common condition affect- ing nearly 100,000 Americans annually [1]. It is charac- terized by the inability to smoothly flex and extend the digit [1]. The patho physiology of stenosing tenosynovitis is related to a disproportion between the volume of the flexor sheath and its contents, the flexor tendons [1]. Non-surgical management consists of activity modifica- tion, non-steroidal anti-inflammatory medications, and corticosteroid injection [1]. The reported effectiveness of corticosteroid injections has ranged from 25% - 77% [2- 6]. A recent systematic review examining the effective- ness of corticosteroid injections found corticosteroid in- jections to be effective in only 57% of patients [7]. Although several studies have found extra-sheath cor- ticosteroid injections to have some benefit in the treat- ment of trigger finger [3,8], the gold standard remains delivery of the corticosteroid into the flexor tendon sheath [1,9]. Two major techniques exist to deliver the corticosteroid into the flexor tendon sheath: the palmar approach and the midaxial approach [1,2,9]. While the palmar approach is more commonly used, some have suggested that the mid-axial approach may be less pain- ful for patients and yield higher intrasheath injection rates [1,2,9]. Studies examining the accuracy of intra- sheath injection by conventional techniques found deliv- ery into the tendon sheath occurs in only 37% - 50% of patients [8,10]. If intrasheath delivery of therapeutic me- dications is an important factor in the treatment of trigger finger, then determining the optimal injection technique is critical. The purpose of this study is to compare the accuracy of the palmar and midaxial approaches for delivery of corticosteroids into the flexor tendon sheath using radio- opaque dye in a cadaver model. 2. Methods The left hands of ten embalmed cadavers were used in this study. The cadaver hands were randomly assigned to receive injection of corticosteroid into the flexor tendon sheath by either the midaxial or palmar approach. For the Copyright © 2012 SciRes. MPS 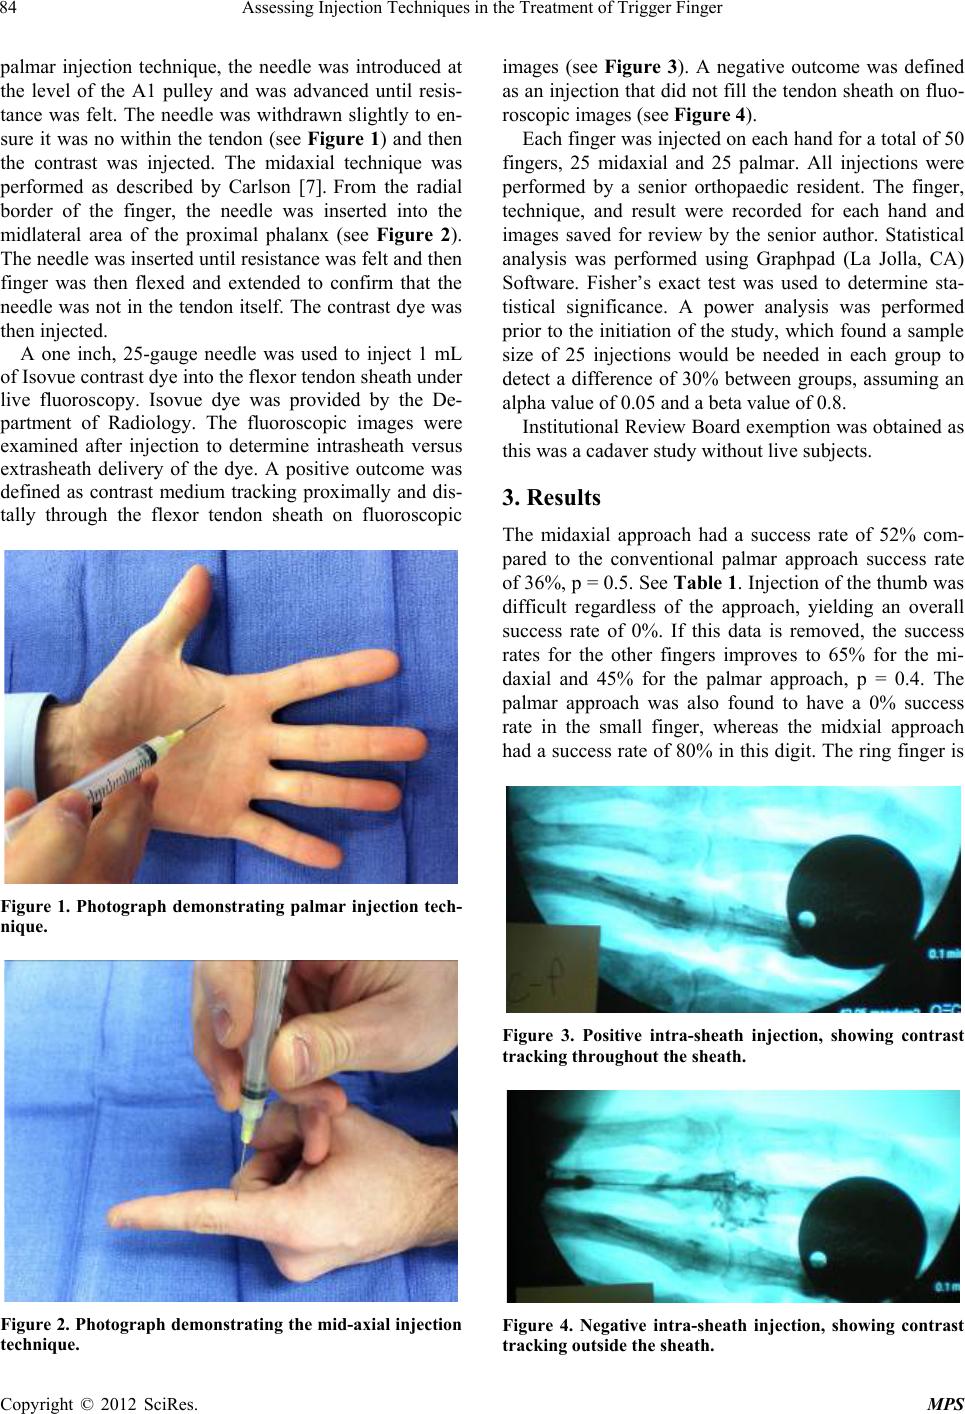 Assessing Injection Techniques in the Treatment of Trigger Finger 84 palmar injection technique, the needle was introduced at the level of the A1 pulley and was advanced until resis- tance was felt. The needle was withdrawn slightly to en- sure it was no within the tendon (see Figure 1) and then the contrast was injected. The midaxial technique was performed as described by Carlson [7]. From the radial border of the finger, the needle was inserted into the midlateral area of the proximal phalanx (see Figure 2). The needle was inserted until resistance was felt an d th en finger was then flexed and extended to confirm that the needle was not in the tendon itself. The contrast dye was then injected. A one inch, 25-gauge needle was used to inject 1 mL of Isovue contrast dye into the flexor tendon sheath under live fluoroscopy. Isovue dye was provided by the De- partment of Radiology. The fluoroscopic images were examined after injection to determine intrasheath versus extrasheath delivery of the dye. A positive outcome was defined as contrast medium tracking proximally and dis- tally through the flexor tendon sheath on fluoroscopic Figure 1. Photograph demonstrating palmar injection tech- nique. Figure 2. Photograph demonstrating the mid-axial injection technique. images (see Figure 3). A negative outcome was defined as an injection that did not fill th e tendon sheath on fluo- roscopic images (see Figure 4). Each finger was injected on each hand for a total of 50 fingers, 25 midaxial and 25 palmar. All injections were performed by a senior orthopaedic resident. The finger, technique, and result were recorded for each hand and images saved for review by the senior author. Statistical analysis was performed using Graphpad (La Jolla, CA) Software. Fisher’s exact test was used to determine sta- tistical significance. A power analysis was performed prior to the initiation of the study, which found a sample size of 25 injections would be needed in each group to detect a difference of 30% between groups, assuming an alpha value of 0.05 and a beta value of 0.8. Institutional Review Board ex emption was obtained as this was a cadaver study withou t live subjects. 3. Results The midaxial approach had a success rate of 52% com- pared to the conventional palmar approach success rate of 36%, p = 0.5. See Table 1. Injection of the thumb was difficult regardless of the approach, yielding an overall success rate of 0%. If this data is removed, the success rates for the other fingers improves to 65% for the mi- daxial and 45% for the palmar approach, p = 0.4. The palmar approach was also found to have a 0% success rate in the small finger, whereas the midxial approach had a success rate of 80% in this digit. The rin g finger is Figure 3. Positive intra-sheath injection, showing contrast tracking throughout the sheath. Figure 4. Negative intra-sheath injection, showing contrast tracking outside the sheath. Copyright © 2012 SciRes. MPS 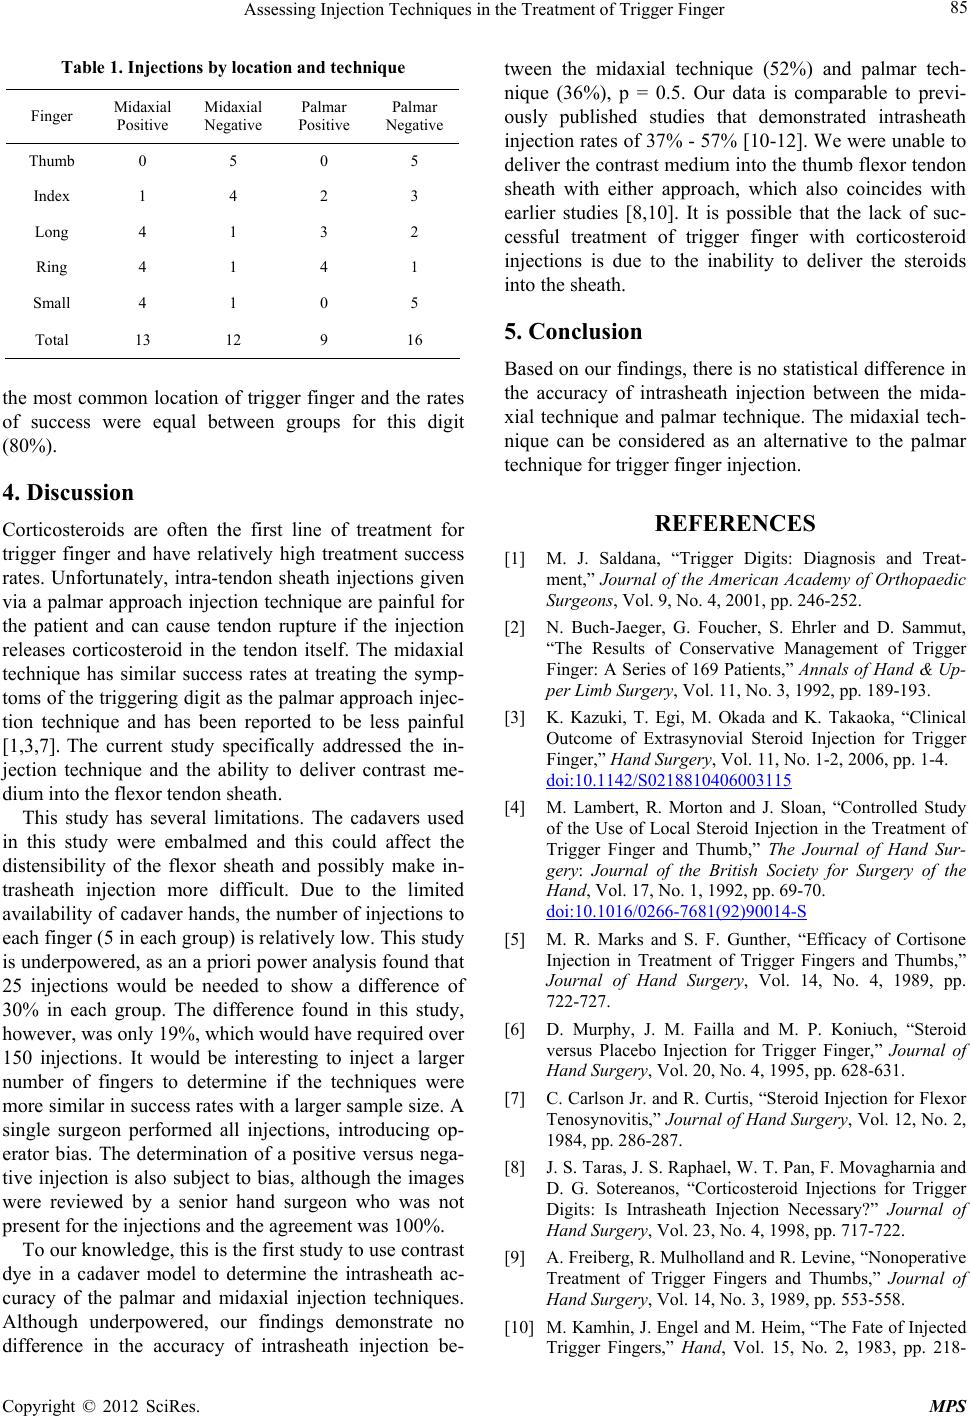 Assessing Injection Techniques in the Treatment of Trigger Finger 85 Table 1. Injections by loca tion and technique Finger Midaxial Positive Midaxial Negative Palmar Positive Palmar Negative Thumb 0 5 0 5 Index 1 4 2 3 Long 4 1 3 2 Ring 4 1 4 1 Small 4 1 0 5 Total 13 12 9 16 the most common location of trigger finger and the rates of success were equal between groups for this digit (80%). 4. Discussion Corticosteroids are often the first line of treatment for trigger finger and have relatively high treatment success rates. Unfortunately, intra-tendon sheath injections given via a palmar approach injection technique are painful for the patient and can cause tendon rupture if the injection releases corticosteroid in the tendon itself. The midaxial technique has similar success rates at treating the symp- toms of the triggering d igit as the palmar approach injec- tion technique and has been reported to be less painful [1,3,7]. The current study specifically addressed the in- jection technique and the ability to deliver contrast me- dium into the flexor tendo n sheath. This study has several limitations. The cadavers used in this study were embalmed and this could affect the distensibility of the flexor sheath and possibly make in- trasheath injection more difficult. Due to the limited availability of cadaver hand s, the number of injections to each finger (5 in each group) is relatively low. This study is underpowered, as an a priori power analysis found that 25 injections would be needed to show a difference of 30% in each group. The difference found in this study, however, was only 19%, which would have required over 150 injections. It would be interesting to inject a larger number of fingers to determine if the techniques were more similar in success rates with a larger sample size. A single surgeon performed all injections, introducing op- erator bias. The determination of a positive versus nega- tive injection is also subject to bias, although the images were reviewed by a senior hand surgeon who was not present for the injections and the agreement was 100%. To our knowledge, this is the first study to use contrast dye in a cadaver model to determine the intrasheath ac- curacy of the palmar and midaxial injection techniques. Although underpowered, our findings demonstrate no difference in the accuracy of intrasheath injection be- tween the midaxial technique (52%) and palmar tech- nique (36%), p = 0.5. Our data is comparable to previ- ously published studies that demonstrated intrasheath injection rates of 37% - 57% [10-12]. We were unable to deliver the contrast medium into the thumb flexor tendon sheath with either approach, which also coincides with earlier studies [8,10]. It is possible that the lack of suc- cessful treatment of trigger finger with corticosteroid injections is due to the inability to deliver the steroids into the sheath. 5. Conclusion Based on our findings, there is no statistical difference in the accuracy of intrasheath injection between the mida- xial technique and palmar technique. The midaxial tech- nique can be considered as an alternative to the palmar technique for trigger finger injection. REFERENCES [1] M. J. Saldana, “Trigger Digits: Diagnosis and Treat- ment,” Journal of the American Academy of Orthopaedic Surgeons, Vol. 9, No. 4, 2001, pp. 246-252. [2] N. Buch-Jaeger, G. Foucher, S. Ehrler and D. Sammut, “The Results of Conservative Management of Trigger Finger: A Series of 169 Patients,” Annals of Hand & Up- per Limb Surgery, Vol. 11, No. 3, 1992, pp. 189-193. [3] K. Kazuki, T. Egi, M. Okada and K. Takaoka, “Clinical Outcome of Extrasynovial Steroid Injection for Trigger Finger,” Hand Surgery, Vol. 11, No. 1-2, 2006, pp. 1-4. doi:10.1142/S0218810406003115 [4] M. Lambert, R. Morton and J. Sloan, “Controlled Study of the Use of Local Steroid Injection in the Treatment of Trigger Finger and Thumb,” The Journal of Hand Sur- gery: Journal of the British Society for Surgery of the Hand, Vol. 17, No. 1, 1992, pp. 69-70. doi:10.1016/0266-7681(92)90014-S [5] M. R. Marks and S. F. Gunther, “Efficacy of Cortisone Injection in Treatment of Trigger Fingers and Thumbs,” Journal of Hand Surgery, Vol. 14, No. 4, 1989, pp. 722-727. [6] D. Murphy, J. M. Failla and M. P. Koniuch, “Steroid versus Placebo Injection for Trigger Finger,” Journal of Hand Surgery, Vol. 20, No. 4, 1995, pp. 628-631. [7] C. Carlson Jr. and R. Curtis, “Steroid Injection for Flexor Tenosynovitis,” Journal of Hand Surgery, Vol. 12, No. 2, 1984, pp. 286-287. [8] J. S. Taras, J. S. Rapha el, W. T. Pan, F. Movagharnia and D. G. Sotereanos, “Corticosteroid Injections for Trigger Digits: Is Intrasheath Injection Necessary?” Journal of Hand Surgery, Vol. 23, No. 4, 1998, pp. 717-722. [9] A. Freiberg, R. Mulholland and R. Levine, “Nonoperative Treatment of Trigger Fingers and Thumbs,” Journal of Hand Surgery, Vol. 14, No. 3, 1989, pp. 553-558. [10] M. Kamhin, J. Engel and M. Heim, “The Fate of Injected Trigger Fingers,” Hand, Vol. 15, No. 2, 1983, pp. 218- Copyright © 2012 SciRes. MPS  Assessing Injection Techniques in the Treatment of Trigger Finger Copyright © 2012 SciRes. MPS 86 220. doi:10.1016/S0072-968X(83)80018-7 [11] S. B. Fleisch, K. P. Spindler and D. H. Lee, “Corticoste r- oid Injections in the Treatment of Trigger Finger: A Level I and II Systematic Review,” Journal of the American Academy of Orthopaedic Surgeons, Vol. 15, No. 3, 2007, pp. 166-171. [12] D. Ring, S. Lozano-Calderón, R. Shin, P. Bastian, C. Mudgal and J. Jupiter, “A Prospective Randomized Con- trolled Trial of Injection of Dexamethasone versus Tri- amcinolone for Idiopathic Trigger Finger,” Journal of Hand Surgery, Vol. 33, No. 4, 2008, pp. 516-522. |