

Paper Menu >>
Journal Menu >>
 Advances in Infectious Diseases, 2012, 2, 72-75 http://dx.doi.org/10.4236/aid.2012.23011 Published Online September 2012 (http://www.SciRP.org/journal/aid) Serum Procalcitonin and Neutrophil Toxic Granules Guided Management of Post-Operative K. pneumoniae Septic-Shock in Laminectomy—A Case Report Indira Chivukula1, Paul K. Marx1, Kamaraju S. Ratnakar2, G. Subbaiah3, Venkataraman Sritharan1* 1Molecular Diagnostics and Biomarkers Laboratory, Department of Laboratory Medicine, Global Hospitals, Hyderabad, India; 2Aca- demic and Research, Global Hospitals, Hyderabad, India; 3Institute of Orthopedics and Spine Surgery, Hyderabad, India. Email: *[email protected] Received April 3rd, 2012; revised May 5th, 2012; accepted June 7th, 2012 ABSTRACT Introduction: We still rely on clinical diagnosis for initiating empirical antibiotic therapy and await blood culture for confirmation of infection, species identification and drug sensitivity. Differential blood cell count (WBC and neutro- phils) and recording of toxic granules in the neutrophils are established methods for indirect diagnosis of infection though they are not used in the diagnosis of sepsis per se. Serum Procalcitonin is considered as a good biomarker in the management of sepsis. Materials and Methods: Whole blood and serum were used for laboratory analysis. We have combined the detection of toxic granules in the peripheral blood smear and serum PCT levels for diagnosis and moni- toring the recovery of a patient with septic shock. A 63 year old laminectomy patient was transferred 2 days after the surgery to our hospital with several co-morbidities and complications. He was in septic shock and was put on Continu- ous Renal Replacement Therapy, with ionotropic support and IV fluids via nasogastric feeding and administration of Activated Protein C. Blood culture and daily measurements of serum Procalcitonin, differential blood cells count, and observation of toxic granules in neutrophils were done. Results: The blood culture showed infection due to K. pneumo- niae resistant to carbapenems. WBC and Neutrophil counts were quite variable and showed incoherent response to treatment. Serum PCT was 24.57 ng/mL on the next day of admission and it peaked at 30.2 ng/mL on day 3. Its level started decreasing from the 4th day. Toxic granules disappeared when serum PCT levels reached < 1 ng/mL. The patient responded well to treatment and he was discharged on the 16th day upon request. Conclusion: This case is presented as an example of managing sepsis with a combination of a conventional hematology marker and a modern biomarker. Re- source poor hospitals with inadequate microbiology services, may evaluate and use these two biomarkers not only for the total management of sepsis but also to reduce the cost of critical care. Keywords: Sepsis; Procalcitonin; Toxic Granules 1. Introduction Sepsis is the most common cause of death in nonco ron ary Intensive Care Units (ICU) with a reported mortality of 29% in the US and 27% in Europe [1], particularly in elderly, immuno compromised/suppressed and critically ill patients. Approximately, 46% of critical care patients and 53% of hospital based patients die due to severe sep- sis in India [2]. Many laboratory results are indistinguishable between patients with Systemic Inflammatory Response Syndrome (SIRS) and sepsis or septic shock with multi organ fail- ure. Differential diagnosis of infection and inflammation is very difficult in the absence of cu lture results. Conv en- tional laboratory indicators for infection, like WBC/ neu- trophils count and serum C-reactive protein (CRP), are non-specific and are often influenced by factors other than infection. Therefore, their status may not directly correlate to either progression or control of infection. Recent reports indicate that absolute neutrophil counts and morphological changes like toxic granules may be better indicators of systemic infection than band count [3]. Since it is desirable to have high sensitivity we used two markers, a biomarker and hematology marker for detecting and monitoring systemic infection (sepsis). Resource poor countries may not have a well equipped microbiology laboratory to do blood culture. Hence, there is an urgent need for biomarkers for a cost-effective and reliable management of sepsis. Procalcitonin (PCT) has been pr oposed as a more spe- cific and better prognostic mark er than differential blood *Corresponding a uthor. Copyright © 2012 SciRes. AID 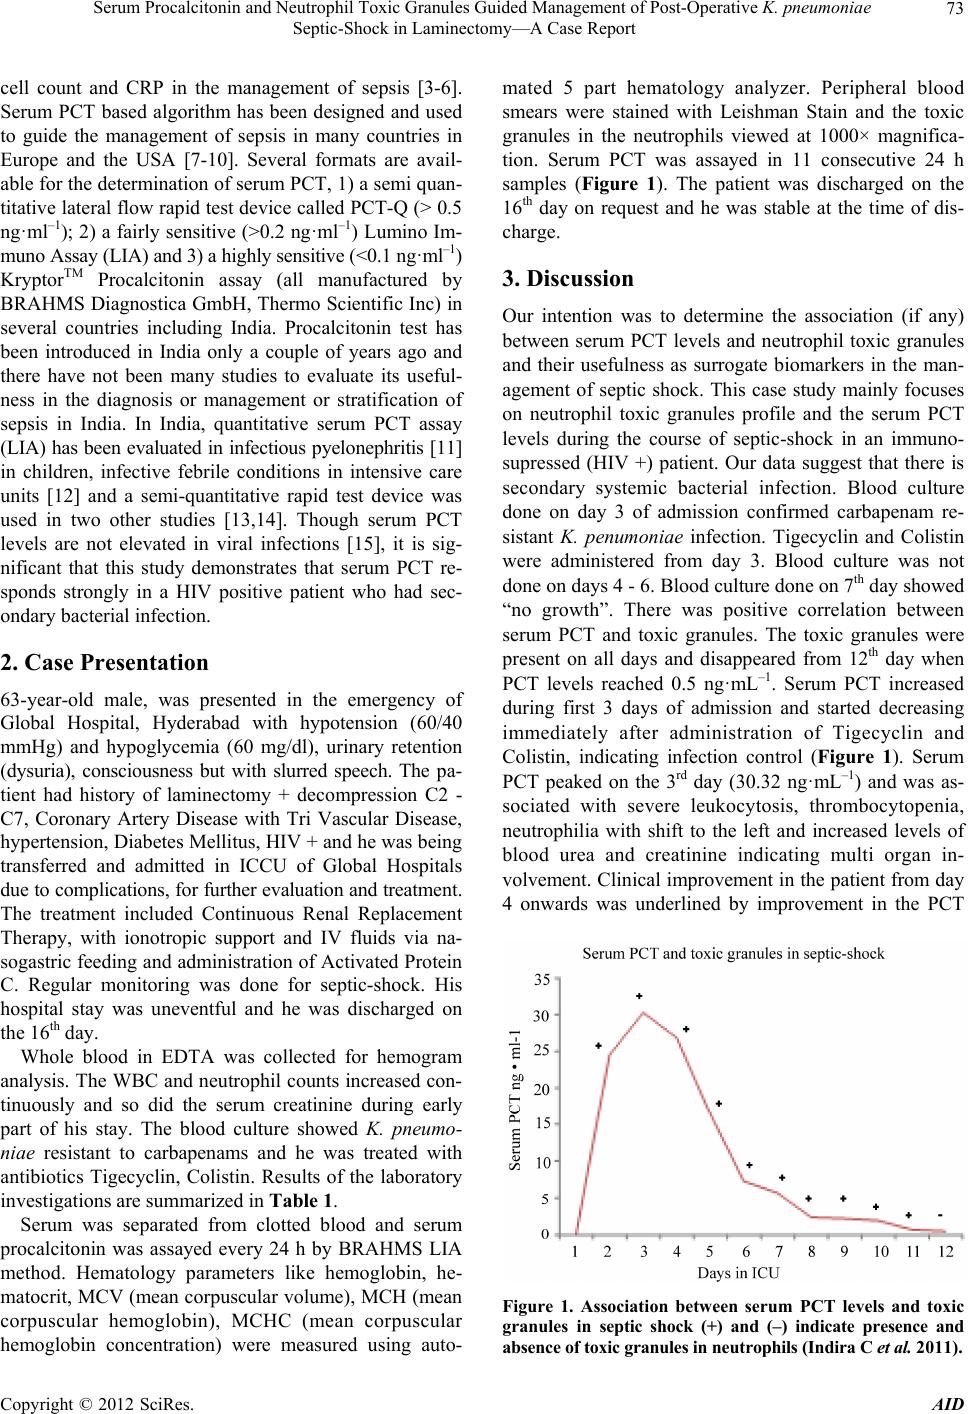 Serum Procalcitonin and Neutrophil Toxic Granules Guided Management of Post-Operative K. pneumoniae Septic-Shock in Laminectomy—A Case Report 73 cell count and CRP in the management of sepsis [3-6]. Serum PCT based algorithm has been designed and used to guide the management of sepsis in many countries in Europe and the USA [7-10]. Several formats are avail- able for the determination of serum PCT, 1) a semi quan- titative lateral flow rapid test device called PCT-Q (> 0.5 ng·ml–1); 2) a fairly sensitive (>0.2 ng·ml–1) Lumino Im- muno Assay (LIA) and 3) a highly sensi ti ve (<0.1 ng·m l –1) KryptorTM Procalcitonin assay (all manufactured by BRAHMS Diagnostica GmbH, Thermo Scientific Inc) in several countries including India. Procalcitonin test has been introduced in India only a couple of years ago and there have not been many studies to evaluate its useful- ness in the diagnosis or management or stratification of sepsis in India. In India, quantitative serum PCT assay (LIA) has been evalua ted in infectious pyelo nephritis [11] in children, infective febrile conditions in intensive care units [12] and a semi-quantitative rapid test device was used in two other studies [13,14]. Though serum PCT levels are not elevated in viral infections [15], it is sig- nificant that this study demonstrates that serum PCT re- sponds strongly in a HIV positive patient who had sec- ondary bacterial infection. 2. Case Presentation 63-year-old male, was presented in the emergency of Global Hospital, Hyderabad with hypotension (60/40 mmHg) and hypoglycemia (60 mg/dl), urinary retention (dysuria), consciousness but with slurred speech. The pa- tient had history of laminectomy + decompression C2 - C7, Coronary Artery Disease with Tri Vascular Disease, hypertension, Diabetes Mellitus, HIV + and he was being transferred and admitted in ICCU of Global Hospitals due to complications, for further evaluation and treatment. The treatment included Continuous Renal Replacement Therapy, with ionotropic support and IV fluids via na- sogastric feeding and administration of Activated Protein C. Regular monitoring was done for septic-shock. His hospital stay was uneventful and he was discharged on the 16th day. Whole blood in EDTA was collected for hemogram analysis. The WBC and neutrophil coun ts increased con- tinuously and so did the serum creatinine during early part of his stay. The blood culture showed K. pneumo- niae resistant to carbapenams and he was treated with antibiotics Tigecyclin, Colistin. Results of the laboratory investigations are summarized in Table 1. Serum was separated from clotted blood and serum procalcitonin was assayed every 24 h by BRAHMS LIA method. Hematology parameters like hemoglobin, he- matocrit, MCV (mean corpuscular volume), MCH (mean corpuscular hemoglobin), MCHC (mean corpuscular hemoglobin concentration) were measured using auto- mated 5 part hematology analyzer. Peripheral blood smears were stained with Leishman Stain and the toxic granules in the neutrophils viewed at 1000× magnifica- tion. Serum PCT was assayed in 11 consecutive 24 h samples (Figure 1). The patient was discharged on the 16th day on request and he was stable at the time of dis- charge. 3. Discussion Our intention was to determine the association (if any) between serum PCT levels and neutrophil toxic granules and their usefulness as surrogate biomarkers in the man- agement of septic shock. This case study mainly focuses on neutrophil toxic granules profile and the serum PCT levels during the course of septic-shock in an immuno- supressed (HIV +) patient. Our data suggest that there is secondary systemic bacterial infection. Blood culture done on day 3 of admission confirmed carbapenam re- sistant K. penumoniae infection. Tigecyclin and Colistin were administered from day 3. Blood culture was not done on days 4 - 6. Blood cultur e done on 7th day showed “no growth”. There was positive correlation between serum PCT and toxic granules. The toxic granules were present on all days and disappeared from 12th day when PCT levels reached 0.5 ng·mL–1. Serum PCT increased during first 3 days of admission and started decreasing immediately after administration of Tigecyclin and Colistin, indicating infection control (Figure 1). Serum PCT peaked on the 3rd day (30.32 ng·mL–1) and was as- sociated with severe leukocytosis, thrombocytopenia, neutrophilia with shift to the left and increased levels of blood urea and creatinine indicating multi organ in- volvement. Clinical improvement in the patient from day 4 onwards was underlined by improvement in the PCT Figure 1. Association between serum PCT levels and toxic granules in septic shock (+) and (–) indicate presence and absence of toxic granules in neutrophils (Indira C et al. 2011). Copyright © 2012 SciRes. AID 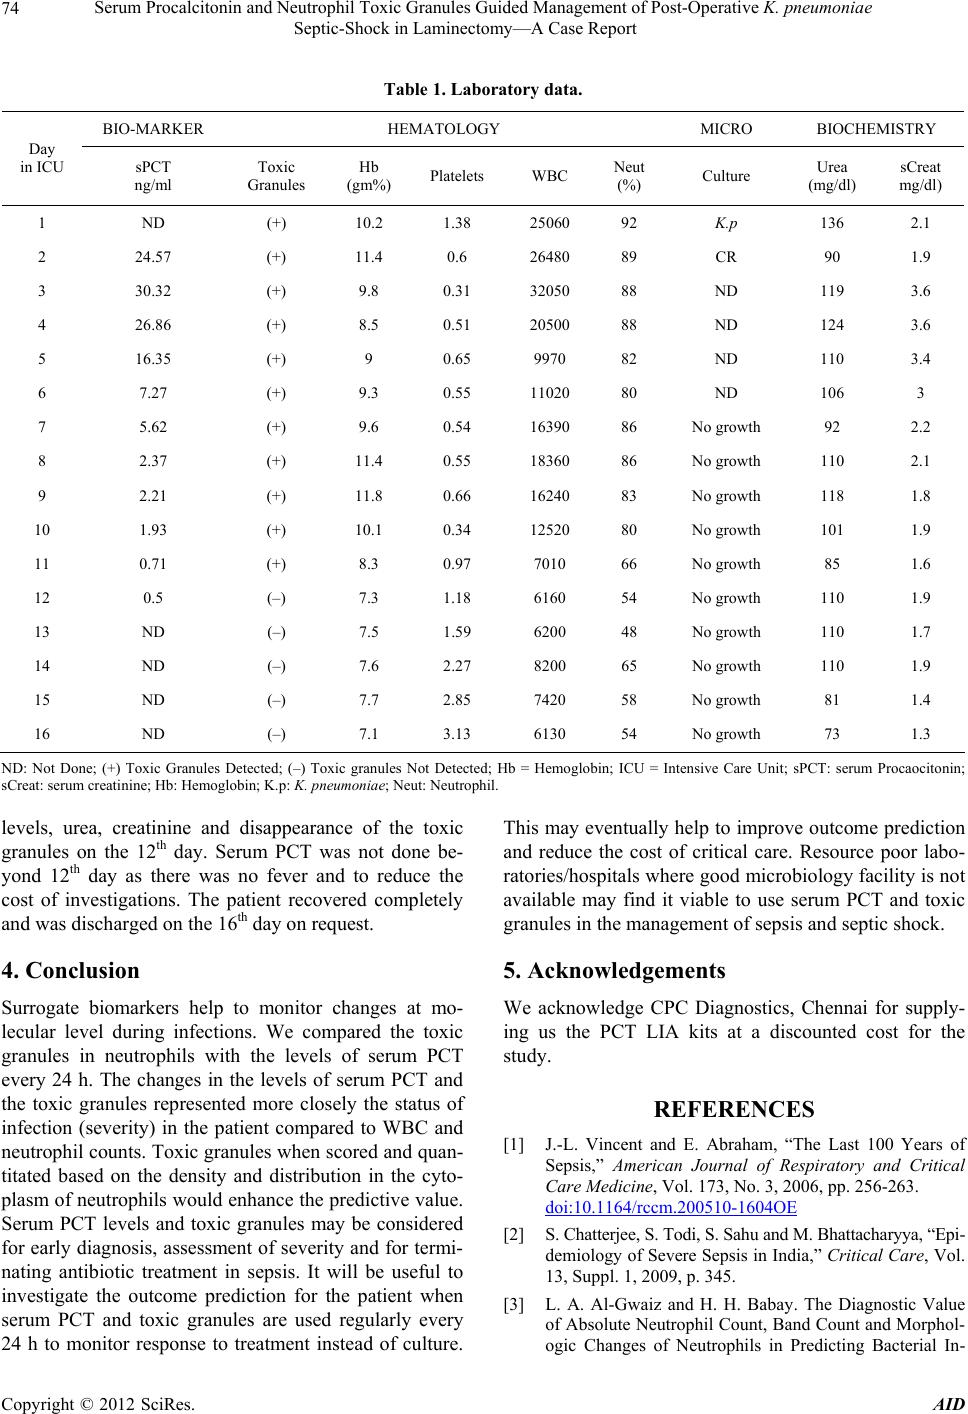 Serum Procalcitonin and Neutrophil Toxic Granules Guided Management of Post-Operative K. pneumoniae Septic-Shock in Laminectomy—A Case Report Copyright © 2012 SciRes. AID 74 Table 1. Laboratory data. BIO-MARKER HEMATOLOGY MICRO BIOCHEMISTRY Day in ICU sPCT ng/ml Toxic Granules Hb (gm%) Platelets WBC Neut (%) Culture Urea (mg/dl) sCreat mg/dl) 1 ND (+) 10.2 1.38 25060 92 K.p 136 2.1 2 24.57 (+) 11.4 0.6 26480 89 CR 90 1.9 3 30.32 (+) 9.8 0.31 32050 88 ND 119 3.6 4 26.86 (+) 8.5 0.51 20500 88 ND 124 3.6 5 16.35 (+) 9 0.65 9970 82 ND 110 3.4 6 7.27 (+) 9.3 0.55 11020 80 ND 106 3 7 5.62 (+) 9.6 0.54 16390 86 No growth 92 2.2 8 2.37 (+) 11.4 0.55 18360 86 No growth 110 2.1 9 2.21 (+) 11.8 0.66 16240 83 No growth 118 1.8 10 1.93 (+) 10.1 0.34 12520 80 No growth 101 1.9 11 0.71 (+) 8.3 0.97 7010 66 No growth 85 1.6 12 0.5 (–) 7.3 1.18 6160 54 No growth 110 1.9 13 ND (–) 7.5 1.59 6200 48 No growth 110 1.7 14 ND (–) 7.6 2.27 8200 65 No growth 110 1.9 15 ND (–) 7.7 2.85 7420 58 No growth 81 1.4 16 ND (–) 7.1 3.13 6130 54 No growth 73 1.3 ND: Not Done; (+) Toxic Granules Detected; (–) Toxic granules Not Detected; Hb = Hemoglobin; ICU = Intensive Care Unit; sPCT: serum Procaocitonin; sCreat: serum creatinine; Hb: Hemog lobin; K.p: K. pneumoniae; Neut: Neutrophil. levels, urea, creatinine and disappearance of the toxic granules on the 12th day. Serum PCT was not done be- yond 12th day as there was no fever and to reduce the cost of investigations. The patient recovered completely and was discharged on the 16th day on request. 4. Conclusion Surrogate biomarkers help to monitor changes at mo- lecular level during infections. We compared the toxic granules in neutrophils with the levels of serum PCT every 24 h. The changes in the levels of serum PCT and the toxic granules represented more closely the status of infection (severity) in the patient compared to WBC and neutrophil counts. Toxic granules when scored and quan- titated based on the density and distribution in the cyto- plasm of neutrophils would enhance the predictive value. Serum PCT levels and toxic granules may be considered for early diagnosis, assessment of severity and for termi- nating antibiotic treatment in sepsis. It will be useful to investigate the outcome prediction for the patient when serum PCT and toxic granules are used regularly every 24 h to monitor response to treatment instead of culture. This may eventually help to improve outcome pred iction and reduce the cost of critical care. Resource poor labo- ratories/hospitals where good microbiology facility is not available may find it viable to use serum PCT and toxic granules in the management of sepsis and septic shock. 5. Acknowledgements We acknowledge CPC Diagnostics, Chennai for supply- ing us the PCT LIA kits at a discounted cost for the study. REFERENCES [1] J.-L. Vincent and E. Abraham, “The Last 100 Years of Sepsis,” American Journal of Respiratory and Critical Care Medicine, Vol. 173, No. 3, 2006, pp. 256-263. doi:10.1164/rccm.200510-1604OE [2] S. Chatterjee, S. Todi, S. Sahu and M. Bhattacharyya, “Epi- demiology of Severe Sepsis in India,” Critical Care, Vol. 13, Suppl. 1, 2009, p. 345. [3] L. A. Al-Gwaiz and H. H. Babay. The Diagnostic Value of Absolute Neutrophil Count, Band Count and Morphol- ogic Changes of Neutrophils in Predicting Bacterial In-  Serum Procalcitonin and Neutrophil Toxic Granules Guided Management of Post-Operative K. pneumoniae Septic-Shock in Laminectomy—A Case Report 75 fections,” Medical Principles and Practice, Vol. 16, No. 5, 2007, pp. 344-347. doi:10.1159/000104806 [4] A. Nakamura, H. Wada, M. Ikejiri, T. Hatada, H. Sakurai , Y. Matsushima, J. Nishioka, K. Maruy ama, S. Isaji, T. Ta- keda and T. Nobori, “Efficacy of Procalcitonin in the Early Diagnosis of Bacterial Infections in a Critical Care Unit,” Shock, Vol. 31, No. 6, 2009, pp. 586-591. doi:10.1097/SHK.0b013e31819716fa [5] L. Simon, F. Gauvin, D. K. Amre, P. Saint-Louis and J. La- croix. “Serum Procalcitonin and C-Reactive Protein Lev- els as Markers of Bacterial Infection: A Systematic Re- view and Meta-Analysis,” Clinical Infectious Diseases, Vol. 39, No. 2, 2004, pp. 206-217. doi:10.1097/SHK.0b013e31819716fa [6] A. van de Vyver, E. F. Delport, M. Esterhuizen and R. Pool, “The Correlation between C-Reactive Protein and Toxic Granulation of Neutrophils in the Peripheral Blood,” South African Medical Journal, Vol. 100, No. 7, 2010, pp. 442-444. [7] P. Schuetz, W. Albrich, M. Christ-Crain, J. Chastre and B. Mueller, “Procalcitonin for Guidance of Antibiotic Ther- apy,” Expert Reviews in Anti Infectives Therapy, Vol. 8, No. 5, 2010, pp. 575-587. doi:10.1586/eri.10.25 [8] P. Emmanuel Charles, E. Kus, S. Aho, S. Prin, J.-M. Doise, N.-O. Olsson, B. Blettery and J.-P. Quenot, “Serum Pro- calcitonin for the Early Recognition of Nosocomial Infec- tion in the Critically Ill Patients: A Preliminary Report,” BMC Infectious Diseases, Vol. 9, No. 1, 2009, pp. 49-58. [9] J. U. Jensen, L. Heslet, T. H. Jensen, K. Espersen, P. Stef- fensen and M. Tvede, “Procalcitonin Increase in Early Identification of Critically Ill Patients at High Risk of Mortality,” Critical Care Medicine, Vol. 34, No. 10, 2006, pp. 2596-2602. doi:10.1097/01.CCM.0000239116.01855.61 [10] C. Pierrakos and J. L. Vincent, “Sepsis Biomarkers: A Review,” Critical Care, Vol. 14, No. 1, 2010, p. R15. doi:10.1186/cc8872 [11] J. C. Singh and N. S. Kekre, “Procalcitonin: A Marker for Renal Parenchymal Infection in Children?” Indian Jour- nal of Urology, Vol. 22, No. 2, 2006, pp. 162-63. [12] S. K. Todi, “Top Stories of 2009,” Indian Journal of Critical Care Medicine, Vol. 14, No. 1, 2010, pp. 3-7. doi:10.4103/0972-5229.63027 [13] U. Sudhir, R. K. Venkatachaliah, T. Anilkumar, M. Yoge- shwar Rao and P. Kempegowda, “Significance of Serum Procalcitonin in Sepsis,” Indian Journal of Critical Care Medicine, Vol. 15, No. 1, 2011, pp. 1-5. doi:10.4103/0972-5229.78214 [14] M. Sinha, S. Desai, S. Mantri and A. Kulkarni, “Procalci- tonin as an Adjunct Biomarker in Sepsis,” Indian Journal of Anesthesia, Vol. 55, No. 3, 2011, pp. 266-270. doi:10.4103/0019-5049.82676 [15] M. Meisner, “PCT in the Differential Diagnosis of Viral and Bacterial Infections,” In: M. Meisner, Ed., Procalci- tonin—A New Innovative Infection Parameter Biochem- ical and Clinical Aspects, 3rd Edi tion, Thie me Verlag, St ut- tgart, 2000, pp 136-37. Copyright © 2012 SciRes. AID |