

Paper Menu >>
Journal Menu >>
 Vol.2, No.3, 200-203 (2010) Health doi:10.4236/health.2010.23029 Copyright © 2010 SciRes Openly accessible at http://www.scirp.org/journal/HEALTH/ Left ventricular noncompaction associated with hypertrophic cardiomyopathy and Wolff-Parkinson-White syndrome Luis Alday1, Eduardo Moreyra1, Eva Bruno2, Norma Rossi3, Hector Maisuls2 1Divisions of Pediatric Cardiology and Cardiology, Sanatorio Allende, Córdoba, Argentina; [email protected] 2Division of Cardiology, Children’s Hospital, Cordoba, Argentina 3Division of Genetics, Private Hospital, Cordoba, Argentina Received 14 October 2009; revised 10 December 2009; accepted 14 December 2009. ABSTRACT We report a 35-year-old female patient with hy- pertrophic cardiomyopathy, left ventricular non- compaction, and Wolff-Parkinson-White EKG patt- ern. Several other family members present the same clinical condition. We speculate that this phenotype is related to the genotypes PRKAG2 and LAMP2 represented by mutations of the genes encoding AMP-activated protein kinase (PRKAG2) and lysosome associated membrane protein 2 (LAMP2 ). Keywords: Left Ventricular Noncompaction; Hypertrophic Cardiomyopathy; Wolff-Parkinson-White Syndrome 1. INTRODUCTION Left ventricular noncompaction (LVNC) is the result from the a rrest in m yocardi al dev elopm ent w ith pe rsist ent sinusoid tracts interspersed with prominent muscular trabeculae. Affected patients usually develop congestive heart failure associated with arrhythmias and systemic thromboembolism.W e report a proband with mental retar- dation and peculiar somatic findings, associated LVNC and hypertrophic cardiomyopathy (HCM). Other family members were also involved, all of them, the proband included, had Wolff-Parkinson-White (WPW) syndrome, suggesting a relationship regarding the etiology of this LVNC - HCM phenotype overlapping. 2. CASE REPORT The proband is a 35-year-old female who had been fol- lowed since infancy. She was referred to us for a heart murmur and congestive heart failure. Clinical examina- tion at presentation was compatible with moderate to severe mitral regurgitation. There was cardiomegaly and signs of pulmonary venous hypertension on the chest X-ray. The EKG showed a WPW pattern with extremely high voltage. Cineangi ography reveal ed a hypercontractile left ventricle without outflow tract obstruction, moderate to severe mitral regurgitation, and a never-seen-before cont our wh ich made i t rese mble a “porcu pine ” since there were heavy trabeculations leaving thin spaces between them as if they were wheel spokes radiating from the center to the periphery of the ventricular cavity. On the basis of the a n gi o gra phic findings this pat i ent’s heart was called a “spongy” heart because was thought to be the result of persistence of embryonic myocardium [1]. The patient was treated for heart failure until early childhood. There was clinical i mprovement with decreasi ng mitral regurgitation as judged by auscultation. She re- mained symptom free for several years and she had non-obstructive HCM with mild mitral insufficiency upon echocardiographic examination. She continued regular follo w- up visits and the echocardiograms showed progression to a dilated stage. Eight years ago she was admitted with pulmonary edema and frequent ventricular extrasystoles. Following treatment she was in NYHA functional class II and was discharged. Occasional re- missions occurred caused by treatment non-com pliance. Presently, she is in functional class III and has slight mental retardation. She has lower than normal stature, a short neck, low posterior hairline, and a high palate. Clinical genetics evaluation suggests the diagnosis of Noonan syndrome. Cardiovascular examination shows, a mitral regurgitation murmur and gallop rhythm. Chest x-ray a nd E KG pr ese nt e d s e ve re ca r di omegaly wi th si g ns of pulmonary venous hypertension and WPW pattern, respectively. Color Doppler-echocardiography demon- strated hypertrophic and dilated left ventr icle with promi- nent cavitary trabeculae compatible with the diagnosis of LVNC (LVNC: C ratio > 2.0), poor contractility, moderate mitral regur gitation, and pericardial ef fusion (Figur e 1(a)). 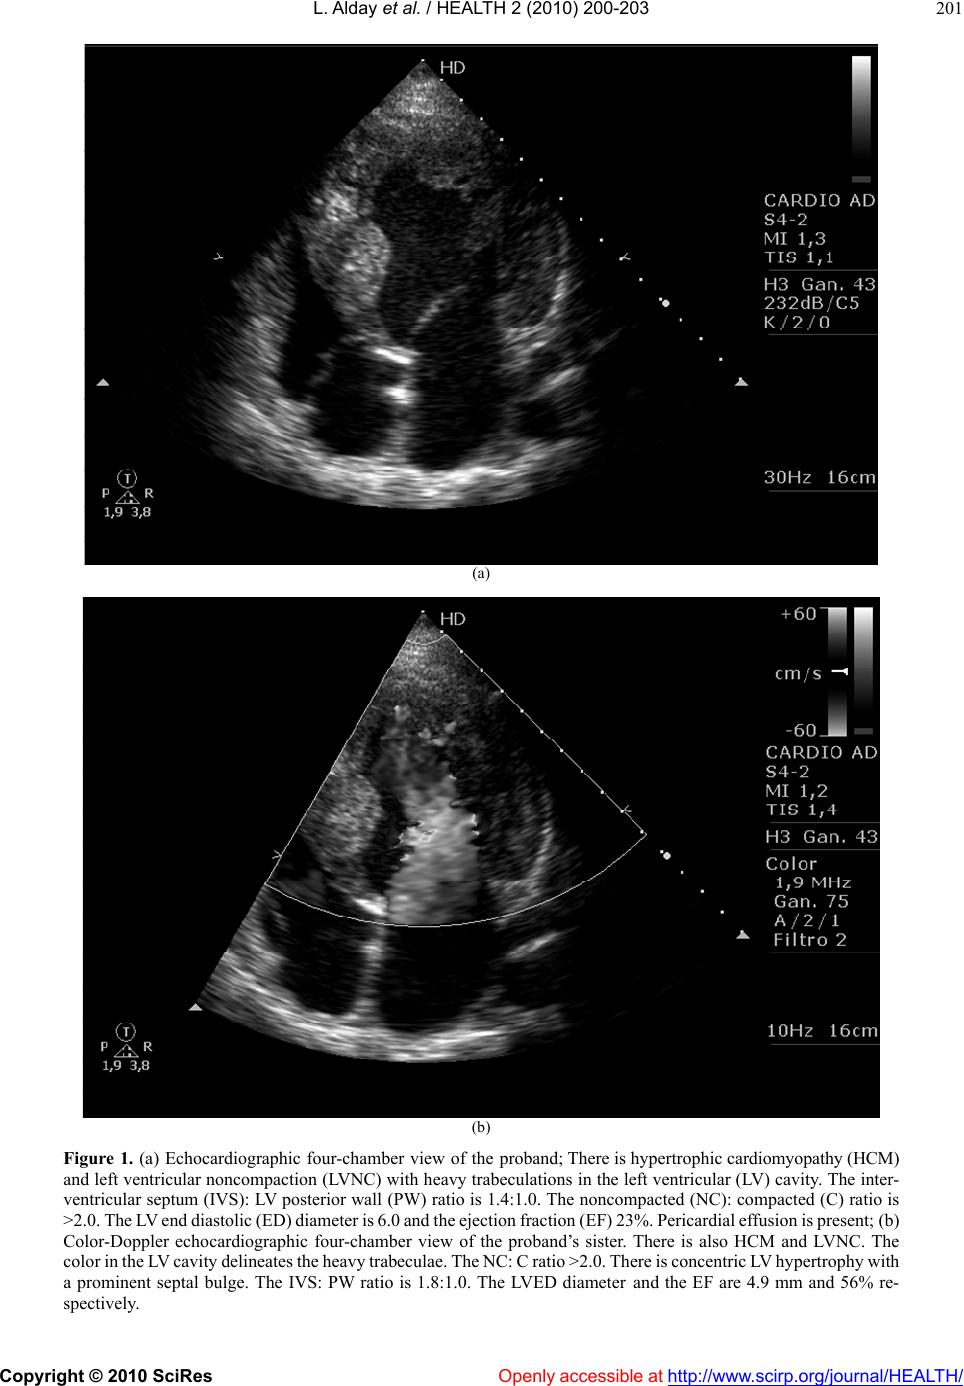 L. Alday et al. / HEALTH 2 (2010) 200-203 Copyright © 2010 SciRes Openly accessible at http://www. scirp.org/journal/HEALTH/ 201 (a) (b) Figure 1. (a) Echocardiographic four-chamber view of the proband; There is hypertrophic cardiom yopathy (H CM) and left ventricular noncompaction (LVNC) with heavy trabeculations in the left ventricular (LV) cavity. The inter- ventricular septum (IVS): LV posterior wall (PW) ratio is 1.4:1.0. The noncompacted (NC): compacted (C) ratio is >2.0. The LV end d iasto lic (ED ) dia meter is 6. 0 and the e jection frac tion (E F) 23 %. Peri cardia l ef fusio n is pr esent ; (b) Color-Doppler echocardiographic four-chamber view of the proband’s sister. There is also HCM and LVNC. The color i n the LV c avity d eline ates t he heav y trab eculae . The NC: C r atio > 2.0. T here i s conce ntric LV hypert rophy w ith a prominent septal bulge. The IVS: PW ratio is 1.8:1.0. The LVED diameter and the EF are 4.9 mm and 56% re- spectively.  L. Alday et al. / HEALTH 2 (2010) 200-203 Copyright © 2010 SciRes Openly accessible at http://www.scirp.org/journal/HEALTH/ 202 I II III Unaffected status Hypertrophic Cardiomyopathy Hypertrophic Cardiomyopat hy and Left Ventricular Noncompaction Unknown clinical status 1 2 345 1 2 3 4 5 6 78 910 11 12 13 14 15 16 1 2 34 56 7 Figure 2. Pedigree of the kindred with hypertrophic cardiomyopathy (HCM), Wolff-Parkinson-White syndrome (WPW), and left ventricular noncompaction (LVNC) inherited as a Mendelian autosomal dominant trait.The proband is pointed by the ar row. I4: Pr oband’s grandmother with unknown clinical statu s. II7 and 8: Proband’s mother and aunt both of them with HCM and WPW. III4: Proband’s sister with HCM, WPW, and LVNC. The better resolution of the new echocardiographic technology allowed confirmation of the initial cinean- giography. An updated family tree (Figure 2) showed an interesting family pattern where the proposita had a 37-year-old sister also with non-obstructive HCM with non-compaction and normal left ventricular function (Figure 1(b)). External features and mental status were normal. She also had a WPW pattern on the EKG with normal voltage. She had occasional episodes of su- praventricular tachycardia. Both the mother and her identical twin had HCM, WPW, and atrial fibrillation. They might have had also LVNC but could not be con- firmed. They died one year apart at the ages of 59 and 60 years due to congestive heart failure and stroke, respec- tively. The mother’s sister had no descendants. The twins had 3 siblings and half- siblings each with no history of HCM. The maternal grandmother died suddenly at a young age of unspecified causes. 3. DISCUSSION LVNC was a poorly recognized entity that began to gain interest from the medical community in the 90’ s. Recently , it has become clear that is more pre valent than previ ously recognized [2]. H owever, its etiology remained unknow n until recently, when molecular genetic studies showed that mutations of cytoskeletal genes like those encoding taffazin (TAZ) and alpha-dystrobrevin (DTNA) causing Barth syndrome were associated with LVNC [3]. More recently , it was found that LV NC was also associated with mutations of sarcomeric genes shared by patients with HCM and dilated cardiomyopathy, like the alpha-cardiac actin gene (ACTC), beta-myosin heavy chain (MYH7), and cardiac troponin T (TNNT2) [4,5]. Cases of patients sharing both the LVNC and HCM phenotypes have been published rece ntly but there was no m ention of a mutation [6,7]. The patient reported here, had other family members with the same disease, and all had the associated WPW syndrome. Such overlapping phenotype suggests a strong genetic association. WPW syndrome is infrequently associated with HCM. It has been found in patients with HCM phenotypes with mutations of the genes encoding AMP-activated protein kinase (PRKAG2) and lysosome associated membrane protein 2 (LAMP2). PRKAG2 is an important enzyme involved in th e production of cellular energy and its mu- tations might cause HCM, WPW syndrome, conduction disorders requiring pacing, skeletal myopathy, and gly- cogen storage disease [8]. About 30% of affected indi- viduals have atrial fibrillation or supraventricular tachy- cardia. This clinical pattern was seen in three of the fam- ily members of our proposita. LAMP-2, an X-linked gene, encodes proteins that regulate the integrity and function of lysosomes. Muta- tions of this gene cause Danon disease characterized by HCM, WPW syndrome, skeletal myopathy and mental retardation. Female carriers present later in life with less severe disease than in males [9].  L. Alday et al. / HEALTH 2 (2010) 200-203 Copyright © 2010 SciRes Openly accessible at http://www. scirp.org/journal/HEALTH/ 203 In the family under discussion, the proband and the sister had a phenotype of HCM, WPW syndrome, and LVNC. The proband had also somatic features suggestive of Noonan syndrome and mental retardation. The dis- eased mother and her twin, with normal external pheno- type, had ha d HCM, WPW syndr ome, an d late onset at rial fibrillation, but LVNC could not be confirmed. The members of this family had features shared with patients affected with the PRKG2 and LAMP-2 mutations. It is then possible that any of the two might be the in- volved gene. There are no systematic molecular genetic studies available showing the association of these genes with the H CM, WPW and LVNC phenotypes. The complex overlapping phenotypes of HCM with WPW syndrome and LVNC seen in this fam ily is possibly due to a previously not described mutation which should be studied further. REFERENCES [1] Van Praagh, R., Personal communication. [2] Pignatelli, R.H., McMahon, C.J., Dreyer, W.J., et al. (2003) Clinical characterization of left ventricular non- compaction in children: a relatively common form of cardiomyopathy. Circulation, 108, 2672-2678. [3] Ichida, F., Tsubata, S., Bowles, K.R., et al. (2001) Novel gene mutations in patients with left ventricular noncompaction or Barth syndrome. Circul ation, 103, 1256-1263. [4] Monserrat, L., Hermida-Prieto, M., Fernandez, X., et al. (2007) Mutation in the alpha-cardiac actin gene associ- ated with apical hypertrophic cardiomy opathy, left ven- tricular non-compaction, and septal defects. European Heart Jour na l, 28, 1953-1961. [5] Klaassen, S., Probst, S., Oechslin, E., et al. (2008) Muta- tion in sarcomere protein genes in left ventricular non- compaction. Circulation, 117, 2893-2901. [6] Pantazis, A.A., Kohll, S.K., and Elliott, P.M. (2006) Images in cardiology. Hypertrophic cardiomyopathy and left ventricular hypertrabeculation: evidence for an overlapping phenotype. Heart, 92, 349. [7] Kelley-Hedgepeth, A., Towbin, J.A., and Maron, M.S. (2009) Images in cardiovascular medicine. Overlapping phenotypes. Left ventricular noncompaction and hy per- trophic cardiomyopathy. Circulati on, 119, 588-589. [8] Murphy, R.T., Mogensen, J., McGarry, K., et al. (2005) Adenosine monophosphate-acti va ted protein kina se dis- ease mimicks hypertrophic cardiomyopathy and Wolff- Parkinson-White sy ndrome. Natural history. Journal of the American College of Cardiology, 45, 922-930. [9] Yang, Z., McMahon, C.J., and Smith, L.R. (2005) Danon disea se as an unde rrecogni zed cause of hypertrop hic car- diomyopathy in children. Circulation, 112, 1612-1617. |